Search results for: “pneumonia”

  • Nursing Dissertation Topics: Best Nurse Dissertation Topic Ideas and Titles in 2025

    Nursing Dissertation Topics: Nurse Topic Ideas and Dissertation Titles

    Choosing the right nursing dissertation topic is a crucial step in the academic journey of every nursing student, especially those pursuing a master’s or PhD in nursing. Whether you’re interested in community health, pain management, critical care, or mental health nursing, this guide provides a comprehensive list of dissertation titles and ideas tailored to modern nursing challenges. Read on to explore engaging nursing dissertation topics, understand how to choose the best research idea, and gain insight into recent dissertation trends across the nursing profession.

    Why Is Selecting the Right Nursing Dissertation Topic So Important?

    A well-chosen nursing dissertation topic not only aligns with your interests but also contributes meaningfully to nursing practice and health care improvement. Selecting the right topic sets the stage for a successful dissertation journey, from literature review to final defense. It also ensures your work can impact real-world nurse-led practices, policy development, or clinical protocols.

    How to Choose a Nursing Dissertation Topic That Reflects Your Passion and Goals

    Choosing the right nursing dissertation topic is both a strategic and personal decision. It involves balancing academic expectations with your unique professional interests and career aspirations. A thoughtful topic not only showcases your understanding of nursing challenges but also sets the foundation for meaningful, evidence-based contributions to the field.

    How to Choose a Nursing Dissertation Topics
    How to Choose a Nursing Dissertation Topics

    Here’s how to approach selecting a topic:

    • Reflect on Your Clinical Practice: Consider the most impactful or challenging cases you’ve encountered during clinical rotations. Think about the patient populations, conditions, or interventions that intrigued you. These real-world experiences often highlight issues worth researching.
    • Review Nursing Literature and Trends: Stay current by reading peer-reviewed journals, nursing blogs, and professional publications. Identify gaps, emerging challenges, or controversial topics in nursing care, education, or policy.
    • Explore the StudyingNurse.com Topics Section: Use this platform to browse curated dissertation ideas across various specializations. It’s an excellent starting point to discover high-demand topics and get clarity on how to narrow your focus.
    • Consult Mentors and Supervisors: Experienced faculty or clinical mentors can help guide you toward a topic that aligns with your academic level and practical scope. Their feedback is especially helpful when narrowing from a broad interest to a focused, researchable question.
    • Balance Scope and Feasibility: Your topic should be narrow enough to be manageable within your program’s timeline, yet broad enough to provide substantial findings. Consider access to data, ethical constraints, and whether the project can be realistically completed with available resources.
    • Align With Your Career Path: Choose a dissertation topic that complements your long-term goals—whether that’s becoming a nurse educator, policy advocate, advanced practice nurse, or researcher. This alignment adds relevance and motivation throughout the research process.

    By following these steps, you’ll ensure your dissertation is not only academically rigorous but also meaningful to your personal growth and the advancement of the nursing profession.

    What Makes a Good Topic for Your Nursing Dissertation?

    Choosing a strong nursing dissertation topic means going beyond surface-level interest. It involves selecting a subject that is clear, relevant, researchable, and aligned with real-world healthcare priorities. A well-crafted dissertation topic showcases your understanding of nursing challenges and your ability to contribute to evidence-based practice.

    Here are the essential qualities of a good nursing dissertation topic:

    • Focused and Specific: A great topic should narrow in on a precise issue within the nursing field. For example, rather than broadly studying “critical care,” a better topic would be “nurse-led care for sepsis patients in intensive care units.” This helps ensure that your research is both manageable and impactful.
    • Addresses a Real Problem: Your dissertation should aim to solve an actual healthcare issue faced by nurses, patients, or health systems. Whether it’s improving communication in emergency rooms or enhancing pediatric pain assessment protocols, your topic should serve a clear purpose.
    • Actionable and Policy-Relevant: A strong topic should lead to findings that inform nursing practice, influence health policy, or suggest improvements in patient care. Ideally, it should result in recommendations that nurses, educators, or administrators can implement.
    • Evidence-Based and Research-Supported: Your topic should allow you to engage with existing literature and contribute new insights. This ensures academic rigor and real-world credibility, especially if you’re pursuing a doctoral or PhD-level nursing dissertation.
    What makes nursing dissertation topics good

    A good topic not only fulfills academic requirements but also reflects your passion and readiness to lead change in the nursing profession.

    What Are the Best Nursing Dissertation Topics in 2022 and 2020?

    Looking back at 2022 and 2020 offers valuable inspiration. These years brought global healthcare challenges that shaped the nursing profession, influencing the types of dissertation topics nursing students chose. Mental health, emergency response, health promotion, leadership, and primary care emerged as top research areas.

    Emerging Themes in Nursing Research from 2018 and 2022

    Nursing dissertation topics from these years addressed issues like pandemic preparedness, virtual care delivery, and gaps in nursing education and leadership. The aim was often health improvement, service innovation, or support for vulnerable populations such as those with disability or chronic illnesses.

    • Pandemic Preparedness and Emergency Response
      Topics explored how nurses adapted during the COVID-19 crisis, focusing on ICU surge protocols, PPE use, and triage practices in overwhelmed emergency departments.
    • Virtual and Tele-Nursing Innovations
      With the rise of remote care, many dissertations evaluated telehealth outcomes, nurse-patient communication in digital platforms, and care continuity during lockdowns.
    • Mental Health Nursing and Burnout
      There was a surge in interest around nurse mental health, PTSD, and coping strategies, especially for psychiatric and frontline staff.
    • Leadership in Crisis and Change Management
      Nurse leadership under stress, particularly during public health emergencies, became a strong theme, along with mentorship and crisis communication.
    • Primary Care and Chronic Disease Management
      Research addressed how nurse-led clinics and services improved care for diabetes, hypertension, and obesity during constrained healthcare access.
    • Support for Vulnerable Populations
      These include nursing services focused on disability inclusion, elderly care, and patients with chronic or complex needs during periods of restricted services.
    • Nursing Education Gaps and Digital Learning
      Dissertations reviewed the effectiveness of online simulation, flipped classrooms, and e-learning platforms in nursing schools amid closures.
    • Health Promotion and Preventive Nursing
      Emphasis was placed on nurse-led community education programs targeting maternal health, adolescent wellness, and school-based interventions.
    • Workforce Resilience and Policy Reform
      Studies evaluated strategies for supporting nursing staff well-being, influencing NHS/US policy updates, and workforce retention post-pandemic.
    • Infection Control and Patient Safety
      Topics here examined evidence-based protocols in hand hygiene, antibiotic stewardship, and prevention of hospital-acquired infections.

    List of Nursing Dissertation Topics in Emergency Nursing and COVID-19 Response

    1. Evaluating nurse-led triage protocols in emergency departments
    2. ICU nurse preparedness during COVID-19 surges
    3. Nurse-led community outreach during pandemic vaccine rollouts
    4. Infection prevention strategies adopted by emergency nurses
    5. Rapid-response protocols and leadership in high-pressure emergency settings

    Nursing Education and Student Well-being Topics

    1. Effectiveness of remote learning on nursing student performance
    2. Academic resilience among undergraduate nursing students during the pandemic
    3. Supporting mental health nurses through peer-led learning during lockdowns
    4. Simulation-based training in school of nursing programs during COVID-19
    5. Dissertation topic selection challenges in online nursing programs

    Public Health and Primary Care Research Topics

    1. Nursing interventions to reduce pediatric obesity in primary care
    2. The role of nurses in improving health promotion awareness in rural areas
    3. Addressing disability-related stigma through primary care nurse education
    4. Enhancing wound care management protocols in community clinics
    5. Nurse-led hypertension control programs in underserved regions

    Psychiatric and Mental Health Dissertation Ideas

    1. Strategies for improving mental health nurses’ communication in telehealth
    2. Evaluating psychiatric nurse response to post-COVID anxiety and trauma
    3. Managing burnout among mental health nurses during prolonged crises
    4. School nursing and early intervention in adolescent psychiatric symptoms
    5. Tele-psychiatry adoption by nurses in remote mental health services

    Leadership and Professional Development Topics

    1. The role of nurse leadership in maintaining morale during health crises
    2. Leadership competencies for managing surgical teams during emergency care
    3. Evaluating mentorship impact in postgraduate (MSc/doctoral) nursing programs
    4. Building leadership skills in undergraduate nursing through service-learning
    5. Selecting the right nursing dissertation topic: A decision-making framework

    Specialty-Specific Dissertation examples from 2016 –2022

    1. Nurse involvement in cardiac rehab programs post-myocardial infarction
    2. Enhancing sepsis recognition through nurse education in critical care
    3. Pediatric nursing education challenges during school closures
    4. Maternal health and obstetrics: The nurse’s role in improving delivery outcomes
    5. Comparing oncology nurse-led pain management strategies pre- and post-pandemic
    6. The impact of NHS policy reforms on nurse-led service delivery in the UK
    7. School-based health promotion programs led by nurses in the UK
    8. Gynaecology nursing service improvement initiatives within NHS Tru

    These sample dissertation topics from 2020 and 2022 reflect the evolving priorities in the nursing profession across the US and UK. Whether your interest lies in emergency care, nursing education, psychiatric support, or leadership, these themes help in selecting the right nursing dissertation topic that is both timely and impactful.

    These sample dissertation topics from 2020 and 2022 reflect the evolving priorities in the nursing profession. Whether your interest lies in emergency care, nursing education, psychiatric support, or leadership, these themes help in selecting the right nursing dissertation topic that is both timely and impactful.

    Critical Care Nursing Dissertation Topics

    These topics are ideal for nurses in ICUs, emergency departments, or surgical recovery wards:

    1. Early sepsis detection by nurses in ICU settings
    2. Managing multi-organ failure: The nurse’s perspective
    3. Protocol adherence for critical care nurses during emergencies
    4. The role of simulation training in preparing ICU nurses
    5. Cardiac arrest response times in nurse-led vs. team-based settings
    6. The psychological toll on critical care nurses
    7. Ventilator-associated pneumonia prevention: Nurse-led interventions
    8. Evaluating handover protocols in critical care units
    9. Stress management programs for surgical ICU nurses
    10. Critical thinking development in trauma nurses

    Community Health Nursing Dissertation Topics

    Explore how nurses contribute to health promotion at the community level:

    1. Nurse-led vaccination campaigns in underserved communities
    2. Improving maternal health through community midwifery programs
    3. Health promotion and behavior change in rural populations
    4. Nurse involvement in public health policy design
    5. Diabetes education effectiveness in community health settings
    6. Addressing malnutrition through community nursing initiatives
    7. Screening for hypertension in resource-poor settings
    8. Smoking cessation counseling by community nurses
    9. Enhancing prenatal care through mobile health clinics
    10. Evaluating school nurse impact on child wellness

    Mental Health Nursing Dissertation Ideas

    Perfect for students focusing on psychiatric and behavioral health:

    1. Psychiatric nurse-led CBT for depression in adolescents
    2. Reducing nurse burnout in mental health settings
    3. Suicide risk assessment protocols in psychiatric nursing
    4. Therapeutic communication techniques in psychiatric wards
    5. Stigma and self-perception among mental health nurses
    6. Evaluating group therapy models in community psychiatry
    7. Nurse education on trauma-informed care practices
    8. Implementing mindfulness in inpatient psychiatric units
    9. Workplace violence against mental health nurses
    10. Support systems for nurses working in forensic psychiatry

    Pain Management and Palliative Care Topics

    Ideal for students focusing on chronic illness or end-of-life care:

    1. Nurse-led pain assessment tools in cancer care
    2. Improving comfort care in advanced dementia patients
    3. Ethical dilemmas in palliative nursing care
    4. Palliative care delivery in home vs. hospital settings
    5. Family counseling in end-of-life situations
    6. Managing pediatric pain: A nurse’s approach
    7. Training gaps in pain management education
    8. Chronic pain interventions in elderly populations
    9. Interdisciplinary collaboration in hospice settings
    10. Exploring spirituality in palliative care nursing

    Pediatric Nursing Dissertation Topics

    Explore topics relevant to neonatal, school-age, and adolescent care:

    1. Neonatal nurse interventions in premature birth outcomes
    2. Evaluating asthma education by pediatric nurses
    3. Parental satisfaction with nurse-led pediatric care
    4. School nurses’ role in managing chronic illnesses
    5. Pediatric obesity prevention through nurse counseling
    6. Pain assessment strategies in non-verbal children
    7. Educating parents on safe infant care practices
    8. Immunization adherence: The pediatric nurse’s influence
    9. Managing pediatric diabetes in school settings
    10. Reducing anxiety in children during hospital stays

    Nursing Education and Leadership Dissertation Ideas

    Target nurse educators, academic researchers, or future nurse leaders:

    1. The effect of simulation-based education on skill acquisition
    2. Nurse leadership in promoting interprofessional teamwork
    3. Mentorship programs and their role in nurse retention
    4. Improving preceptorship experiences for student nurses
    5. Academic stress management among nursing students
    6. Integrating technology in nursing education programs
    7. Leadership styles and nurse job satisfaction
    8. Competency frameworks in nurse training curricula
    9. Evaluating flipped classroom models in nursing schools
    10. Impact of continuing education on nursing care quality

    List of Nursing Dissertation Topics

    If you’re still exploring ideas, here’s a broader list with AEO-friendly formatting:

    30 Dissertation Topics for Nursing Students

    1. The effectiveness of tele-nursing in chronic heart failure management
    2. Nurse-led obesity prevention programs in primary care
    3. How nurse communication reduces medication errors
    4. Health nurses and adolescent sexual health education
    5. Diabetic wound care: A nursing perspective
    6. COVID-19 and nurse burnout: Lessons learned
    7. Pre-op assessments: Nurse-led vs. physician-led outcomes
    8. Barriers in child abuse reporting by school nurses
    9. Ethical decision-making in palliative care nursing
    10. Managing hypertension with community health nurse interventions
    11. The role of school nurses in mental health early detection
    12. Patient satisfaction in nurse-led postnatal care
    13. Evaluating nurse involvement in emergency preparedness
    14. Improving infection control through nursing audits
    15. Use of wearable tech in nurse-monitored home care
    16. The nurse’s role in elder fall prevention
    17. Integrating AI tools in nursing diagnostics
    18. Exploring mobile apps for nursing education support
    19. Nurse strategies in promoting HPV vaccination
    20. Nurse resilience-building programs and their outcomes
    21. Preventing pressure ulcers in long-term care
    22. Antibiotic stewardship initiatives led by nurses
    23. Evaluating e-learning in postgraduate nursing training
    24. The influence of cultural competence in global nursing
    25. Addressing disability inclusion in nursing services
    26. Pediatric nurse interventions in developmental disorders
    27. Nurse attitudes toward end-of-life discussions
    28. Evaluating holistic care in nurse training programs
    29. Nursing informatics integration in clinical workflows
    30. Role of nurses in implementing trauma care protocols

    Tips for Nursing Students: Selecting the Right Dissertation Topic and Service

    Selecting the right nursing dissertation topic is a crucial step toward academic success and professional development. A well-defined topic not only reflects your area of interest but also opens the door to impactful, evidence-based research that contributes to nursing practice and policy.

    Here are strategic and practical tips to help you choose an effective dissertation topic:

    • Identify Gaps in Research: Start by conducting a thorough literature review using reliable academic databases. Focus on recent publications to uncover underexplored or emerging topics in nursing practice, education, or health policy.
    • Use StudyingNurse.com for Inspiration: Visit the StudyingNurse.com Topics Section to explore curated lists of trending dissertation topics, nursing education gaps, and hot issues in primary care, mental health, and patient safety. The platform helps students easily browse research themes relevant to both UK and US contexts.
    • Ensure Measurable Outcomes: Your topic should support measurable data collection, whether through surveys, patient outcomes, or policy evaluation. Avoid topics that are too abstract or lack real-world applications.
    • Test Feasibility Early: Consider your available time, resources, and access to research participants or institutional data. StudyingNurse.com’s Primary Research Finding Service can help you locate relevant sources, validated tools, and current datasets to support your topic.
    • Align with Your Specialization: Select a topic that aligns with your nursing track (e.g., pediatric, critical care, psychiatric, community health) and future career goals. This ensures your work remains relevant and meaningful.
    • Seek Academic Guidance: Talk to your dissertation advisor, nursing faculty, or peers who have completed similar projects. Their feedback can help you refine and validate your topic choice, ensuring academic rigor and originality.

    Remember: Selecting the right nursing dissertation topic is a crucial step toward producing valuable research that influences the future of nursing care and healthcare systems.

    How to Choose a Nursing Research Topic for your Dissertation

    Selecting the right nursing research topic is often the most challenging step in the dissertation process. The direction you choose will shape months of your academic journey, so it’s worth investing time in thoughtful consideration. Two proven frameworks can guide your decision-making process and help you identify a topic that’s both meaningful and manageable.

    The 3 Ps Approach: Mapping Your Research Landscape

    The 3 Ps framework—Populations, Problems, and Practices—provides a systematic method for generating potential research areas aligned with your interests:

    The 3 Ps Approach to Nursing Dissertation Topics
    The 3 Ps Approach to Nursing Dissertation Topics

    Patient Populations

    Consider which groups capture your professional interest or where you have valuable experience:

    Start by identifying specific patient populations you’re passionate about or have clinical experience with. These could include pediatric patients, older adults, marginalized communities, mental health service users, or patients with chronic illnesses like diabetes or heart failure.

    • Pediatric patients with chronic conditions
    • Geriatric populations in community settings
    • Underserved rural communities
    • Post-surgical recovery patients
    • Mental health populations
    • Maternal-child healthcare recipients

    Healthcare Problems

    Think about pressing healthcare problems or clinical challenges affecting those populations. These might include delayed wound healing, medication adherence, access to mental health care, high hospital readmission rates, or barriers to preventive care. Identify challenges that warrant further investigation:

    • Medication adherence barriers
    • Healthcare access disparities
    • Hospital readmission patterns
    • Care coordination breakdowns
    • Patient education effectiveness
    • Healthcare-associated infections
    • Nursing workflow inefficiencies

    Nursing Practices

    Practices: Finally, explore existing nursing practices or interventions related to these problems. Ask yourself which practices are effective, where the gaps lie, or how protocols vary across settings (e.g., nurse-led vs. multidisciplinary care). Explore interventions, approaches, or methodologies that could be evaluated or improved:

    • Evidence-based protocols for specific conditions
    • Nurse-led education initiatives
    • Interdisciplinary collaboration models
    • Technology integration in care delivery
    • Patient-centered communication techniques
    • Transitional care approaches
    • Clinical simulation in nursing education

    The intersection of your selected Population, Problem, and Practice often reveals fertile ground for research. For example, combining “geriatric patients” (population) with “medication adherence” (problem) and “nurse-led education initiatives” (practice) might lead to a focused study on how specialized nursing education affects medication compliance among older adults.

    The FINER Criteria: Evaluating Topic Viability

    Using the F.I.N.E.R. Criteria for Topic Selection

    The F.I.N.E.R. criteria—Feasible, Interesting, Novel, Ethical, and Relevant—is a widely recommended framework for evaluating whether a dissertation topic is worth pursuing, especially for nursing students involved in clinical or applied research. Here’s how you can apply each component of the F.I.N.E.R. criteria to ensure your nursing dissertation topic is academically sound and professionally meaningful:

    The FINER Criteria for Nursing Dissertation Topics
    The FINER Criteria for Nursing Dissertation Topics

    Feasible

    Can you realistically complete this research with available resources?

    • Consider time constraints, access to participants, and required approvals
    • Evaluate whether you have the necessary skills or can acquire them
    • Assess potential obstacles and how they might be addressed

    Interesting

    Will this topic sustain your intellectual engagement?

    • Choose something that genuinely excites your curiosity
    • Consider whether you’ll remain motivated through challenging phases
    • Reflect on whether the topic connects to your personal nursing experiences

    Novel

    Does your research add something new to the field?

    • Look for gaps in existing literature or practice
    • Consider new angles on previously studied topics
    • Identify opportunities to extend or challenge current understanding

    Ethical

    Can the research be conducted while respecting patient rights and wellbeing?

    • Consider potential risks to participants and how they’ll be minimized
    • Evaluate whether benefits outweigh any potential harms
    • Assess whether vulnerable populations are protected appropriately

    Relevant

    Will your findings matter to nursing practice or education?

    • Consider the potential impact on patient outcomes
    • Evaluate alignment with current healthcare priorities
    • Assess whether results could influence nursing procedures, education, or policy

    Additional Strategic Approaches

    Beyond these frameworks, consider these practical strategies for topic identification:

    • Review Clinical Journals: Note where authors suggest “future research is needed”
    • Analyze Healthcare Policy Reports: Identify priority areas emphasized by nursing organizations
    • Consult with Mentors: Discuss potential topics with experienced researchers
    • Examine Interdisciplinary Intersections: Consider how nursing connects with technology, psychology, or business
    • Reflect on Clinical Observations: Consider patient care challenges you’ve personally witnessed

    Remember that your dissertation isn’t just an academic exercise—it’s an opportunity to contribute meaningfully to nursing knowledge while developing expertise that can shape your career trajectory. By applying these structured approaches, you’ll identify a topic that balances scholarly merit with personal significance.

    Frequently Asked Questions on Nursing Dissertation Topics

    • How to choose a nursing dissertation topic? – Provides a balanced approach considering personal interests, academic requirements, and practical considerations.
    • What is the best topic for nursing research? – Identifies current high-impact areas in nursing research with specific examples that reflect contemporary healthcare challenges.
    • What is the best dissertation topic? – Outlines five key criteria that make a dissertation topic effective, emphasizing the subjective nature of “best” based on individual circumstances.
    • How do I choose a nursing research topic? – Offers structured approaches including the “3 Ps” framework (Populations, Problems, Practices) and the FINER criteria for evaluating potential topics.
    • How do I find a unique dissertation topic? – Provides seven specific strategies for identifying original research areas, including interdisciplinary approaches and understudied populations.
    • How long is a nursing dissertation? – Gives concrete word count and page ranges for different degree levels (BSN, MSN, DNP, PhD) while emphasizing quality over quantity.
  • Focused Exam Chest Pain Shadow Health: Assessment Guide with Example

    Introduction to the Focused Exam

    A thorough, objective, focused exam chest pain  Shadow Health involves a systematic assessment of vital signs, chest wall inspection, and palpation. When preparing for your clinical rotations, understanding how to properly assess a patient presenting with chest pain is a fundamental skill that could save lives. The focused exam chest pain Shadow Health assessment offers a realistic environment to hone these skills without the pressure of a real-life emergency. This comprehensive guide explores how to effectively approach, conduct, and document this essential assessment, using the virtual patient Brian Foster as your study subject.

    Shadow Health Brian Foster Case

    Brian Foster, the 58-year-old Caucasian male patient in this Shadow Health simulation, presents with troubling chest pain that requires careful assessment. This virtual patient interaction allows nursing students to practice their clinical reasoning and documentation skills in a controlled environment.

    The Shadow Health focused exam for chest pain allows you to interact with Brian, collect subjective and objective data, and develop a comprehensive report based on your findings. This article will guide you through the entire process, ensuring you understand how to maximize your learning from this digital clinical experience.

    Focused Exam Chest Pain Shadow Health flowchart

    Preparing for the Focused Exam: Chest Pain Assessment

    Before beginning your shadow health focused assignment, take time to review the relevant content in your health assessment textbook. Pay particular attention to:

    • Cardiac assessment techniques
    • Respiratory assessment methods
    • Pain assessment scales
    • Documentation requirements for chest pain

    Understanding these fundamentals will help you approach the exam with confidence and ensure you collect all necessary data to complete your assessment of Brian Foster successfully.

    Conducting the Focused Exam: Chest Pain Interview

    The interview portion of the chest pain focused exam is where you’ll gather subjective data from Brian about his experience. Here’s how to structure this important component:

    Investigating Onset and Duration of Chest Pain

    When you meet Brian, you’ll need to ask about onset and duration of his chest pain. Document carefully when the pain began and how long episodes typically last. This information is crucial for determining potential causes and urgency.

    Questions to consider:

    • “When did you first notice the chest pain?”
    • “Have you experienced this chest pain before?”
    • “What were you doing when the chest pain started?”
    • “Is there anything that seems to trigger the onset of chest pain?”

    Pain Assessment in the Shadow Health Chest Pain Scenario

    focused exam chest pain Shadow Health assessment scale

    During your focused exam, you’ll be asked to rate chest pain on a scale of 1-10. This standardized pain assessment helps quantify Brian’s subjective experience and track changes in his condition.

    Beyond intensity, document:

    • Pain quality (sharp, dull, burning, etc.)
    • Radiation (Does the pain extend to the neck, shoulder, or arm?)
    • Alleviating factors (What makes the pain better?)
    • Exacerbating factors (What makes the pain worse?)
    • Associated symptoms (shortness of breath, nausea, etc.)

    If Brian mentions arm pain or discomfort radiating to other areas, this could indicate cardiac involvement, so document these findings carefully in your report.

    Related Symptoms and Health History

    The chest pain focused exam should include questions about:

    • Heartburn or indigestion symptoms
    • Exercise tolerance and whether exertion worsens symptoms
    • Past cardiac history
    • Family history of heart disease
    • Risk factors such as smoking, diet, stress levels

    Brian may mention feeling uncomfortable during certain activities or experiencing distension in his abdomen. These details should be documented thoroughly as they contribute to a complete clinical picture.

    Physical Assessment Components

    After gathering subjective data, you’ll conduct the physical portion of the focused exam chest pain Shadow Health simulation. This objective data collection phase is crucial for developing an accurate clinical impression.

    Cardiovascular Assessment

    During the cardiac exam, you’ll need to:

    1. Auscultate heart sounds in all four cardiac areas
    2. Locate and document the PMI (Point of Maximum Impulse)
    3. Assess for any irregular heartbeats or abnormal sounds
    4. Check for signs of sinus rhythm or ST changes on the ECG if available
    5. Palpate peripheral pulses

    Respiratory Assessment

    The respiratory component of your focused exam includes:

    1. Observing respiratory rate, depth, and pattern
    2. Auscultating breath sounds in all lung fields
    3. Noting any abnormal breath sounds like crackles or wheezes
    4. Assessing for tenderness when you palpate the chest wall

    Additional Assessment Areas

    Don’t forget to:

    • Check for neck vein distension
    • Palpate for tenderness in the epigastric region
    • Assess skin color and temperature
    • Document vital signs thoroughly
    focused exam chest pain Shadow Health physical assessment

    Documenting Your Findings

    Creating a thorough report following your focused exam chest pain assessment is essential for clinical communication and your grade in the Shadow Health study module. Your document should include:

    1. All subjective data collected from Brian
    2. Complete objective findings from your physical exam
    3. Analysis of potential causes for Brian’s chest pain
    4. Recommended follow-up or further testing

    The Shadow Health platform evaluates your transcript based on thoroughness and accuracy, so be methodical in your documentation.

    Focused Exam Chest Pain Shadow Health Example

    Cardiovascular and Chest Pain Assessment Activity

                Nurses should comprehensively assess vital concerns to rule out life-threatening circumstances when dealing with patients like Brian who are presenting with chest pain. There are several priority questions and assessments that nurses should conduct on such patients. First, the nurse should patient’s onset of pain. The priority question is, ‘Mr. Brian, when did you start experiencing chest pain? Was the pain gradual or did it increase gradually?’ Enquiring about the onset of pain will help the nurses to establish whether the patient’s pain relates to a recent surgery or a new serious condition like a heart attack. Secondly, the nurse should assess the nature of the pain. The priority question is, ‘Mr. Brian, please tell me more about your pain. Is it dull, sharp, or burning? Is your pain constant or does it come and disappear?’ Comprehending the nature of the pain will inform the nurse about the potential causes (Wilson & Giddens, 2020). The third assessment should be about associated symptoms. The priority question will be, ‘Do you have any other symptoms such as shortness of breath, sweating, or dizziness?’ Asking about other symptoms helps to indicate symptoms such as conditions such as heart disease.

                The nurse should assess Brian’s vital signs such as heart rate, blood pressure, oxygen saturation, and respiratory rate. The nurse should also examine physical examination to identify distress signs such as difficulty in breathing, and sweating. An ECG assessment was also necessary to determine potential abnormal electrical abnormalities of the heart while blood tests will check for cardiac enzymes released when the heart muscles are damaged (Tejtel et al., 2022). 

                On the contrary, Tina presents with a family history of heart disease and high blood pressure. The nurse should focus on Tina’s blood pressure. The priority question is, ‘Tina, have you been monitoring your blood pressure at home? What are ranges about the reading?’ Monitoring the patient’s blood pressure is vital to evaluate the effectiveness of the new medication. The nurse should also assess Tina’s medication adherence. The priority question is, ‘Are you under any medication currently? Have you taken all doses as prescribed?’ Inquiring about medication adherence is vital to determine non-compliance. Lastly, the nurse should evaluate Tina’s lifestyle. The priority question is, ‘Do you have an exercise or diet routine? Assessing Tina’s physical activity levels is relevant since it affects cardiovascular health. Tina’s health assessments should include blood pressure measurements. Heart and lung auscultation is also necessary to reveal irregular heartbeats or abnormal heart sounds that imply heart disease or respiratory problems (Jarvis, 2018). Peripheral vascular assessment is also necessary to check edema and observe poor circulation or lower extremity pulses.

                The assessments for Tina and Brain are different. Tina’s assessment focused on the cardiovascular system, including edema and high blood pressure. Tina’s questioning entailed exercise habits, diet, and medication adherence. On the contrary, the Brain needed immediate attention to the elevated heart rate and chest pain. Brian’s questions included the severity, duration, and onset of the chest pain. Brian’s NANDA nursing diagnosis is acute pain linked to myocardial ischemia. The Nursing Interventions (NICs) include pain management through administration of analgesics and evaluating their effectiveness. Secondly, cardiac care through monitoring of vital signs and heart rhythm will be vital to detect abnormalities. The last intervention is patient education on lifestyle modification. The Nursing Outcomes (NOCs) is pain control where the patient reports the pain is manageable. The second outcome is cardiac stability where heart rhythm and vital signs are within normal ranges. The outcome is the patient demonstrating a high level of understanding of his health state and lifestyle modification.

    References

    Jarvis, C. (2018). Physical examination and health assessment (8th ed.).  St. Louis, MO: Saunders.

    Tejtel, S. K. S., Munoz, F. M., Al-Ammouri, I., Savorgnan, F., Guggilla, R. K., Khuri-Bulos, N., … & Engler, R. J. (2022). Myocarditis and pericarditis: case definition and guidelines for data collection, analysis, and presentation of immunization safety data. Vaccine40(10), 1499-1511. https://doi.org/10.1016/j.vaccine.2021.11.074

    Wilson, S. F., & Giddens, J. F. (2020). Health Assessment for Nursing Practice-E-Book. Elsevier Health Sciences. https://books.google.co.ke/books?hl=en&lr=&id=_foPEAAAQBAJ&oi=fnd&pg

    Common Challenges in the Shadow Health Brian Foster Case

    Many nursing students struggle with specific aspects of this simulation:

    • Remembering to ask about onset and duration of chest pain
    • Correctly documenting radiation patterns
    • Properly conducting and documenting the cardiac exam
    • Distinguishing between cardiac and non-cardiac causes

    To overcome these challenges, study with Quizlet and memorize flashcards containing terms like sinus rhythm, PMI assessment, and proper chest pain documentation language.

    Tips for Success in the Shadow Health Focused Exam

    To achieve the highest score on your chest pain focused exam in Shadow Health:

    1. Read the assignment instructions thoroughly before beginning
    2. Review cardiac assessment techniques in advance
    3. Take a systematic approach to both the interview and physical exam
    4. Document thoroughly, including negative findings
    5. Ask follow-up questions based on Brian’s responses
    6. Complete all components of the assessment
    7. Review your document before submission

    FAQs About the Focused Exam: Chest Pain Shadow Health Assessment

    What should I do if I’m unable to access the PDF of my Shadow Health transcript?

    If you encounter technical difficulties accessing the PDF of your Shadow Health transcript, first try clearing your browser cache and cookies, then restart your browser. If problems persist, contact Shadow Health technical support through your course portal and document your attempt to resolve the issue for your instructor.

    How can I improve my health assessment skills beyond the Shadow Health simulations?

    To enhance your health assessment proficiency, consider joining study groups that practice physical examination techniques, volunteer at community health screenings to gain real-world experience, and regularly review anatomy and physiology to better understand normal versus abnormal findings you might encounter during assessments.

    How should I interpret abnormal breath sounds during a chest pain assessment?

    When you detect abnormal breath sounds like crackles or wheezes during a chest pain assessment, correlate these findings with other clinical data such as oxygen saturation, respiratory rate, and the patient’s reported symptoms to determine possible underlying causes, which could range from heart failure to pneumonia depending on the overall clinical picture.

    What is the significance of ST changes in relation to chest pain assessment?

    ST changes on an ECG during a chest pain assessment may indicate myocardial ischemia or injury, requiring immediate medical attention; these electrocardiogram alterations are particularly concerning when they coincide with chest discomfort, shortness of breath, or other cardiac symptoms and should prompt urgent cardiology consultation.

  • Brian Foster Shadow Health Assessment: A Chest Pain Focused Exam | Example and Guide

    Brian Foster Shadow Health Assessment: Chest Pain Focused Exam

    Brian Foster is a 54-year-old male patient in Shadow Health who presents with chest pain. As a nursing student, your task involves conducting a thorough assessment, including gathering a health history and performing a focused physical examination. The Brian Foster case challenges students to differentiate between cardiac and non-cardiac causes of chest pain, a critical skill for any future healthcare provider.

    Cardiovascular Brian Foster shadow health Assessment Guide
    Cardiovascular Brian Foster Shadow Health Assessment Guide

    Brian Foster Chest Pain Focused Exam

    DOCUMENTATION OF HISTORY AND PHYSICAL EXAM

    Patient Name (Initials only): B.R DOB: March/10/1965 Gender:

    CHIEF COMPLAINT “My chest pains”
    HISTORY OF PRESENT ILLNESS
    Mr. B.R., a 58-year-old man, complained of chest pain in the middle of his chest when he arrived at the emergency room. It starts abruptly and does not radiate. Moving up the stairs and exertion exacerbate the tight, painful discomfort. Resting reduces the pain. The patient continues with everyday activities despite the pain, which is not severe. Mr. B.R. experiences periodic and intermittent chest pain. In one month, he has experienced three pain bouts. Three days ago was the most recent incident. According to the patient, the pain is related to leg cramps. He does not, however, admit to having heartburn, orthopnea, syncope, indigestion, nausea, vomiting, exhaustion, or shortness of breath.
    PAST MEDICAL HISTORY
    B.R. denies previous medical conditions.
    The patient denies previous hospitalization, surgery, or trauma.
    Medications None
    Allergies/Adverse Reactions None
    Immunizations:  Flu – 2019, Pneumonia – 2009 Tdap – Denied Zoster – Denied, Covid – 2021, June
    FAMILY HISTORY
    The patient is the youngest of three siblings in a family of five. The father suffered from hypertension and coronary heart disease and died at 60. The mother had developed diabetes mellitus and high blood pressure and died at 68. His siblings are all still alive and well.
    SOCIAL HISTORY The patient has a wife and kids. He is a call center manager and likes reading books and watching television. He does not smoke and occasionally drinks alcohol. Grilled meat, sandwiches, and vegetables are staples in his diet. Typically, he consumes grilled meat 4-5 times a week. On busy days, he eats fast food for lunch. Every day, he drinks 1-2 cups of coffee.
    REVIEW OF SYSTEMS
    Constitutional
    Patient denies fatigue, dizziness, weakness, fever, and weight loss.
    Eyes
    B.R. denies visual impairment or blurry vision
    Ears/Nose/Throat
    Immunizations:  Flu – 201,9, Pneumonia – 2009 Tdap – Denied Zoster – Denied, Covid – 2021, June
    Mouth / Dental
    Ears: denies hearing changes or ear pain. Nose: denies sneezing or change in the sense of smell, sinus pain, or pressure. Throat: denies difficulty swallowing- dry mouth, swollen lymph nodes
    Breast
    N/A
    Cardiovascular The patient reports chest pain at the mid-sternum of the chest, causing discomfort.
    Respiratory Denies cough or chest tightness, difficulty breathing except during asthma attacks, and dyspnea on exertion.
    Gastrointestinal
    Denies nausea or vomiting, abdominal pain, no changes in bowel or bladder pattern, or constipation; denies diarrhea.
    Genito-Urinary
    Denies change in urinary pattern; denies dysuria or incontinence. He is heterosexual. B.R. denies a history of STDs and reports being sexually active with his wife, who is under birth control.
    Male Reproductive
    Denies any erectile or urinary problems
    Female Reproductive N/A
     
    Denies tooth decay and gum disease; the last visit to the dentist was one year ago. B.R. denies speech problems, sinus drainage, taste, and snoring
    Neurological
    The patient denies syncopal episodes or dizziness, paresthesia, change in memory or thinking pattern, disturbances or problems with coordination, and seizure history.
    Skin
    Denies rashes, itching, or bruising. Denies changes in skin color.
          Endocrine
    B.R. denies polyurea, polyphagia, polydipsia, or fatigue. He denies heat or cold intolerance or shedding of hair.
    Hematologic/Lymphatic:
    B.R.  denies bruising, bleeding, and anemia. He has no history of blood transfusion or thrombolytic disorders.
    Psychiatric
    He denies a history of anxiety or depression, apart from when his father and mother died from an illness. He denies fatigue, sleep disturbances, delusions, or mental health history. B.R. denies suicidal and homicidal history or ideation.
    PHYSICAL EXAMINATION (Please describe your findings from inspection, palpation, percussion, & auscultation and use the term “deferred” if you did not examine that area.)
    Vital signsHt: 5’8 Wt 198 BMI 30.1 
     Temp: 98.2F Pulse 85 BP 110/68 
     R.R. 18 Pain 4/10   
    General Appearance
    The patient appears healthy, dressed appropriately for the season, clean and well-groomed, with well-kempt hair. BMI indicates obesity.
    Head Normocephalic and atraumatic. Patient denies headaches
    PHYSICAL EXAMINATION (Please describe your findings from inspection, palpation, percussion, & auscultation, and use the term “deferred” if you did not examine that area.)
    Ears/Nose/Throat
    Oropharynx red, moist mucous membranes
    Mouth / Dental
    Teeth appear healthy and aligned. No odor or teeth decay.
    Neck Supple. No JVD. Trachea midline. No pain, swelling, or palpable nodules.
    Eyes Sclera anicteric, no conjunctival erythema, PERRLA
    Cardiovascular
    Although the patient’s heartbeat and rhythm are regular, murmurs and other sounds are coming from her chest. The patient’s heart rate is constant, and capillaries refill in two seconds. S3 rub is noted at the mitral area. The JVP is 3cm above the sternal angle. A bruit was noted on the right carotid, which had a 3+ thrill.
    Gastrointestinal No nausea or vomiting, no abdominal pain or bowel changes
    Genitourinary/Gynecological No changes in urinary pattern, no dysuria or inconsistency, no STD, reports being sexually active with wife.
    Gastrointestinal: No nausea or vomiting, no abdominal pain or bowel changes
    Lymphatic: No axillary lymphadenopathy or swelling on palpation
    Back, Extremities, Musculoskeletal
    Skin: No rashes or bruising
    No arthralgia and myalgia, no arthritis gout, or limitations in range of motion, no trauma or fractures
    Psychiatric No anxiety or depressive report, fatigue, sleep disturbances, or suicidal or homicidal ideation.
    Neurological: No syncopal episodes or dizziness, no paresthesia, no change in memory or thinking pattern, denies disturbances or problems with coordination.
    List 3 Differential Diagnoses with Rationale (pertinent positive and negative)
    Coronary artery disease with stable angina
    Congestive heart failure
    Costochondritis Rationale The chest pain that characterizes B.R.’s typical angina is typically brought on by a buildup of plaque in the arteries that supply the heart with blood. B.R. is at risk for coronary artery disease due to his history of hypertension, hyperlipidemia, and familial myocardial infarction. He described the pressure in his mid-sternum as his chest pain. Angina can happen while the heart is working harder or at rest, and it can continue for five to thirty minutes. Usually eased with nitrate and rest. Right-sided carotid bruit and thrill are B.R.’s first signs of heart failure. Typically, more fluid causes an S3 gallop. Additionally, the bilateral posterior bases of his lungs displayed fine crackles. These signs and symptoms all point to Class II heart failure ( Inamdar & Inamdar, 2019). Physical activity is slightly restricted in patients with class II heart failure, who are comfortable at rest but experience heart failure symptoms during routine physical exercise( Shahjehan & Bhutta, 2022).  When the patient started pulling weeds, the first thing that came to mind was a musculoskeletal condition like costochondritis. When doing repetitive upper body movements, the strain on the upper chest costal cartilage can feel like angina in the upper to mid-sternum region.
    ASSESSMENT ICD-10 code I25 Coronary artery disease with stable angina (Confirmed Diagnosis) A mismatch in supply and demand is what causes stable angina. Symptoms frequently appear when the myocardial oxygen demand momentarily surpasses the myocardial oxygen supply. Stable angina is caused by several factors, with coronary artery stenosis being the most common cause (Gillen & Goyal, 2021). An imbalance between the myocardial oxygen supply and the myocardial oxygen demand typically causes angina to emerge. Myocardial ischemia is most frequently caused by coronary artery stenosis. The stenosis prevents a sufficient delivery of cardiac oxygen during periods of high myocardial oxygen demand. The primary parameters affecting oxygen demand are heart rate, systolic blood pressure, myocardial wall tension, and myocardial contractility (Gillen & Goyal, 2021). The chest pain that characterizes B.R.’s typical angina is typically brought on by a buildup of plaque in the arteries that supply the heart with blood ( Schumann, Sood, & Parente, 2023). Angina can happen while the heart is working harder or at rest, and it can continue for five to thirty minutes. Usually eased with nitrate and rest.
    REFERENCE (include at least one evidence-based guideline/peer-reviewed journal article to support the diagnosis and plan) Gillen, C., & Goyal, A. (2021). Stable Angina. In StatPearls [Internet]. StatPearls Publishing. Inamdar, A. A., & Inamdar, A. C. (2019). Heart Failure: Diagnosis, Management and Utilization. Journal of Clinical Medicine5(7), 62. https://doi.org/10.3390/jcm5070062 Schumann, J. A., Sood, T., & Parente J. J. (2023). Costochondritis. In: StatPearls [Internet]. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK532931/ Shahjehan, R. D., & Bhutta, B. S. (2022). Coronary artery disease. In StatPearls [Internet]. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK564304/
    REFERENCE (include at least one evidence-based guideline/peer-reviewed journal article to support the diagnosis and plan)
    Gillen, C., & Goyal, A. (2021). Stable Angina. In StatPearls [Internet]. StatPearls Publishing. Inamdar, A. A., & Inamdar, A. C. (2019). Heart Failure: Diagnosis, Management and Utilization. Journal of Clinical Medicine, 5(7), 62. https://doi.org/10.3390/jcm5070062
    Schumann, J. A., Sood, T., & Parente, J. J. (2023). Costochondritis. In: StatPearls [Internet]. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK532931/
    Shahjehan, R. D., & Bhutta, B. S. (2022). Coronary artery disease. In StatPearls [Internet]. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK564304/

    Conducting the Focused Exam with Brian Foster

    The focused exam for Brian Foster in Shadow Health concentrates on the cardiovascular system due to his presenting complaint of chest pain. During this exam, students should:

    Brian Foster Shadow Health

    Initial Assessment

    When you first meet Brian Foster in Shadow Health, begin by establishing rapport and identifying his chief complaint. Brian will describe his chest pain, which he might characterize as tight and uncomfortable. Students should ask Brian Foster to rate his chest pain on a scale of 1-10 and determine when his chest started hurting.

    Health History

    Collecting a comprehensive health history from Brian Foster is crucial. Key areas to explore include:

    1. Family History: Ask about any family history of heart conditions or high cholesterol.
    2. Personal Health History: Inquire about Brian’s history of angina, high blood pressure, or heart murmur.
    3. Medication Review: Document any cardiovascular medications like Lisinopril.
    4. Risk Factors: Assess for cardiovascular risk factors such as smoking, diet, and physical activity.

    Brian Foster may mention that he has high blood pressure and high cholesterol. He might also share his family history of heart disease, which is relevant health information that could contribute to his current condition.

    Physical Examination

    During the physical examination of Brian Foster in Shadow Health, you should:

    • Measure vital signs, including blood pressure
    • Observe for any signs of distension in the neck veins
    • Auscultate for heart murmurs or abnormal heart sounds
    • Palpate the chest to identify areas of tenderness
    • Assess for arm pain, back pain, or neck pain that might radiate from the chest

    The Shadow Health platform allows you to perform these assessments virtually, providing feedback on your technique and findings.

    Differential Considerations for Brian Foster’s Chest Pain

    When working with Brian Foster in Shadow Health, consider various potential causes for his chest pain:

    Cardiac Causes

    • Angina
    • Myocardial infarction
    • Pericarditis

    Non-Cardiac Causes

    • Heartburn (Brian might mention “it might just be heartburn”)
    • Pulmonary conditions (check for history of pulmonary embolism)
    • Musculoskeletal pain
    • Anxiety

    Through careful questioning and examination, you’ll gather data to help determine the likely cause of Brian Foster’s chest pain. Shadow Health experts emphasize the importance of not jumping to conclusions before completing a thorough assessment.

    Communication Strategies for the Brian Foster Case

    Effective communication with Brian Foster in Shadow Health requires a balanced approach. Shadow Health recommends using a combination of open and closed questions when interviewing patients like Brian Foster:

    • Open questions encourage Brian to share his experience in his own words
    • Closed questions will yield better patient data for specific details like pain intensity

    For example, you might start with an open question like “Can you tell me about your chest pain?” followed by more specific closed questions such as “Did your chest pain radiate to your arm?”

    As you ask about the onset and duration of chest pain, maintain a conversational tone while systematically gathering necessary information. Brian Foster’s responses in Shadow Health are programmed to react to different questioning approaches, providing valuable feedback on your communication techniques.

    Documenting the Brian Foster Encounter

    Proper documentation of your encounter with Brian Foster in Shadow Health is essential for success in this simulation. Your documentation should include:

    Subjective Data

    Record what Brian Foster tells you about his chest pain and health history, including:

    • Description of pain (tight and uncomfortable)
    • Onset and duration of chest pain
    • Associated symptoms
    • Relevant health history, such as high blood pressure or history of angina

    Objective Data

    Document your physical findings and measurements:

    • Vital signs, including blood pressure
    • Heart and lung sounds
    • Areas of tenderness upon palpation
    • Observable signs of distress

    Shadow Health provides a documentation system for recording your findings from the Brian Foster case, which then factors into your overall assessment grade.

    Common Challenges in the Brian Foster Shadow Health Simulation

    Many nursing students encounter similar challenges when working through the Brian Foster chest pain scenario in Shadow Health:

    1. Missing Key Questions: Failing to ask about critical aspects of chest pain, such as aggravating or alleviating factors
    2. Incomplete Physical Assessment: Not performing all necessary aspects of the cardiovascular examination
    3. Poor Documentation: Inadequately recording subjective and objective data
    4. Time Management: Spending too long on certain aspects of the assessment while neglecting others

    To overcome these challenges, review resources like the focused exam guide and Shadow Health experts’ recommendations before beginning the Brian Foster simulation.

    Preparing for the Brian Foster Shadow Health Assessment

    Successful completion of the Brian Foster chest pain Shadow Health assessment requires preparation. Consider these strategies:

    1. Review Cardiovascular Assessment: Understand the components of a focused cardiovascular exam
    2. Study Chest Pain Differentials: Know the various causes of chest pain and their distinguishing features
    3. Practice Documentation: Familiarize yourself with proper documentation of subjective and objective data
    4. Utilize Available Resources: Many students study with Quizlet and memorize flashcards containing terms like angina, myocardial infarction, and other cardiovascular concepts.

    Some students find it helpful to review peers’ experiences with the Brian Foster case through discussion boards or study groups, though they always maintain academic integrity by forming your assessment rather than copying others’ work.

    Interpreting Your Results from the Brian Foster Case

    After completing the Brian Foster chest pain Shadow Health assessment, you’ll receive feedback on your performance. This feedback evaluates:

    • Thoroughness of your health history
    • Accuracy of your physical examination techniques
    • Appropriateness of your communication approach
    • Completeness of your documentation

    Shadow Health experts design this feedback to be educational rather than merely evaluative. Use insights from your performance with Brian Foster to strengthen your clinical reasoning skills for future patient encounters.

    Applying Brian Foster Shadow Health Learning to Clinical Practice

    The skills practiced in the Brian Foster Shadow Health simulation translate directly to clinical practice. When encountering real patients with chest pain, you’ll need to:

    1. Quickly establish the nature of the chief complaint
    2. Perform a targeted assessment based on presenting symptoms
    3. Think critically about potential causes
    4. Communicate findings effectively to the healthcare team

    The experience of assessing Brian Foster in Shadow Health builds confidence for these real-world clinical situations. By mastering the virtual simulation, you develop muscle memory for the assessment process that will serve you well in actual patient care.

    Beyond Brian Foster: Advanced Shadow Health Scenarios

    After mastering the Brian Foster chest pain case in Shadow Health, students typically progress to more complex scenarios. These might include patients with multiple comorbidities or atypical presentations of common conditions.

    The foundational skills learned through assessing Brian Foster—thorough history taking, focused physical examination, critical thinking, and clear documentation—support success in these advanced cases as well.

    Conclusion

    The Brian Foster chest pain case in Shadow Health offers nursing students a valuable opportunity to develop clinical assessment skills in a safe, virtual environment. By approaching this simulation with preparation and attention to detail, students can maximize learning and build confidence for future clinical encounters.

    Remember that the goal of the Brian Foster Shadow Health experience extends beyond achieving a high grade—it’s about developing the clinical reasoning abilities that will make you an effective healthcare provider. Each interaction with Brian Foster and careful analysis of his chest pain contributes to your growth as a nursing professional.

    Frequently Asked Questions

    How can I improve my assessment of arm pain, back pain, and neck pain when evaluating Brian Foster’s chest pain in Shadow Health?

    When assessing Brian Foster, thoroughly investigate any radiation of pain to the arms, back, or neck, as these can be important indicators of cardiac origins. Ask specific questions about when these pains occur in the chest and have Brian Foster describe their quality and intensity. Remember that pain radiation patterns often help differentiate between cardiac and non-cardiac causes.

    What techniques should I use to palpate effectively during Brian Foster’s focused exam for chest pain?

    When palpating during Brian Foster’s focused exam, use the pads of your fingers with gentle but firm pressure, systematically covering the precordial area while observing for facial expressions indicating discomfort. Pay special attention to areas where Brian Foster reports pain, and note any tenderness, masses, or abnormal pulsations that might relate to his chief complaint of chest pain.

    How should I approach questions about heartburn versus angina when Brian Foster mentions “it might just be heartburn”?

    When Brian Foster suggests his chest pain “might just be heartburn,” explore distinguishing characteristics between heartburn and angina through targeted questions about pain relief methods, relation to meals, and associated symptoms like nausea or acid reflux. Use this opportunity to educate Brian about the importance of not dismissing chest pain and the necessity of proper medical evaluation, even when it feels similar to previous heartburn episodes.

    What is the significance of documenting a history of pulmonary embolism or a history of rheumatic fever when assessing Brian Foster in Shadow Health?

    Documenting a history of pulmonary embolism or rheumatic fever is crucial as both conditions significantly impact differential diagnosis for Brian Foster’s chest pain. Pulmonary embolism history increases risk for recurrence and requires immediate consideration when chest pain presents, while rheumatic fever history suggests possible valvular heart disease that could contribute to cardiac-origin pain or complications like heart murmur, making these historical elements essential components of your comprehensive health assessment.

  • Dorothy Johnson Behavioral System Model

    Dorothy Johnson Behavioral System Model

    Dorothy E. Johnson, a renowned nursing theorist, was born on August 21, 1919, in Savannah, Georgia. Her contributions to the field of nursing, particularly through Johnson Behavioral System Model, emphasize the intricate relationship between nursing care and the behavioral functions of individuals, promoting health and balance. Johnson’s innovative approach transformed nursing practice by advocating for the integration of scientific principles with the art of nursing. This model has become a cornerstone in understanding human behavior in healthcare settings, making it a pivotal component in contemporary nursing education and practice. Johnson’s legacy is underscored by her distinguished career, during which she introduced essential concepts such as nursing diagnosis and identified key subsystems integral to her behavioral system model.

    Introduction to Dorothy E. Johnson’s Model

    Dorothy E. Johnson, a prominent nursing theorist, is known for her influential contributions to the field of nursing, particularly through her development of the Behavioral System Model. Her biography reveals a strong foundation built upon her upbringing, education, and extensive nursing career.

    Background on Dorothy E. Johnson Biography

    Dorothy Johnson’s life and career exemplify her dedication to nursing. Born on August 21, 1919, in Savannah, Georgia, her early years were marked by an environment that shaped her understanding of health challenges faced by communities with limited healthcare access. This upbringing fueled her passion for enhancing nursing care and advocating for patients.

    Early Life

    Johnson’s early life experiences were pivotal in her development as a nursing theorist. Growing up amidst societal health disparities, she developed a keen awareness of the necessity for effective nursing practices. These formative years laid the groundwork for her future endeavors in nursing education and theory formulation.

    Education

    Her academic journey commenced with an Associate’s Degree from Armstrong Junior College, followed by a Bachelor of Science in Nursing from Vanderbilt University. This rigorous academic background was further enriched by her Master of Public Health degree earned at Harvard University in 1948. The comprehensive nursing education she received fostered significant insights that would later influence her theoretical contributions.

    Career & Appointments

    Dorothy Johnson’s nursing career began as a pediatric nursing instructor at Vanderbilt University, where she served for approximately five years. Subsequently, she accepted a faculty position at UCLA, dedicating nearly 29 years to nursing education, research, and administration. Her teaching appointments allowed her to shape future generations of nurses and empower them with her theoretical knowledge. Notably, Johnson made a lasting impact on global nursing education during her sabbatical in India, where she successfully initiated a baccalaureate nursing program.

    Key Concepts of the Johnson Behavioral System Model

    Core ConceptDefinitionCharacteristicsClinical Application
    Behavioral SystemA system of patterned, repetitive, and purposeful behaviors that function as an integrated whole• Dynamic • Organized • Interdependent parts • Goal-directed • Self-maintaining • AdaptiveFoundation for nursing assessment, viewing the person holistically as a complete behavioral system
    System Balance & StabilityState of equilibrium among subsystems where all are functioning efficiently• Flexibility within stability • Efficient energy use • Predictable patterns • Effective adaptationGoal of nursing interventions is to maintain or restore system balance
    System ImbalanceDisruption in function of one or more subsystems• Inefficient behavior • Unpredictable responses • Maladaptive patterns • Energy misuseTriggers nursing assessment and intervention

    The Seven Behavioral Subsystems

    SubsystemPurposeKey BehaviorsFunctional RequirementsImbalance IndicatorsNursing Interventions
    Attachment/AffiliativeSocial inclusion and bond formation• Forming relationships • Social interaction • Intimacy behaviors • Belonging• Security in relationships • Opportunities for meaningful connection • Social stimulation• Social isolation • Difficulty forming attachments • Excessive dependency • Social withdrawal• Facilitate social connections • Promote therapeutic relationships • Support family involvement
    DependencyObtaining nurturing and approval• Help-seeking • Approval-seeking • Care-receiving behavior• Reliable caregivers • Appropriate assistance • Validation• Excessive dependency • Inability to seek help • Rejection of assistance• Provide appropriate assistance • Encourage self-care when possible • Establish boundaries
    IngestiveFood and fluid intake• Eating • Drinking • Food selection • Appetite regulation• Nutritional adequacy • Eating satisfaction • Cultural appropriateness• Poor appetite • Malnutrition • Disordered eating • Inadequate fluid intake• Nutritional assessment • Meal planning • Feeding assistance • Hydration management
    EliminativeExcretion of waste products• Bowel elimination • Urination • Sweating • Expelling carbon dioxide• Regular patterns • Privacy • Comfort • Accessibility• Constipation • Incontinence • Retention • Irregular patterns• Bowel/bladder training • Elimination monitoring • Environmental adaptations
    SexualProcreation and gratification• Sexual identity expression • Intimacy • Reproductive behaviors • Sexual response• Gender identity support • Privacy • Sexual health education • Respect for values• Sexual dysfunction • Identity conflicts • Reproductive disorders• Sexual health education • Respect privacy • Address concerns sensitively
    Aggressive/ProtectiveSelf-protection and preservation• Self-defense • Boundary setting • Protection of values • Assertion of rights• Safety • Ability to protect self • Constructive expression• Excessive aggression • Inability to defend self • Self-harm • Risk-taking• Safety planning • Boundary education • Anger management • Protective environments
    AchievementEnvironmental mastery and competence• Skill development • Intellectual pursuits • Goal-directed activities • Creative expression• Challenges • Recognition • Opportunities to achieve • Skill development• Underachievement • Perfectionism • Lack of motivation • Skill deficits• Realistic goal setting • Skill development • Recognition of achievements • Adaptive equipment

    Functional Requirements for All Subsystems

    RequirementDefinitionExamplesNursing Implications
    ProtectionShielding from harmful influences• Safe environment • Health maintenance • Disease preventionNurses implement protective measures to prevent system damage
    NurturanceProviding input needed for growth• Educational support • Emotional nourishment • Resource provisionNurses support growth of each subsystem through targeted interventions
    StimulationPromoting appropriate behavioral responses• Sensory input • Challenges • Activity promotionNurses provide appropriate stimulation to activate subsystems

    Nursing Process in JBSM

    Process StepFocusActivitiesGoals
    AssessmentIdentify subsystem status and function• Observe behavioral patterns • Interview about subsystem function • Evaluate relationships between subsystemsComprehensive understanding of behavioral system status
    DiagnosisDetermine causes of system imbalance• Identify structural issues (insufficient, excessive, or restrictive environment) • Recognize functional problems (impaired use or development)Clear identification of behavioral system problems
    InterventionApply external regulatory mechanisms• Impose (restrict behaviors) • Teach (new behaviors) • Support (existing adaptive behaviors)Restoration of behavioral system balance
    EvaluationMeasure restoration of balance• Reassess subsystem functioning • Monitor stability over time • Evaluate integration of subsystemsDocument progress toward behavioral system equilibrium

    External Regulatory Mechanisms

    MechanismPurposeExamplesClinical Application
    ImpositionEstablish or reinforce behavioral limits• Activity restrictions • Dietary limitations • Safety protocolsUsed when patient cannot self-regulate behaviors
    TeachingProvide knowledge for new behaviors• Health education • Skill development • Decision-making guidanceUsed to develop new, more adaptive behaviors
    SupportMaintain existing adaptive behaviors• Positive reinforcement • Environmental modifications • Resource provisionUsed to strengthen functional behaviors

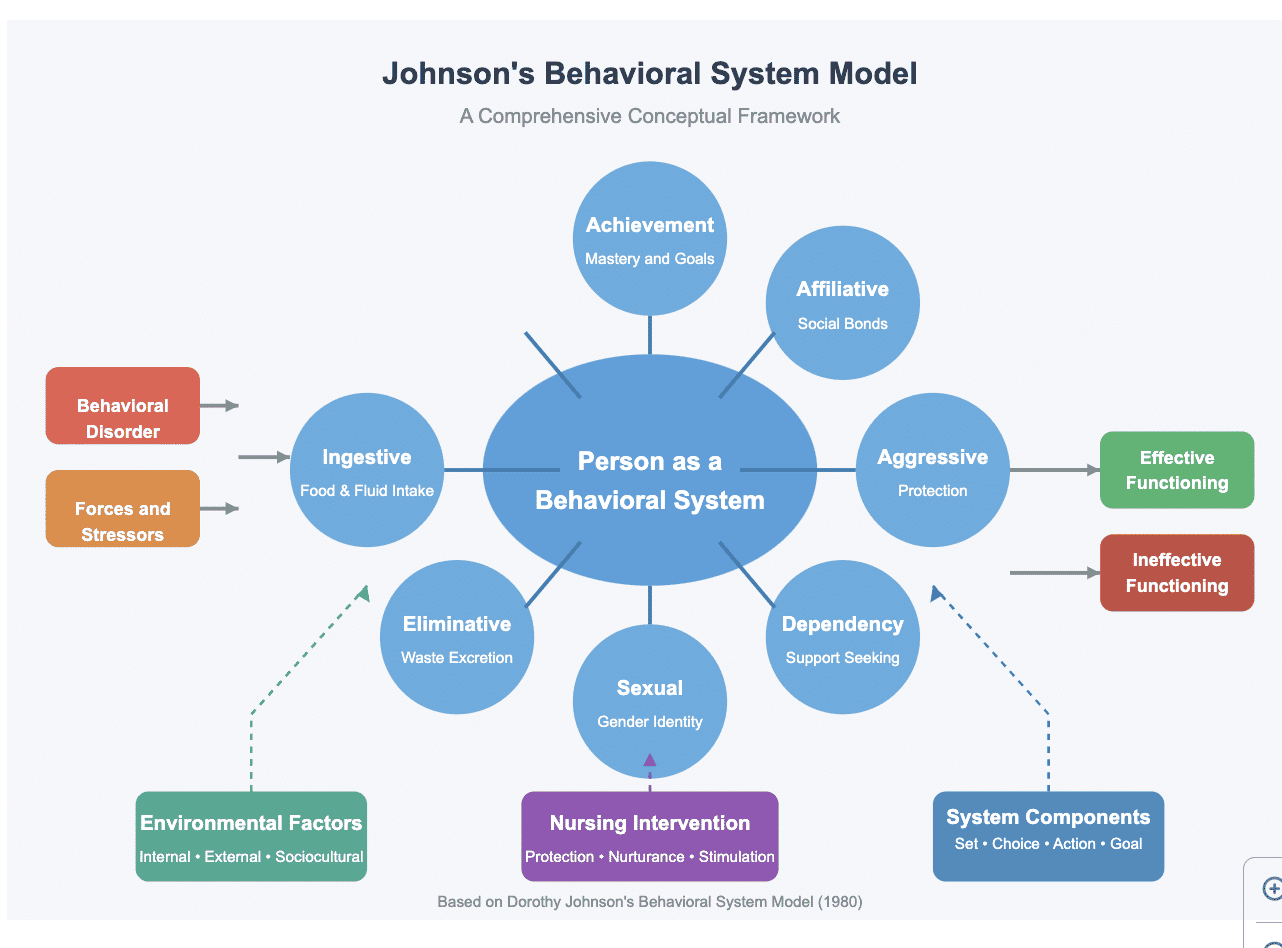
    The Behavioral System Model proposed by Dorothy E. Johnson represents an essential facet of modern nursing theory, focusing on the interplay between various behavioral systems and their impact on patient health. This model places a premium on understanding the organized and dynamic nature of behaviors that each individual exhibits. The following sections will elucidate the concept definition of behavioral systems and outline the critical behavioral system model components essential for nursing practice.

    Definition of Behavioral Systems

    Behavioral systems refer to structured patterns of behavior that coexist within individuals, influenced by biological, psychological, and social factors. Through the lens of nursing theory, these systems emphasize the interaction and interdependence of behaviors, asserting that health outcomes are significantly influenced by how these behaviors are organized. Johnson’s model articulates that understanding these systems is critical for effective nursing care, as they help healthcare professionals identify areas where patients may be experiencing imbalance and require support.

    Components of the Johnson Behavioral System Model

    Johnson Behavioral System Model
    Johnson Behavioral System Model

    Within the Johnson Behavioral System Model, several components emerge that serve to categorize human behavior into distinct subsystems. Johnson identified seven behavioral system model components:

    • Attachment
    • Achievement
    • Aggressive
    • Dependence
    • Sexual
    • Ingestive
    • Eliminative

    Each of these subsystems possesses three functional requirements necessary for maintaining balance: protection from harmful influences, nurturing through appropriate environmental input, and stimulation for growth. Johnson’s insights into the behavioral system model components illuminate how these subsystems can interact and influence each other, essential for restoring equilibrium when disruptions occur. This holistic understanding is pivotal in nursing practices, where diverse factors converge to shape patient h

    Within the Johnson Behavioral System Model, several components emerge that serve to categorize human behavior into distinct subsystems. Johnson identified seven behavioral system model components:

    • Attachment
    • Achievement
    • Aggressive
    • Dependence
    • Sexual
    • Ingestive
    • Eliminative

    Each of these subsystems possesses three functional requirements necessary for maintaining balance: protection from harmful influences, nurturing through appropriate environmental input, and stimulation for growth. Johnson’s insights into the behavioral system model components illuminate how these subsystems can interact and influence each other, essential for restoring equilibrium when disruptions occur. This holistic understanding is pivotal in nursing practices, where diverse factors converge to shape patient health and wellbeing.

    The Role of the Nurse in the Model

    Johnson’s Behavioral System Model positions nursing as a fundamental component of behavioral science, highlighting its critical role in understanding patient behavior and influencing health outcomes. The model suggests that to fulfill their nursing responsibilities effectively, nurses must engage with the various behavioral subsystems that govern patients’ actions. This requires a nuanced approach that balances scientific knowledge with compassionate care, enabling nurses to address both physical and emotional dimensions of health.

    Nursing as a Behavioral Science

    The integration of nursing with behavioral science enables practitioners to observe and respond to patient needs more effectively. Nurses analyze behaviors that may indicate underlying health issues, applying research-based knowledge to foster a supportive environment conducive to healing. In this context, the nursing role encompasses not only the assessment of patients but also the creation of individualized care plans that promote optimal functioning across the identified subsystems. By focusing on holistic assessments, nurses can pinpoint interconnected problems and facilitate improved health outcomes for their patients.

    Responsibilities of the Nurse Practitioner

    Nurse practitioners carry substantial responsibilities in executing the principles outlined in Johnson’s model. Primarily, they evaluate the balance within a patient’s behavioral system, identifying any disruptions that could stem from internal stressors such as anxiety or external factors like environmental influences. Continuous assessment is vital as it allows for flexibility in care plans, ensuring they evolve alongside the patient’s needs. Additionally, nurse practitioner roles include the collaboration with interdisciplinary teams, which enhances the effectiveness of interventions aimed at restoring stability and promoting holistic well-being. This commitment to addressing both medical and behavioral challenges underscores the critical nature of nursing practice in achieving healthy patient outcomes.

    Johnson Behavioral System Model: Seven Subsystems Explained

    Dorothy Johnson viewed each person as a behavioral system made up of seven interconnected subsystems. Think of these subsystems as seven essential parts of a person that work together to maintain balance and health. When one subsystem is affected, it impacts the others—much like how a mobile hanging above a baby’s crib will tilt completely if just one piece is moved.

    Before we dive into each subsystem, remember that:

    • Each subsystem has a purpose (what it aims to accomplish)
    • Each has functional requirements (what it needs to work properly)
    • Each displays behaviors (observable actions)
    • Each requires nursing care when imbalanced

    1. Attachment and Affiliative Subsystem: Building Meaningful Connections

    What It Is

    This subsystem governs how we form social bonds and maintain relationships with others. It’s about our need to belong and connect.

    Real-World Example

    Meet Mrs. Chen: An 82-year-old widow hospitalized for pneumonia. She rarely has visitors and appears withdrawn. Nurses notice she brightens significantly when they spend extra time talking with her during medication administration.

    Functional Assessment

    • Healthy Function: Mrs. Chen maintained close relationships with her church group before hospitalization
    • Dysfunction: Isolation in hospital has disrupted her attachment patterns

    Nursing Application

    1. Personalized Care: The nurse assigns the same staff to Mrs. Chen when possible
    2. Environmental Adjustment: Places Mrs. Chen in a semi-private room with a compatible roommate
    3. Family Involvement: Coordinates video calls with her church friends
    4. Therapeutic Communication: Schedules brief but meaningful daily conversations

    Result

    Mrs. Chen develops a trusting relationship with her care team, participates more actively in recovery, and experiences reduced anxiety—demonstrating how supporting the attachment subsystem promotes healing.

    2. Dependency Subsystem: Balancing Help and Self-Reliance

    What It Is

    This subsystem controls behaviors related to caretaking, assistance, and the balance between dependence and independence.

    Real-World Example

    Meet James: A 45-year-old man recovering from a stroke who is frustrated by his new limitations. He refuses help with activities he cannot safely perform alone, saying “I don’t need anyone’s help!”

    Functional Assessment

    • Healthy Function: Before his stroke, James appropriately sought help for complex tasks while maintaining independence
    • Dysfunction: Now alternates between refusing necessary assistance and becoming frustrated when tasks are difficult

    Nursing Application

    1. Gradual Independence: The nurse creates a schedule where James does more for himself each day
    2. Reframing Assistance: Explains how accepting help now leads to greater independence later
    3. Partnership Approach: “Let’s work on this together” instead of “Let me do this for you”
    4. Celebrating Milestones: Acknowledges each new skill James masters

    Result

    James begins to accept necessary help while working toward independence, showing how properly supporting the dependency subsystem creates a healthy balance between assistance and autonomy.

    3. Ingestive Subsystem: Nourishing the Body and Mind

    What It Is

    This subsystem manages behaviors related to eating, drinking, and taking in nourishment—both what and how we consume.

    Real-World Example

    Meet Sophia: A 16-year-old with newly diagnosed diabetes who is struggling with dietary restrictions. She secretly eats forbidden foods and then lies about her blood sugar readings.

    Functional Assessment

    • Healthy Function: Previously ate a varied diet with regular meal patterns
    • Dysfunction: Now exhibits disordered eating patterns and resistance to dietary guidelines

    Nursing Application

    1. Education Through Exploration: The nurse helps Sophia discover diabetes-friendly versions of favorite foods
    2. Psychological Support: Addresses the emotional aspects of dietary changes
    3. Practical Skills: Teaches carbohydrate counting instead of rigid “forbidden foods” rules
    4. Social Strategies: Role-plays how to handle food-centered social situations

    Result

    Sophia develops a healthier relationship with food while managing her diabetes appropriately, demonstrating how addressing both physical and psychological aspects of the ingestive subsystem leads to better outcomes.

    4. Eliminative Subsystem: Managing Waste Processes with Dignity

    What It Is

    This subsystem regulates behaviors related to bodily excretion—how we eliminate waste biologically, socially, and psychologically.

    Real-World Example

    Meet Mr. Rodriguez: A 70-year-old man hospitalized after prostate surgery who is now incontinent. He refuses to leave his room or see visitors due to embarrassment.

    Functional Assessment

    • Healthy Function: Previously had normal elimination patterns and no social limitations
    • Dysfunction: Now experiencing incontinence and social withdrawal due to shame

    Nursing Application

    1. Preserving Dignity: The nurse ensures privacy during care and uses discreet incontinence products
    2. Scheduled Voiding: Implements a timed toileting program
    3. Environmental Control: Places his room near the bathroom and creates clear access
    4. Normalization: Explains that temporary incontinence is common after his procedure

    Result

    Mr. Rodriguez regains confidence to participate in physical therapy and accept visitors, showing how addressing both physical and psychological aspects of the eliminative subsystem preserves dignity and promotes recovery.

    5. Sexual Subsystem: Acknowledging Identity and Intimacy Needs

    What It Is

    This subsystem encompasses behaviors related to gender identity, sexual expression, and reproduction.

    Real-World Example

    Meet Maria: A 35-year-old woman recovering from a mastectomy who expresses concerns about her relationship with her husband and her self-image.

    Functional Assessment

    • Healthy Function: Previously had positive body image and satisfying intimate relationship
    • Dysfunction: Now experiencing altered body image and anxiety about intimacy

    Nursing Application

    1. Open Communication: The nurse creates opportunities to discuss concerns about intimacy and relationship changes
    2. Body Image Support: Teaches Maria how to care for her surgical site while acknowledging emotional responses
    3. Resource Connection: Provides information about support groups and reconstruction options
    4. Partner Inclusion: With Maria’s permission, includes her husband in discussions about adjustment

    Result

    Maria begins to adapt to body changes and communicates more openly with her husband, demonstrating how supporting the sexual subsystem addresses both physical adjustments and relational aspects of health.

    6. Aggressive/Protective Subsystem: Safeguarding Self and Values

    What It Is

    This subsystem manages behaviors related to self-protection, setting boundaries, and responding to threats—both real and perceived.

    Real-World Example

    Meet Devon: A 19-year-old admitted after a car accident who becomes verbally aggressive when healthcare decisions are made without his input.

    Functional Assessment

    • Healthy Function: Previously used appropriate assertiveness to protect his interests
    • Dysfunction: Now displaying excessive aggression due to feeling threatened and powerless

    Nursing Application

    1. Control Restoration: The nurse involves Devon in care planning: “What time would you prefer to take your medication?”
    2. Boundary Education: Teaches the difference between assertiveness and aggression
    3. Predictability: Explains procedures before they happen to reduce threat perception
    4. Validation: Acknowledges his right to have opinions about his care

    Result

    Devon’s aggressive outbursts decrease as he gains appropriate control over his care, showing how supporting healthy protective behaviors while redirecting unhelpful aggression balances this subsystem.

    7. Achievement Subsystem: Mastering Skills and Environment

    What It Is

    This subsystem directs behaviors related to accomplishment, intellectual mastery, and skill development.

    Real-World Example

    Meet Aisha: A 50-year-old teacher who has had a stroke affecting her language abilities. She becomes depressed when unable to read or communicate effectively.

    Functional Assessment

    • Healthy Function: Previously derived significant satisfaction from intellectual accomplishments and teaching
    • Dysfunction: Now experiencing frustration and loss of identity due to communication difficulties

    Nursing Application

    1. Modified Goals: The nurse helps break rehabilitation into achievable milestones
    2. Alternative Achievements: Identifies non-verbal accomplishments Aisha can master
    3. Progress Visibility: Creates a visual chart showing improvement over time
    4. Strength Focus: Emphasizes abilities retained rather than only what was lost

    Result

    Aisha engages more actively in speech therapy and finds new ways to experience achievement, demonstrating how supporting this subsystem maintains motivation and identity during recovery.

    How These Subsystems Work Together: A Holistic View

    Interconnected Nature

    Consider how these subsystems overlap and influence each other:

    Case Study: Mr. Jackson Mr. Jackson, a 60-year-old with newly diagnosed heart failure, shows how disturbance in one subsystem affects others:

    • Ingestive subsystem is affected by sodium restrictions
    • This impacts his achievement subsystem as he can no longer cook favorite family recipes
    • His attachment subsystem is strained as social gatherings revolved around these meals
    • His aggressive/protective subsystem activates as he feels his identity threatened
    • His dependency subsystem struggles with new reliance on medications
    • His eliminative subsystem is affected by diuretics
    • His sexual subsystem faces challenges due to medication side effects and fatigue

    Nursing Application to Multiple Subsystems

    Effective nursing care addresses these connections:

    1. Holistic Assessment: Evaluate all subsystems, not just the most obvious one
    2. Prioritization: Address the most critical subsystem first while planning for others
    3. Ripple Effect Planning: Anticipate how interventions in one area will affect others
    4. Patient Perspective: Ask which subsystem disruption matters most to the patient

    Practical Application for Nursing Students

    Assessment Questions for Each Subsystem

    Attachment:

    • “Who are the important people in your life?”
    • “How has your illness affected your relationships?”

    Dependency:

    • “What activities do you need help with now?”
    • “How do you feel about asking for assistance?”

    Ingestive:

    • “Describe your typical eating patterns.”
    • “Have you noticed any changes in appetite or enjoyment of food?”

    Eliminative:

    • “Have you experienced any changes in your bowel or bladder habits?”
    • “Are you comfortable using the bathroom facilities here?”

    Sexual:

    • “Has your condition affected how you see yourself?”
    • “Do you have concerns about how this condition might affect intimate relationships?”

    Aggressive/Protective:

    • “What helps you feel safe and in control?”
    • “How do you typically respond when you feel threatened?”

    Achievement:

    • “What activities give you a sense of accomplishment?”
    • “How has your condition affected your ability to do things that matter to you?”

    Creating Nursing Care Plans Using Johnson’s Model

    • Step 1: Identify which subsystems are imbalanced
    • Step 2: Determine what each subsystem needs (protection, nurturance, stimulation)
    • Step 3: Plan interventions that specifically address those needs
    • Step 4: Evaluate effectiveness by observing behavioral changes

    Example: For Mr. Jackson (heart failure patient mentioned earlier):

    • Priority Subsystem: Ingestive
    • Need: Knowledge about heart-healthy eating while preserving enjoyment
    • Intervention: Work with dietitian to modify favorite recipes to be heart-healthy
    • Evaluation: Mr. Jackson demonstrates understanding by creating a meal plan that follows restrictions while maintaining satisfaction

    Dorothy Johnson’s Behavioral System Model offers a structured way to understand the whole person—not just their medical diagnosis. By recognizing how these seven subsystems interact, nurses can:

    1. Provide truly holistic care that addresses all aspects of human functioning
    2. Anticipate problems before they develop by noticing early subsystem imbalances
    3. Create interventions that promote balance rather than just treating symptoms
    4. Recognize that behavior has meaning and serves a purpose in maintaining balance

    Remember that each patient’s behavioral system is unique, shaped by their culture, experiences, and values. The art of nursing using Johnson’s model lies in understanding each patient’s individual patterns and supporting their return to their optimal balance.

    Furthermore, Johnson Behavioral System Model can be effectively juxtaposed against other nursing theories, including Orem’s Self-Care Deficit Theory. While Orem emphasizes the importance of individual self-care abilities, Johnson’s framework places a greater emphasis on the nurse’s role in achieving behavioral equilibrium for their patients. This Johnson model comparison allows for deeper insights into varying approaches to nursing care, reinforcing the necessity for adaptable strategies that meet diverse patient needs. The exploration of these nursing theories further solidifies the importance of acknowledging both self-care capabilities and the facilitative role of nursing in managing patient behaviors and health outcomes.

    FAQ

    What is Dorothy E. Johnson’s Behavioral System Model?

    The Behavioral System Model developed by Dorothy E. Johnson emphasizes the relationship between nursing care and individuals’ behavioral functions to promote health and equilibrium. It advocates a holistic approach to nursing that integrates both the science and art of care.

    How does Johnson’s model categorize human behavior?

    Johnson’s model categorizes human behavior into seven distinct subsystems, each addressing a specific function and goal. These subsystems facilitate the understanding of how behaviors interconnect and influence health outcomes.

    What role do nurses play in the Behavioral System Model?

    Nurses are tasked with assessing behavioral systems, implementing interventions, and evaluating patient outcomes. They are responsible for creating a therapeutic environment that empowers patients to modify their behaviors for better health.

    How does the Behavioral System Model relate to patient autonomy?

    Johnson’s model underscores the importance of encouraging patient autonomy while recognizing their needs for support. This balance is critical for recovery and self-management, making it essential for nurses to foster independence during care.

    What are the practical applications of Johnson’s Behavioral System Model?

    The model’s framework aids nurses in systematizing patient assessments and interventions, ensuring that care is patient-centered and responsive to behavioral needs, ultimately facilitating recovery in clinical settings.

    How does the Behavioral System Model integrate into nursing education?

    By incorporating Johnson’s model into nursing curricula, students are equipped to analyze patient behaviors better and design effective care plans that align with holistic health promotion.

    How does Johnson’s model compare to Orem’s Self-Care Deficit Theory?

    While Orem’s theory focuses on individuals’ self-care abilities, Johnson emphasizes the role of nurses in facilitating behavioral equilibrium. Both theories contribute to a more comprehensive approach to patient care.

  • SOAP Note Example NP – Best 3 Examples

    SOAP Note Example NP – Pediatric Patient

    S: Subjective

    Chief Complaint: “My daughter has had ear pain and fever for two days.” (Parent report)
    HPI:

    • 5-year-old female with 2-day history of right ear pain, described as “sharp,” rated 6/10.
    • Associated symptoms: Fever (max 101.3°F), fussiness, difficulty sleeping, and decreased appetite.
    • Tugging at right ear. No vomiting, diarrhea, or cough.
    • Recent upper respiratory infection (URI) resolved 1 week ago.
      PMH: Full-term birth, no chronic illnesses.
      Immunizations: Up to date, including PCV13 and influenza.
      Allergies: NKDA.
      Family History: No history of recurrent ear infections.
      Social: Lives with parents and siblings; attends preschool.

    O: Objective

    Vital Signs:

    • Temp: 101.3°F (oral)
    • HR: 110 bpm
    • RR: 22/min
    • SpO2: 98% RA
    • Weight: 18 kg (50th percentile)

    Physical Exam:

    • General: Alert but fussy.
    • HEENT:
      • Right ear: Tympanic membrane erythematous, bulging, loss of landmarks, decreased mobility on pneumatic otoscopy.
      • Left ear: Normal.
      • Throat: Mild erythema, no exudate.
      • Nose: Clear, no discharge.
    • Neck: No lymphadenopathy.
    • Lungs: Clear bilaterally, no wheezing.
    • Skin: No rash.

    A: Assessment

    Primary Diagnosis:

    • Acute Otitis Media (AOM), Right Ear (ICD-10: H66.91)
      • Rationale:
        • Clinical findings: Bulging, erythematous TM with decreased mobility (key diagnostic criteria for AOM).
        • Supportive symptoms: Acute onset ear pain, fever, recent URI.

    Differential Diagnoses:

    1. Otitis Externa (ICD-10: H60.90)
      • Rationale for Exclusion: Absence of ear canal edema, pain on tragus palpation, or history of swimming.
    2. Viral Pharyngitis (ICD-10: J02.9)
      • Rationale for Exclusion: Mild throat erythema without exudate or tonsillar swelling; primary symptom is ear pain.
    3. Teething (ICD-10: K00.7)
      • Rationale for Exclusion: Fever >100.4°F and ear findings inconsistent with teething.

    P: Plan

    1. Antibiotic Therapy:
      • Amoxicillin 45 mg/kg/day divided BID x10 days (18 kg → 405 mg BID).
      • Rationale: First-line treatment for AOM in patients without penicillin allergy. High-dose amoxicillin covers S. pneumoniae and H. influenzae.
    2. Symptom Management:
      • Ibuprofen 10 mg/kg every 6–8 hours PRN pain/fever.
      • Acetaminophen 15 mg/kg every 4–6 hours PRN (if ibuprofen contraindicated).
    3. Follow-Up:
      • Re-evaluate in 10 days to confirm resolution.
      • Return immediately if fever persists >48 hours, worsening pain, or hearing loss.
    4. Parent Education:
      • Counsel on completing antibiotics even if symptoms improve.
      • Avoid bottle propping to reduce aspiration risk.
      • Use analgesics as needed for comfort.
    5. Prevention:
      • Encourage hand hygiene and avoid sick contacts.

    Rationale for ICD-10 Selection:

    • H66.91: Specific to right ear AOM (laterality improves coding accuracy).
    • Differentials excluded based on history/exam findings to avoid misclassification.

    Clinical Decision-Making:

    • AOM diagnosis aligns with AAP criteria (acute symptoms + middle ear effusion). Immediate antibiotics chosen due to age <6 years, bilateral symptoms excluded, and significant discomfort.

    Example SOAP Note Nurse Practitioners – Teen Patient

    SUBJECTIVE:

    Chief Complaint:

    “I’ve been feeling really sad and tired all the time for the past 3 months”

    History of Present Illness: Alex is a 16-year-old male who presents with mother for evaluation of persistent sadness, fatigue, and academic decline over the past 3 months. Patient reports feeling sad “most of the day, almost every day,” with decreased interest in basketball and video games, which he previously enjoyed. Reports difficulty falling asleep and staying asleep, waking early at 4-5 AM unable to return to sleep. Has experienced a 10-pound unintentional weight loss over the past 2 months. Describes feeling “worthless” and has trouble concentrating on schoolwork. Denies suicidal ideation, plan, or intent. No prior history of self-harm. No manic episodes.

    Past Medical History: No significant medical history
    Past Psychiatric History: None
    Medications: None
    Allergies: NKDA
    Family History: Mother with history of depression and anxiety; maternal grandmother with history of depression
    Social History: Lives with mother and younger sister. Parents divorced 6 months ago. Changed schools 4 months ago due to move. Reports difficulty making new friends. Denies alcohol, tobacco, or substance use.
    Review of Systems: Constitutional: Fatigue, weight loss. Psych: As above. All other systems negative.

    OBJECTIVE:

    Vital Signs:
    BP 118/72, HR 78, RR 16, Temp 98.6°F, Ht 5’10”, Wt 155 lbs (down from 165 lbs 2 months ago)

    Physical Examination:

    • General: Alert, appropriately dressed adolescent male who appears stated age. Makes minimal eye contact. Psychomotor retardation noted.
    • HEENT: Normocephalic, atraumatic. No thyromegaly.
    • Cardiovascular: Regular rate and rhythm, no murmurs
    • Respiratory: Clear to auscultation bilaterally
    • Abdominal: Soft, non-tender, no organomegaly
    • Neurological: CN II-XII intact, no focal deficits
    • Psychiatric: Affect flat, mood depressed. Speech slow in rate and volume. Thought process linear. No evidence of hallucinations or delusions. No suicidal or homicidal ideation. Oriented x3. Good insight and judgment.

    PHQ-9 Score: 18 (Moderately severe depression)

    Laboratory Results:

    • TSH: 2.1 mIU/L (normal range: 0.4-4.0 mIU/L)
    • CBC: Within normal limits
    • Comprehensive Metabolic Panel: Within normal limits
    • Urine drug screen: Negative

    ASSESSMENT:

    Primary Diagnosis:

    • Major Depressive Disorder, single episode, moderate (F32.1)
      Rationale: Patient meets DSM-5 criteria with depressed mood, anhedonia, significant weight loss, insomnia, psychomotor retardation, fatigue, feelings of worthlessness, and diminished ability to concentrate for > 2 months. Symptoms are causing significant impairment in academic and social functioning. PHQ-9 score indicates moderately severe depression.

    Differential Diagnoses:

    1. Adjustment Disorder with Depressed Mood (F43.21)
      Rationale: Recent stressors include parental divorce and school change. However, symptom severity and duration exceed typical adjustment reaction.
    2. Persistent Depressive Disorder (Dysthymia) (F34.1)
      Rationale: Symptoms have not persisted for ≥ 1 year as required for this diagnosis in adolescents.
    3. Bipolar Disorder (F31.9)
      Rationale: No history of manic or hypomanic episodes.
    4. Hypothyroidism (E03.9)
      Rationale: Some symptoms overlap, but normal TSH rules this out.
    5. Substance-Induced Depressive Disorder (F19.94)
      Rationale: Negative drug screen and denial of substance use make this less likely.

    PLAN:

    Psychotherapy:

    • Refer to adolescent therapist for Cognitive Behavioral Therapy (CBT), weekly sessions
    • Rationale: Evidence-based first-line treatment for adolescent depression; helps address negative thought patterns and develop coping skills

    Medication:

    • Start Fluoxetine 10 mg PO daily for 1 week, then increase to 20 mg daily
    • Rationale: FDA-approved SSRI for adolescent depression; start low and titrate slowly to minimize side effects
    • Discussed black box warning regarding increased risk of suicidal thoughts/behaviors in adolescents
    • Parent and patient educated on side effects, benefits, and risks

    Safety Plan:

    • Developed safety plan with patient and mother
    • Provided crisis hotline numbers and local emergency resources
    • Rationale: Essential component of depression management even in absence of current suicidal ideation

    Monitoring:

    • Follow-up in 1 week to assess for side effects and symptom changes
    • Repeat PHQ-9 at each visit to track symptom improvement
    • Rationale: Close monitoring needed during initiation of treatment, especially in adolescents

    School Accommodations:

    • Provided letter for school counselor recommending temporary accommodations
    • Rationale: Support academic functioning during acute phase of illness

    Family Support:

    • Provided information on parent support groups and family therapy options
    • Rationale: Family involvement improves outcomes in adolescent depression

    Lifestyle Modifications:

    • Encouraged regular exercise, sleep hygiene, and healthy eating
    • Rationale: Adjunctive non-pharmacological interventions with evidence supporting efficacy in depression

    Next Appointment: 1 week from today
    Duration: 45 minutes

    Nurse Practitioner SOAP Note Example – Major Depressive Disorder

    SOAP Note Example NP - Best 3 Examples
    SOAP Note Example NP – Best 3 Examples

    Subjective:

    CC (Chief Complaint):
    45-year-old Caucasian female presents with complaints of persistent low mood, fatigue, and difficulty concentrating over the past six months. She reports feeling “overwhelmed and exhausted all the time,” with decreased interest in activities she used to enjoy.

    HPI:

    • Onset: Symptoms began approximately six months ago after experiencing increased work-related stress and the loss of a close family member.
    • Duration: Symptoms have been persistent, occurring nearly every day.
    • Character:
      • Depressed mood, frequent crying spells.
      • Difficulty sleeping, early morning awakening.
      • Feelings of worthlessness and guilt, especially about not being “productive enough.”
      • Increased fatigue despite adequate sleep.
      • Decreased motivation and enjoyment in hobbies.
      • Reports some unintentional weight loss (approximately 8 lbs in the past 3 months).
      • Concentration issues affecting job performance.
      • No suicidal ideation currently but states, “I feel like I don’t have a purpose anymore.”

    Substance Current Use:

    • Drinks 1-2 glasses of wine on weekends but denies excessive alcohol use.
    • Smoked cigarettes in her 20s but quit 10 years ago.
    • No history of illicit drug use.

    Medical History:

    • Current Medications: None
    • Allergies: No known drug allergies
    • Reproductive Hx: Menopausal symptoms started in the last year, with occasional hot flashes and night sweats.

    ROS:

    • GENERAL: Reports weight loss, fatigue.
    • HEENT: No vision changes, no tinnitus.
    • SKIN: No rashes, itching, or abnormal bruising.
    • CARDIOVASCULAR: No chest pain, palpitations.
    • RESPIRATORY: No shortness of breath or cough.
    • GASTROINTESTINAL: Reports mild nausea, occasional loss of appetite.
    • GENITOURINARY: No dysuria, normal urine output.
    • NEUROLOGICAL: No dizziness, headaches, or focal deficits.
    • MUSCULOSKELETAL: No joint pain or swelling.
    • ENDOCRINOLOGIC: No excessive thirst or urination.

    Objective:

    Vital Signs:

    • BP: 124/78 mmHg
    • HR: 72 bpm
    • RR: 16 bpm
    • Temp: 98.2°F
    • O2 Sat: 98% on room air
    • BMI: 24.5 kg/m²

    Mental Status Examination:

    • Appearance: Well-groomed, appropriate attire for weather.
    • Gait: Normal.
    • Behavior: Cooperative, but appears tired and downcast.
    • Eye Contact: Fair, intermittently downcast.
    • Speech Rate & Tone: Soft, slow, but articulate.
    • Mood: Depressed.
    • Affect: Constricted, congruent with mood.
    • Thought Process: Linear, logical.
    • Thought Content: No delusions, no psychotic features.
    • Suicide Ideation: Denies, but reports feelings of hopelessness.
    • Homicidal Ideation: None.
    • Perceptual Disturbances: None.
    • Insight & Judgment: Fair.
    • Fund of Knowledge: Appropriate.
    • Cognition: Alert, oriented to person, place, and situation.

    Diagnostic Results:

    • PHQ-9 Score: 18 (Moderate-Severe Depression)
    • TSH & T4: Pending (rule out hypothyroidism contribution).
    • CMP: Pending (assess nutritional and metabolic status).

    Assessment:

    Primary Diagnosis:

    🩺 F32.1 – Major Depressive Disorder, Single Episode, Moderate

    • Rationale: Patient meets DSM-5 criteria for Major Depressive Disorder (MDD) with symptoms persisting for over 6 months, including depressed mood, anhedonia, fatigue, changes in sleep and appetite, difficulty concentrating, and feelings of worthlessness. The PHQ-9 score supports moderate to severe depression.

    Differential Diagnoses:

    1. F41.1 – Generalized Anxiety Disorder (GAD)
      • Patient reports excessive worry, fatigue, and difficulty concentrating, which overlap with GAD. However, her symptoms are primarily depressive, not excessive worry and fear.
    2. E66.9 – Menopausal Symptoms with Mood Changes
      • Patient has started experiencing menopausal symptoms (hot flashes, night sweats). While menopause can contribute to mood instability, the duration and severity of symptoms suggest an independent depressive disorder.
    3. F34.1 – Persistent Depressive Disorder (Dysthymia)
      • Dysthymia is diagnosed when symptoms persist for at least 2 years. This patient’s depressive symptoms have lasted six months, making Major Depressive Disorder the more appropriate diagnosis.
    4. E03.9 – Hypothyroidism, Unspecified
      • Hypothyroidism can mimic depression (fatigue, weight changes, concentration issues). TSH and T4 testing is pending to rule this out.
    5. F43.21 – Adjustment Disorder with Depressed Mood
      • This diagnosis is considered but ruled out because the patient’s symptoms are more pervasive and persistent than what is typically seen in adjustment disorder, which resolves within 6 months after a stressor.

    Plan (Treatment & Rationale):

    1. Pharmacologic Treatment:

    • Start Sertraline (Zoloft) 50 mg PO daily
      • First-line SSRI for depression, low side effect profile, effective for moderate-severe MDD.
      • Patient educated on delayed onset of action (2-4 weeks for effect).
      • Side effects discussed (nausea, headache, sexual dysfunction).
      • Will follow up in 4 weeks to assess response and adjust dose if needed.

    2. Psychotherapy Referral:

    • Cognitive Behavioral Therapy (CBT) recommended
      • Proven effective in restructuring negative thoughts and improving coping mechanisms.
      • Encouraged patient to engage in therapy 1x/week.

    3. Lifestyle & Holistic Interventions:

    • Exercise: Encourage 30 minutes of moderate exercise (walking, yoga) 5x/week to help with mood.
    • Sleep Hygiene: Maintain a consistent bedtime routine, avoid screens before bed.
    • Mindfulness & Relaxation Techniques: Journaling, meditation, deep breathing exercises.

    4. Nutritional Support:

    • Increase omega-3 fatty acids (salmon, flaxseeds, walnuts) for brain health.
    • Reduce caffeine/alcohol intake to improve sleep and anxiety symptoms.
    • Ensure adequate hydration and balanced diet.

    5. Lab Follow-Up:

    • TSH/T4 Results Pending: If abnormal, consider endocrinology referral.
    • CMP: Check for metabolic/nutritional deficiencies.

    6. Follow-Up Plan:

    • Follow-up in 4 weeks to assess medication response and side effects.
    • Check PHQ-9 score for improvement.
    • Assess sleep, appetite, and suicidal ideation.
    • If no improvement in 6-8 weeks, consider increasing Sertraline dose or switching to an SNRI (e.g., Venlafaxine).

    7. Safety & Crisis Planning:

    • Patient educated on warning signs for worsening depression and suicidal thoughts.
    • Crisis hotline provided: 988 Suicide & Crisis Lifeline.
    • Patient instructed to seek immediate help if experiencing severe suicidal thoughts.

  • SBAR Nursing: Situation, Background, Assessment and Recommendation Example

    Introduction to SBAR Nursing

    SBAR is a structured communication framework that can help teams share information about the condition of a patient or team member or about another issue your team needs to address. For nurses working in today’s complex healthcare environments, effective communication is not just a skill—it’s a necessity. The SBAR nursing communication tool has revolutionized how healthcare professionals share critical patient information. As an RN, mastering this structured communication technique can dramatically improve patient outcomes and enhance interprofessional relationships.

    What is SBAR in Nursing?

    SBAR stands for Situation, Background, Assessment, and Recommendation. This structured communication tool was originally developed by the U.S. Navy for nuclear submarine operations but has since become a cornerstone of nursing practice. SBAR in nursing provides a clear framework for healthcare professionals to communicate vital patient information concisely and effectively.

    The SBAR method offers a systematic approach to patient handoff, ensuring that all relevant information is communicated during shift handover or when reporting to physicians. By using the SBAR tool, nurses can organize their thoughts coherently, reducing communication errors that might otherwise compromise patient safety.

    SBAR Nursing Framework

    Essence of SBAR Nursing Communication

    In any healthcare setting, from general medical floors to the intensive care unit, clear communication is essential. A systematic review of communication failures in healthcare revealed that poor handoff communication contributes significantly to adverse patient events. The implementation of the SBAR communication technique has been shown to reduce these incidents substantially.

    Nursing students are now taught the SBAR method early in nursing school, emphasizing its importance in developing professional communication skills. Using the SBAR tool consistently throughout a nursing career helps establish good habits that improve patient care and professional relationships.

    How to Use the SBAR Method Effectively

    SBAR ComponentPurposeKey ElementsExample
    SituationIdentify yourself and briefly describe the current issueYour name and role Patient name/location Concise problem statement“This is Nurse Garcia from Med-Surg. I’m calling about Mrs. Smith in room 423, who’s experiencing acute chest pain.”
    BackgroundProvide relevant contextual informationBrief admission History  Diagnosis Recent relevant events“She was admitted yesterday with pneumonia. History of MI 2 years ago. Pain started 20 minutes ago.”
    AssessmentShare your professional evaluationVital signs Clinical observations Recent changes  Your concerns“BP elevated at 162/94, pulse 112. Pain is 8/10, radiating to left arm. ECG shows ST elevation.”
    RecommendationClearly state what you needSpecific request  Timeframe  Questions“I recommend you come assess her now. Should I call the rapid response team and prepare aspirin?”

    Situation

    The first component of SBAR nursing communication involves clearly stating the current situation. When you use SBAR to communicate with other healthcare providers, begin by identifying yourself, your unit, and your patient. Then briefly describe what is happening that prompted your communication.

    For example: “This is Sarah, RN from the medical care unit. I’m calling about Mr. Johnson in room 215, who is experiencing sudden shortness of breath and dropping oxygen levels.”

    Background

    Next, provide concise background information about the patient that relates to the current situation. This helps establish context for the healthcare team.

    An SBAR report might continue: “Mr. Johnson is a 67-year-old patient admitted yesterday with pneumonia. He has a history of COPD and was stable on 2L oxygen until about 30 minutes ago.”

    Assessment

    In this section of the SBAR nursing framework, share your professional assessment of the situation. This is where your clinical communication skills and nursing practice expertise become evident.

    “His oxygen saturation has dropped from 95% to 88% despite increasing oxygen to 4L. He’s using accessory muscles to breathe, has a respiratory rate of 28, and is becoming anxious. I suspect his pneumonia may be worsening or he could be developing a pneumothorax.”

    Recommendation

    Finally, state your recommendation or what you need from the other healthcare professional. Being clear about what you’re requesting helps avoid communication errors.

    “I recommend coming to assess him now and possibly ordering a stat chest X-ray. Also, should I prepare for possible intubation equipment?”

    SBAR in Nursing Example

    Situation
    The CDC provides that 12 million Americans have COPD, but more than 12 million others have lung function impairment and may be undiagnosed (CDC, 2020). COPD is the third leading cause of death in the US and affects almost 26 million people. Tobacco use contributes to about 75% of COPD cases. Preventing COPD in the US requires implementing healthcare policies that address risk factors such as smoking.

    The Family Smoking Prevention and Tobacco Control Act (Tobacco Control Act) was signed into law on June 22, 2009, to protect the American people and create a healthier future. The policy or law gives the FDA authority to regulate tobacco products’ manufacture, distribution, and marketing. The policy led to a $0.62 increase in tobacco products taxation. However, no increase in taxes has occurred since then. If this policy is not enacted adequately, tobacco will continue to contribute to the majority of COPD cases (75%) and associated deaths (40.5 deaths per 100,000 among US men and 34.3 per 100,000 among US women) (CDC, 2020). COPD will continue to be the third contributor to deaths in the US. 

    Background

    Individuals and organizations, including The American Cancer Society Cancer Action Network, BeTobaccoFree.gov, UCSF Center for Tobacco Control Research and Education, National Networks for Tobacco Control and Prevention, American Lung Association, World Lung Foundation, The Legacy Foundation, Americans For Nonsmoker’s Rights have a special interest in the issue. Their primary interest is to reduce tobacco use and minimize the risks of tobacco-related illnesses like COPD and associated death and promote healthier lifestyles. The policymaker is interested in promoting healthier America, and also in protecting tobacco manufacturers, distributors, and retailers, who are also a part of the economy. However, the burden of COPD is more significant, with a cost of about $49 billion annually. Therefore, policymakers should consider the policy and how it can help reduce tobacco use. 

    As nurses, we are equipped with a responsibility to promote healthier lifestyles. We are also responsible for advocating for health issues like COPD and tobacco use and the patients. Nurses have the necessary skills and knowledge to help patients quit smoking by educating them. Nurses deal with COPD patients every day, and they understand their struggle, including the lack of a cure. Preventative measures become necessary; a reason nurses are advocating for policies to reduce tobacco use. I have had family members and friends who developed COPD, and some have died from its effects in the long run. It is sad to see people die from a disease that can be prevented or minimized in the first place.  

    Assessment

    COPD contributes significantly to mortality rates in the US. Over 6% of the population has been diagnosed with COPD, and nearly the same percentage has lung function impairment and may not be diagnosed (CDC, 2020). This information indicates that the COPD disease burden is greater than reported. As a nurse, I have encountered many patients suffering from COPD, and many have died from its effects. Having a disease as the third contributor to deaths in the country is saddening and shows that relevant stakeholders are not doing enough to enable preventative care. 

    Many stakeholders are involved in efforts to reduce tobacco use consumption to promote healthier communities and reduce the disease burden. Adequate utilization of the policy to minimize tobacco consumption would help stakeholders like National Networks for Tobacco Control and Prevention, American Lung Association, World Lung Foundation, and policymakers achieve positive results in their efforts. The 2009 law has helped prevent over 350,000 teens from smoking and saved about $31 billion in tobacco use-related costs (Truth Initiative, 2019). This information shows that the policy can be more effective if utilized adequately. 

    The policy is supported by the American Cancer Society Cancer Action Network, BeTobaccoFree.gov, UCSF Center for Tobacco Control Research and Education, National Networks for Tobacco Control and Prevention, American Lung Association, World Lung Foundation, The Legacy Foundation, Americans for Nonsmoker’s Rights.

    Recommendation/Request

    The involved organizations and policymakers need to consider implementing an annual tobacco product tax increase at a consistent rate to discourage tobacco use further. The $0.62 tax increase in 2009 had a significant impact. However, people need to feel the impact of tax increases each year to quit or reduce tobacco products consumption. We hope as the healthcare community that the involved stakeholders will consider this proposal with the attention it deserves to save American lives. Thank you for the time and attention you have invested in this matter. As a nurse, I will continue to offer my assistance and expertise based on my knowledge and understanding of the situation to ensure the policy helps promote healthier communities and save lives.  

    References

    American Lung Association (2021). 2021 federal action plan: tobacco priorities. https://www.lung.org/policy-advocacy/federal-action-plan/tobacco-priorities

    CDC. (2020). Public health strategic framework for COPD prevention. https://www.cdc.gov/copd/pdfs/framework_for_copd_prevention.pdf

    CDC. (2018, February 21). COPD costs. https://www.cdc.gov/copd/infographics/copd-costs.html

    Truth Initiative. (2019, June). A decade of the tobacco control act: Where are we now? https://truthinitiative.org/research-resources/tobacco-prevention-efforts/decade-tobacco-control-act-where-are-we-now

    SBAR Nursing Template (PDF and Printable)

    Hospitals and nursing schools often use SBAR report templates to standardize communication. Below is a general format:

    SBAR Report Template

    SectionDetails to Include
    SituationPatient’s name, current condition, immediate concern
    BackgroundMedical history, past treatments, recent changes
    AssessmentCurrent vitals, symptoms, nurse’s evaluation
    RecommendationSuggested actions, medication adjustments, follow-up plans

    Downloadable SBAR Report Sheet (PDF) Many organizations provide nursing SBAR templates in PDF format for documentation. These templates ensure consistency in reporting.

    Benefits of SBAR in Nursing Practice

    Research demonstrates that SBAR improves numerous aspects of healthcare delivery. A quasi-experimental study showed that the implementation of the SBAR communication tool led to:

    • Improved patient safety
    • Enhanced quality of care
    • Better communication between nurses and physicians
    • Reduced communication failures
    • More efficient handoff report processes
    • Greater confidence among nursing staff when communicating in clinical settings

    The Institute for Healthcare Improvement recognizes SBAR as an essential communication strategy that promotes interprofessional communication and ultimately improves patient outcomes.

    SBAR Nursing Applications Across Healthcare Settings

    SBAR Nursing Applications

    The SBAR framework is versatile and can be adapted for various clinical settings:

    Shift Handover

    Using the SBAR tool for shift handover ensures continuity of care. When one RN transfers care to another, the handoff communication follows a consistent structure, reducing the risk of overlooking important patient information.

    Nurse-to-Physician Communication

    When a nurse needs to report to a physician about a change in patient status, SBAR nursing communication provides a professional and efficient format. This structured communication tool helps nurses organize their thoughts and deliver concise, relevant information that physicians need for decision-making.

    Emergency Situations

    In the intensive care unit or emergency department, SBAR helps streamline communication during critical situations. When every second counts, this standardized communication approach ensures that all healthcare professionals receive the necessary information quickly.

    Nursing Education

    Nursing students learn the SBAR method as part of their professional communication training. By incorporating this tool early in nursing school, students develop strong communication skills that serve them throughout their nursing profession.

    Implementing SBAR in Your Nursing Practice

    To effectively incorporate the SBAR communication technique into your daily routine:

    1. Practice using the SBAR template regularly
    2. Keep SBAR tool reference cards handy until it becomes second nature
    3. Encourage fellow nursing staff to adopt this structured communication approach
    4. Participate in department of nursing initiatives to standardize SBAR use
    5. Provide feedback on how SBAR helps improve your clinical communication

    Frequently Asked Questions

    What is an example of a SBAR situation?

    A SBAR situation example in nursing typically involves a scenario where a nurse needs to communicate critical patient information concisely to a physician, another nurse, or a healthcare team member. Here is a practical SBAR example in a clinical setting:

    Scenario: A post-operative patient is experiencing a sudden drop in blood pressure.

    Situation:
    “Dr. Carter, this is Nurse Emily from the surgical unit. I am calling about Mr. James, a 65-year-old patient who underwent a total knee replacement yesterday. His blood pressure has suddenly dropped to 88/55 mmHg.”

    Background:
    “He was stable earlier with a BP of 120/80 mmHg, HR 78, and SpO2 98% on room air. He has a history of hypertension and Type 2 diabetes. He received IV fluids and pain medications during the shift, but no significant changes were noted until now.”

    Assessment:
    “Currently, he appears pale and slightly diaphoretic. His BP remains low despite elevating his legs, and his heart rate has increased to 105 bpm. Urine output is also reduced in the last two hours.”

    Recommendation:
    “I recommend assessing him for possible hypovolemia or bleeding. Should I increase his IV fluids, order a stat hemoglobin check, or prepare for further intervention?”

    This structured approach ensures clear, efficient, and timely communication between healthcare providers, leading to quicker decision-making and better patient outcomes.

    How is SBAR different from traditional nursing reports?

    Traditional nursing reports often vary in structure and content depending on the nurse giving the report. SBAR nursing communication, however, provides a consistent framework that ensures all critical information is included every time. This standardized communication tool focuses specifically on relevant information needed for clinical decision-making, eliminating extraneous details that can distract from the key issues.

    When should nurses use the SBAR method?

    Nurses should use SBAR to communicate in various situations, including:

    • Shift handover reports
    • Calling physicians about changes in patient status
    • Transferring patients between units
    • Communicating with other healthcare professionals during emergencies
    • Documenting significant changes in patient condition
    • Training nursing students in professional communication

    The SBAR tool is particularly valuable during high-stress situations when clear communication is essential.

    How can nursing students practice using SBAR?

    Nursing school programs typically incorporate SBAR training through:

    • Role-playing scenarios with peers
    • Simulation labs with standardized patients
    • Clinical rotations with preceptor feedback
    • SBAR template worksheets to complete during clinical experiences
    • Video recording practice sessions for self-evaluation

    Regular practice using the SBAR tool helps nursing students develop the communication skills necessary for their future nursing practice.

    Does SBAR in nursing replace other forms of documentation?

    No, SBAR doesn’t replace comprehensive nursing documentation. Instead, it complements existing documentation by providing a structured communication technique for verbal exchanges. Many healthcare settings incorporate SBAR format into their electronic health records for consistency between verbal and written communication.

    How has SBAR improved nursing practice?

    According to multiple systematic reviews, implementation of the SBAR communication tool has led to:

    • 65% reduction in adverse events related to communication failures
    • Improved satisfaction among nurses and physicians
    • Enhanced confidence among nursing staff when communicating with physicians
    • More efficient handoff processes, saving an average of 7 minutes per shift change
    • Better identification of deteriorating patients through consistent assessment reporting

    These improvements demonstrate why SBAR nursing communication has become standard practice in healthcare settings worldwide.

  • Med Surg Exam 1 blueprint nurs 3661

    N 3661 Exam 1 Exam Blueprint – Med Surg Exam 1 blueprint nurs 3661

    Med Surg Exam 1 blueprint nurs 3661

    The focus of the N3561 exams is nursing management (Med Surg Exam 1 blueprint nurs 3661. This will mean you need to recognize risk factors (what can they nurse teach about here), expected findings, signs of complications, how is this condition/disease managed (medications , diet , exercise , etc…). So, when you look at the content areas – think assessment, planning, intervention and evaluation.

    Perioperative Nursing 

    1. Explain the nurse’s responsibilities preoperatively and during surgery.

    Pre-op responsibilities

    • Assessment (includes vitals)
      • Ensure that ordered diagnostic procedures are done and provider is notified of abnormal results (labs, X-rays, EKG’s).Witness informed consent.Patient in gownAllergy/ID bands placed on pt.Perform any required bowel prep.  Perform any required skin prep.  Start IV (at least an 18 gauge)  Give ordered pre-op meds.Ensure patient has been NPO.Remove all jewelry, dentures, prosthetics, make-up, nail polish, glasses, contacts.Pt teaching about what to expect after surgery.Ask about blood thinners (aspirin, Plavix, lovenox, etc.)Patient uses restroom prior to ORDocumentationIntra-op responsibilitiesRoom prep (privacy, infection prevention, safety)Transfer pt to OR suite (verify pt identity, transfer pt safely)Surgical time-out (before anesthesia given)  Pt confirms name & DOB.Operative procedure and procedure sitePatient consent (verbal)Compare hospital ID # with pt armband and chart.Maintain sterile field.Sponge/instrument count.  Position pt for optimal alignment  Prevent chemical injury.Electrical equipment safety.Give meds safely.Monitor vitals.
      • Monitor blood loss and urine output.
    • Identify the purpose and components of preoperative nursing assessment and interpret the significance of data related to the patient’s health status and risk.
    • Vital signs (establishes baseline and is safety precaution)
    • Home medications (prescription, OTC, herbal supplements) Especially blood thinners (including aspirin) and beta blockers – reduced nonfatal MIs in highrisk patients undergoing elective surgery. Therefore, pts. Who are already on beta blockers should continue to take them during the perioperative period.
    • Allergies to drugs, foods, or latex (allergy to kiwi, avocado, bananas, [[or balloons may indicate latex allergy)
    • Previous surgical history/reactions to anesthesia
    • Labs/X-ray/EKG
    • Urinalysis- kidney fx, rule out infection.
    • Blood type and crossmatch- if pt needs transfusion.
    • CBC- hydration, anemia, infection/immune status
    • Pregnancy test- fetal risk
    • Clotting studies- PT, INR, aPTT, platelet count
    • Electrolyte levels (usually a BMP or CMP)- electrolyte imbalances
    • Serum creatinine and BUN- kidney fx
    • ABG’s (per ATI book) oxygenation status
    • Chest x-ray- heart and lung status
    • EKG- baseline, check for dysrhythmias, hx of cardiac disease, done on all pt’s  over 40 (per ATI)
    • Nutritional status
    • obesity, weight loss, malnutrition, deficiencies in specific nutrients,
    • metabolic abnormalities (nutrition affects healing. Table 17-2 on pg 425 talks about specific nutrients)
    • Hydration status -dehydration, hypovolemia and electrolyte imbalances can cause significant problems in surgery.
    • Dental- do they have dentures or anything removable in their mouth? Any anatomical issues that might make it hard for intubation. Decaying teeth may crumble and go into airway during intubation
    • Drug/alcohol use – weakens immune system, can interfere with medications, increases post-op complications, alcoholics tend to be malnourished.
    • Respiratory status – infections, resp diseases (asthma, COPD), smoking causes poor wound healing, more surgical site infections, complications the include blood clots and pneumonia.
    • Cardiovascular status- ensure pt can tolerate the O2, fluid and nutritional requirements of surgery. Uncontrolled HTN may cause delays in surgery.
    • Liver fx– liver metabolizes the medications, if liver sucks, meds can build up and be toxic.
    • Kidney fx– kidneys excrete meds, most surgeries are contraindicated on patients with renal problems unless the surgery is absolutely necessary.
    • Endocrine fxo
    • Diabetes- hypoglycemia can develop from inadequate carbs or too much insulin,
    • hyperglycemia can develop from stress of surgery and can increase risk of wound infection.
    • Patients who have been on corticosteroids any time in the last year may be at
    • risk of adrenal insufficiency.        Must be reported to CNRA or anesthesiologist.
    • Pt’s with uncontrolled thyroid disorders are at risk of thyrotoxicosis (with hyperthyroid disorders) or respiratory failure (with hypothyroid disorders)
    • Immune fx– determines infection and allergies. Immunosuppression can occur with corticosteroid therapy, organ transplant, radiation, chemo, immune system disorders like AIDs and leukemia.
    • Psychosocial factors
    • Preoperative anxiety (determine what it’s related to and provide supportive guidance)
    • Pt’s support system (how much help do they have or need at home?)
    • Pt’s baseline level of functioning and typical daily activities (assist in pt’s care and recovery)
    • Pt’s readiness to learn and how they learn (to provide the most affective education)
    • Spiritual & cultural beliefs
    • We must help the pt obtain the spiritual support they request (within reason of course, no live chickens or goats or anything)
    • Ask pt if their spiritual advisor is aware of impending surgery (be careful how you say it because it may make pt’s think that you think they are going to die or something)
    • Ask pt which ethnic group they belong to and any customs/beliefs the pt holds about illness and health care providers.
    • Joint problems – can impact patient positioning in surgery, don’t want to bend something in a way that it doesn’t bend anymore.
    • Special considerations
    • Elderly– can have more comorbidities. They have less physiological reserve (ability of an organ to return to normal after a disturbance in its equilibrium). Respiratory and cardiac complications are leading causes of post-op morbidity and mortality in older adults.
    • Bariatrico BMI > 30. Obesity increases the risk and severity of complications from surgery.
      • Increase in wound infections and dehiscence. Possible restrictions on theability to move.
      • Increased cardiac demand.
      • Shallow respirations when supine increased risk of hypoventilation and postop pulmonary problems.
      • Can have short, thick necks, big tongues, recessed chins, etc that can make them harder to intubate, increase O2 demand and decrease pulmonary reserves.
      • Assess for sleep apnea, very common in overweight folks.
      • Pt’s with disabilities– assess for need for assistive devices, modifications in
    • preop education, additional assistance with positioning and transferring.
    • Explain the etiology and nursing assessment with management of post-operative care.
      • Objectives are to provide care until pt has recovered from effects of anesthesia (resumes motor and sensory fx), making sure that the pt is oriented, has stable vital signs, and shows no evidence of hemorrhage or other complications.
      • Assess – airway, respiratory fx, cardiac fx, skin color, level of consciousness, ability to respond to commands, vital signs (minimum Q15, more frequent if needed), surgical sites, drainage tubes and monitoring lines, IV fluids and meds.
      • Airway
      • Primary objective- right after surgery, is maintaining ventilation and preventing hypoxemia and hypercapnia.
      • Give O2 as prescribed, assess resp rate & depth, ease of respiration, O2 sats, breath sounds.
      • Monitor for hypopharyngeal obstruction from lower jaw and tongue blocking airway.o S/S: choking, noisy & irregular respirations, decreased O2 sats, cyanosis (blue, dusky skin color).

    o Can try head tilt and chin lift to improve.

    • Use hand to feel pt’s breath, just b/c pt’s chest is moving doesn’t mean they are breathing HOB elevated 15 to 30 degrees unless contraindicated.
      • If vomiting, turn on the side.
        • Suction if needed.
        • Cardiac
        • Primary post op CV complications are hypotension and shock, hemorrhage, HTN and dysrhythmias.
        • Hypotension– blood loss, hypoventilation, position changes, pooling of blood in extremities, side effects of meds.
        • Shock-
        • Can be classified as hypovolemic, cardiogenic, neurogenic, anaphylactic, and septic.
        • Most common is hypovolemic.

    S/S: pallor; cool, moist skin; rapid breathing; cyanosis of lips, gums, and tongue; rapid, weak, thready pulse; narrowing pulse pressure; low blood pressure; concentrated urine.

    • Relieve pain and anxiety
      • usually opioids b/c they provide immediate relief and are short acting so not as much of a risk of prolonged respiratory depression.
      • Control nausea/vomiting – treat nausea ASAP to decrease chance of vomiting and aspiration.
      • Determine if pt ready to leave PACU (is a critical care unit where the pt’s vital signs are closely observed, pain mgt begins and fluids are given) o Aldrete score (tool to maintain assessment of the post anesthesia pt as they move through their stay in the dept. and in the hospital).assign number of 0, 1,, or 2 to 5. Variables.
      • Used to determine if pt is ready to leave PACU (Post Anesthesia Care Unit) o Q15 minutes, pt given score for activity (movement), respiration, circulation (blood pressure), consciousness, and O2 sats. Scores are added and usually if pt scores are below 7, they must stay in PACU. Usually, a score of 7-10 means pt can leave PACU. o ATI list of what nurses should monitor and assess.
      • Airway, circulation. Vital signs, positioning, response to anesthesia (sedation, nausea, vomiting), I/O’s, surgical wound/incision site/drainage, pain, mentation (mental activity).
    • Choose strategies to prevent postoperative complications.  Airway obstruction
      • Monitor for S/S of hypopharyngeal obstruction discussed above and intervene.
      • Head-tilt/chin-lift.
      • Keep resuscitation bag, suction equipment and airway supplies at bedside.
      • Notify anesthesiologist,
      • Elevate HOB if not contraindicated.
      • Give humidified O2,
      • Prepare for reintubation with ET tube.
      • Hypoxia
      • Monitor O2 status and give O2 as prescribed.
      • Encourage coughing and deep breathing to prevent atelectasis.
      • Elevate HOB and turn Q2 hours to facilitate chest expansion.
      • Hypovolemic shock
      • Monitor for decreased BP and urinary output, increased heart and respiratory rates, narrowing of pulse pressure and slow cap refill.
      • Give O2.
      • Supine position with legs elevated.
      • IV fluids and vasopressors as prescribed.
      • Paralytic ileus
      • Monitor bowel sounds.  Encourage ambulation.
      • Advance diet as tolerated when bowel sounds or flatus are present.
      • NG tube placement if needed to empty stomach.
      • Give prokinetic agents, such as metoclopramide, as prescribed.
      • Wound dehiscence or evisceration.
      • Monitor risk factors (obesity, coughing, moving without splinting, poornutritional status, diabetes, infection, hematoma, steroid use).
      • If it occurs, call for help, stay with pt, cover wound with sterile towel ordressing that is moistened with sterile saline, do not attempt to reinsert organs, place in low-Fowlers with hips and knees bent, monitor for shock, notify provider STAT.
      • DVT-
      • Prophylactic treatments:
        • low molecular weight heparin.
          • low-dose heparin, low dose warfarin.
          • anti-embolism stockings.
          • pneumatic compression devices.
          • range of motion (ROM) exercises.
          • early ambulation
      • Avoid any pressure behind the knee with a pillow or blanket, can constrict bloodvessels and decrease venous return.
      • Don’t let pt’s legs dangle very long.
      • Hydration with IV fluids and PO intake
      • Other complications listed on last page of powerpoint
      • Pulmonary embolism
      • Urinary retention
      • Infection
      • Gastric dilation
      • Pneumonia
      • Atelectasis
    • Describe general discharge teaching for the postop patient.

    Teach the patient-

    • The purpose, administration, guidelines, and adverse effects of meds
      • Activity restrictions (driving, stairs, limits on weightlifting, sexual activity)  Dietary guidelines
      • Treatment instructions (wound care, catheter, care, use of assistive devices)  Emergency contact info and what complications they should report.

    Content

    Perioperative Care

    A. Preoperative Nursing

    1. Consent
      1. Medications to avoid
        1. Teaching

    B. Postoperative Nursing

    1. Prevent complications ( IS, CD&B, ambulation , SCD’s etc..)
      1. Assessment

    C. Discharge Teaching

    1. potential limitations
      1. teaching that should occur ( what does the nurse need to cover)

    Fluid & Electrolytes

      Identify patients at risk for F&E imbalance. Infant age 1 and under and older adults.

      Describe the etiology, laboratory, diagnostic findings and nursing as well as collaborative management of persons with fluid and electrolyte imbalances.

    II.  Fluid & Electrolyte Imbalances

    A. Electrolyte imbalances

                      a.   Sodium

    • Normal range 135-145
    • Hyponatremia – < 135  Signs/symptoms:
    • Anorexia, nausea and vomiting, headache, lethargy, dizziness, muscle cramps and weakness, muscle

    twitching, seizures, increased pulse, decreased BP,

    • Labs:
    • Decreased serum and urine sodium, decreased urine specific gravity and osmolality.
    • Management.
    • Sodium replacement and water restriction  management:
    • Monitor and Ident. pts at risk.
    • Nursing management
    • Monitor I&O and daily weight.
    • Hypernatremia
    • 1. >145
    • Signs and symptoms
    • Thirst, elevated body temp, swollen dry tongue and sticky mucus membranes, hallucinations, lethargy,
    • restlessness, irritability, simple partial or tonic clonic.  seizures, pulmonary edema, hyperreflexia, twitching,  nausea, vomiting, anorexia, increase pulse and BP.
    • Labs
    • Increased serum sodium, decreased urine sodium,
    • increased urine specific gravity and osmolality
    • Nursing management
    • Gradual lowering of serum sodium with IV hypotonic solution or isotonic non saline solution
    • I&O monitoring.
    • Calcium
      • Normal range 8.5-10.5  Hypocalcemia – <8.5
      • Signs and symptoms
        • Numbness, tingling of fingers, toes, and circumoral region.
          • Positive Trousseau sign and Chvostek sign.
            • seizures, carpopedal spasms, hyperactive deep tendon reflexes, irritability, bronchospasm, anxiety, impaired clotting time,
            • ↓ prothrombin, diarrhea,
            • ↓BP. ECG: prolonged QT interval and lengthened ST
          • Management
          • Acute symptomatic
          • IV infusion of calcium salts.
          • Nutritional therapy
          • Vitamin D
          • Nurse management
            • Monitor pt if severe seizure precautions areimplemented.
            • Airway monitored for laryngeal stridor.
            • Diet education
      • Hypercalcemia   >10.5
      • Signs and symptoms

     Muscular weakness, constipation, anorexia, nausea and vomiting, polyuria and polydipsia, dehydration, hypoactive deep tendon reflexes, lethargy, deep bone pain, pathologic fractures, flank pain, calcium stones, hypertension. ECG: shortened ST segment and QT interval, bradycardia, heart blocks

    • Management
      • Aim to decrease calcium level.
        • Treating the underlying cause is essential.
          • Nurse management
            • Increase mobility and encourage fluid intake.
            • Unless contraindicated fluids with sodium should be encouraged.
            • Encourage adequate fiber intake.
            • Monitor cardiac rhythms.
    • potassium
      • Normal 3.5-5
        • Hypokalemia <3.5
          • Signs and symptoms
          • Fatigue, anorexia, nausea and vomiting, muscle weakness, polyuria, decreased bowel motility, ventricular asystole or fibrillation, paresthesia’s, leg cramps,
          • ↓ BP, ileus, abdominal distention, hypoactive reflexes.
          • ECG: flattened T waves, prominent U waves, ST depression, prolonged PR interval
          • Management
          • Oral or IV potassium replacement  Nurse Management
          • Monitor ECG and for dig toxicity.
          • Hyperkalemia – >5
          • Signs and symptoms
          • Muscle weakness, tachycardia → bradycardia, dysrhythmias, flaccid paralysis, paresthesia, intestinal colic, cramps, abdominal distention, irritability, anxiety.
          • ECG: tall, tented T waves, prolonged PR interval and QRS duration, absent P waves, ST depression
          • Management
          • ECG immediately obtained.
          • Kayexalate (poo the potassium away)
          • Emergency management
    • IV calcium gluconate
    • IV regular insulin and a hypertonic dextrose solution
      • Nurse management
        • Monitor pt and I&O
    • Magnesium
      • Normal 1.3-2.3
        • Hypomagnesemia – <1.3
        • Signs and symptoms
          • Neuromuscular irritability, positive Trousseau sign and Chvostek sign, insomnia, mood changes, anorexia, vomiting, increased tendon reflexes, and ↑BP.
            • ECG: PVCs, flat or inverted T waves, depressed ST segment, prolonged PR interval, and widened QRS.
          • Management
          • Mild-diet therapy
          • Magnesium salts can be given orally or IV.
          • Nurse management.  Monitor pt.
          • Education
          • Hypermagnesemia >2.3
          • Signs and symptoms
          • Flushing, hypotension, muscle weakness, drowsiness, hypoactivereflexes, depressed respirations, cardiac arrest and coma, diaphoresis.
          • ECG: tachycardia →bradycardia, prolonged PR interval and QRS, peaked T waves
          • Management
          • Avoid magnesium salts on pts with kidney injury.
          • In emergent situations IV calcium gluconate is indicated.

    B.NO ABG’S (arterial blood gases)

    • Fluid Volume Deficit; causes, symptoms and management. Remember BP changes
      • know orthostatic BP – how do you do it ? What’s normal ?
      • Fluid Volume Excess; causes, symptoms and management.
      • Some specific electrolyte disturbances- examples (not an all-inclusive list electrolytelosses secondary GI issue (like an NGT) NO ABG’S (arterial blood gases)

     Heart Failure:

    Heart Failure

    1. Causes ( risk factors)
    • Clinical Manifestations
      • Left-sided HF
        • Signs/symptoms
          • Dyspnea, orthopnea, nocturnal dyspnea  Fatigue
            • Displaces apical pulse.
            • S3 heart sound (gallop)
            • Pulmonary congestion
            • Frothy sputum
            • AMS
            • Manifestations of organ failure such as oliguria
            • nocturia
            • Nursing management
      • Right-sided HF
        • Signs/symptoms
          • JVD
          • Ascending dependent edema
          • Fatigue, weakness
          • Nausea and anorexia
          • Polyuria at rest (nocturnal)
          • Liver enlargement and tenderness
          • N 3561 Exam 1 Exam Blueprint
          • Weight gain
          • Nursing management Medical Management
          • labs to monitor.
          • BNP
          • lytes
          • Pharmacologic Therapy
          • Diuretics. (Labs to monitor, how do you know the medication was effective)
          • Digoxin. (Sign of toxicity, what does the nurse need to monitor)
          • HF Plan of Care
          • weight management /monitoring  signs of exacerbation
          • LOOK FOR ABOVE.

    Hypertension:

    Identify risk factors associated with primary hypertension.

    • Nonmodifiable risks
      • Age: over 60 or postmenopausal
        • Race: especially African Americans
          • Family history
          • Gender
          • Prehypertension or gestational diabetes
          • Modifiable risks
          • Overweight or obese
          • High sodium intake
          • Alcohol use
          • Lack of physical activity
          • Smoking
          • Stress
          • Hyperlipidemia

     Explain the medical and nursing management of the person with hypertension.

    • Lifestyle modifications
      • Weight loss (shoot for BMI of 18.5-24.9)
        • DASH diet (Dietary Approaches to Stop Hypertension)
          • Rich in fruits & vegetables
            • Low-fat dairy
            • Reduce saturated and total fat.
            • Reduce sodium intake to at least < 2400 mg a day, but preferably <1500 mg a day.
          • Aerobic activity at least 30 minutes a day, most days of the week
          • Reduce alcohol- limit consumption to 2 drinks or less (24 oz beer, 10 oz of wine,
          • or 3 oz 80-proof whiskey) per day in most men and 1 drink of less per day in
          • women or lighter weight people.
          • Medication therapy (they will start on lowest dose, then increase gradually if needed.
          • Multiple medications may be needed to reach the target).
          • The medications used for treating hypertension decrease peripheral resistance,  blood volume, or the strength and rate of myocardial contraction. Initial medication for African American patients and patients over 60 with stage I hypertension is a calcium channel blocker or a thiazide diuretic. Patients with stage I who are not African American and less than 60 are started with an ACE inhibitor or ARB. Patients are initially given low doses of medication. If the blood pressure does not fall less than 140/90 mm Hg, the dose is increased gradually, and additional hypertension medications may be included. When the bp is less than 140/90 for a least 1-year, gradual reduction of the types and doses is considered.
          • Diuretics
          • Thiazide diuretics (hydrochlorothiazide)
          • Usually, the first drug they put people on if they don’t have any other. major issues
    • Prevents reabsorption of sodium and water Excretes more potassium.
    • Monitor for hypokalemia.
    • Pt may need to eat more potassium.
      • Loop diuretics (furosemide AKA Lasix)  Same info as thiazides.
        • Potassium-sparing diuretics (spironolactone)  Prevent reabsorption of sodium  Hold onto potassium.
        • Monitor for hyperkalemia.
        • ACE Inhibitors (lisinopril and enalapril)
        • Prevent angiotensin I from converting to angiotensin II whichprevents vasoconstriction.
        • Monitor for hypotension, heart or kidney complications, edema.
        • Teach pt to report cough and any signs of heart failure (edema)
        • Can cause angioedema, HUGE swollen lips
        • Beta blockers (metoprolol and atenolol)
        • Decrease cardiac output and block release of renin, leads todecreased.

    vasoconstriction

    • Good for unstable angina or MI
      • Check bp and PULSE before giving.

     Identify the impact of uncontrolled hypertension on other body systems. (renal, cardiac, eyes, etc.…)

    • Uncontrolled hypertension can result in a hypertensive crisis.  Manifestations include-
      • severe headache, extremely high blood pressure greater than 240/120,  blurred vision, dizziness, disorientation, and epistaxis.
        • Prolonged blood pressure elevation gradually damages blood vessels throughout the body, target organs such as the heart, kidneys, brain, and eyes.
        • The typical outcome of Uncontrolled hypertension is MI, heart failure, chronic kidney disease, stroke, and impaired vision.
        • Hypertrophy of the left ventricle of the heart may occur as it works to pump blood against the elevated pressure.

     Identify which evaluation(s) would indicate a therapeutic response to the medical and nursing interventions.

    • Reports knowledge of disease management sufficient to maintain adequate tissue perfusion such as
      • The patient maintains a blood pressure less than 140/90 mm Hg with lifestyle modifications and medications.
        • Demonstrations no symptoms of angina, palpitation, or vision changes. Has stable BUN and serum creatinine levels.
        • Has palpable peripheral pulses.
        • Adheres to the self-care program such as abstains from tobacco and alcohol intake, adheres to dietary regimen, exercise regularly, takes medication.
        • Keeps follow up appointments, and measure bp routinely.
        • Has no complications such as  no changes in vision.
        • exhibits no retinal damage on vision testing.
        • reports no dyspnea or edema.
        • maintain pulse rate and rhythms and respiratory rate with normal ranges.
        • maintain urine output consistent with intake.
        • has renal function test results within normal range.
        • demonstrates no motor, speech, or sensory deficits.
        • and reports no headaches, dizziness, weakness, change in gait, or falls.

     Identify and discuss what is/are the priority teaching(s) to patients with hypertension.

    • Express the importance of adhering to the medication regimen.
      • Encourage the patient to keep all appointments with the provider to monitor efficacy of pharmacological treatment and possible electrolyte imbalance.
        • Encourage potassium-rich foods if the patient is taking a potassium-depleting diuretic.
        • Instruct patients who are taking antihypertensives to change positions slowly, and  to be careful when getting out of bed, driving, and climbing stairs.
        • Patients should rise slowly to prevent postural hypotension.
        • Patients should not stop their medications abruptly. Smoking cessation and stress reduction.
        • Patients should be taught how to monitor BP at home.

    Effect on organs macrovascular vs microvascular (this is complications)

    • Potential complications include left ventricular hypertrophy, MI, heart failure, TIAs, cerebrovascular disease (stroke or brain attack), renal insufficiency and chronic kidney disease, and retinal hemorrhage.

    Patient teaching- Diet- what kind? What does the nurse need to teach about?

    Dash Diet:

    • consume a diet rich in fruits, vegetables, low-fat dairy products with a reduced content of saturated fat.
      • monitor for hyperkalemia with salt substitute use.
        • Consume less than 2.3g/day of sodium.
        • Avoid foods high in sodium and fat (trans and saturated fat)  Consume feeds rich in calcium and magnesium.

    Medications: Table 31-4

    • Diuretics: Thiazide diuretics inhibit water and sodium reabsorption and increase potassium excretion.
      • Other diuretics can treat hypertension that is not responsive to thiazide diuretics such as loop diuretics and potassium diuretics.
        • Monitor potassium levels and watch for muscle weakness, irregular pulse, and dehydration.
        • Thiazide and loop can cause hypokalemia, and potassium-sparing diuretics can cause hyperkalemia.
        • Ace inhibitors: (end in -pril) prevents the conversion of angiotensin I to angiotensin II, which prevents vasoconstriction.
        • Hypotension is a common adverse effect.
        • Monitor for evidence of heart failure, edema.
        • ACE inhibitors can cause heart and kidney complications.
        • Teach the client to report a cough as it’s an adverse effect.
        • Beta blockers: (end in -olol) for clients with unstable angina and MI.
        • They decrease cardiac output and block the release of renin, decreasing vasoconstriction of the peripheral vasculature.
        • These meds can mask hypoglycemia in clients with DM.

    What does the medications do for the patient? How does the nurse know the medications are working? Side effects? What needs to be monitored?

    • The patients bp should be lower than 140/90.
      • When the patient returns for follow up care, all body systems must be assessed to detect any evidence of vascular damage.
        • An eye examination with an ophthalmoscope is important to detect retinal blood vessel damaged which indication similar damage elsewhere in the  vascular system.
        • The patient is questioned about blurred vision, spots in the front of eyes and diminished visual acuity.
        • The heart, nervous system, and kidneys are assessed.
        • The patient should report no changes in vision, edema, dyspnea,  no motor, sensory, or speech deficits.
        • Urine output should be consistent with input, no headaches, weakness, or falls. Any significant findings may indicate the need to change medications and additional diagnostic tests may be needed such as urinalysis, blood chemistry, a 12-lead electrocardiogram, and echocardiography.
        • Additional studies, such as creatinine clearance, renin level, urine tests, and 24-hour urine protein.

    Diabetes:

    1.   Describe the clinical manifestations of persons with diabetes. General Signs and Symptoms of Diabetes

    Type I vs Type II Diabetes

     Criteria for Diagnosing Diabetes

    *note – PGL plasma glucose level {there is a difference between a PGL and a BLG (blood glucose level).

    The textbook talks about obtaining plasma glucose levels.

    • Ketones – a highly acidic substance formed when the liver breaks down free fatty acids in the absence of insulin
    • Classic Signs of Diabetes – Polyuria, polydipsia, and weight loss

    2.Explain the relationship between diabetes and other disease processes  Macrovascular disease – usually associated with type II diabetes.

    • Pathology – Increased atherosclerosis [1] leading to ischemia
      • Changes in arterial walls r/t hyperglycemia and hyperinsulinemia  Changes in platelet and clotting factors  Decrease in RBC flexibility.
      • Decrease in oxygen release.  Specific Processes
      • Coronary Artery Disease (CAD)
      • MIs are more likely to occur, reoccur, and cause death.
      • MIs may not have ischemic signs and symptoms  silent MI related to neuropathy.
      • Cerebrovascular Disease
      • Thrombus of cerebral vessel or emboli that lodges in cerebral vessel  Recovery is also hampered in diabetics.
      • HHS and DKA symptoms may be similar to those of a stroke.  Peripheral Artery Disease (PAD)
      • S&S  diminished peripheral pulses, claudication, pale skin
      • PAD can progress resulting in ischemia, gangrene and need for
      • amputation
      • Microvascular – usually associated with type I diabetes.
      • Pathology
      • Elevated glucose causes a thickened capillary basement membrane.
      • Specific Processes
      • Diabetic Retinopathy
      • Leading cause of blindness in ages 20-74
      • Microvascular changes of retinal [2] blood vessels cause.

    S&S of Retinopathy

    • Many are asymptomatic until proliferative stage.
      • Floaters/cobwebs
      • Sudden, spotty, hazy vision
      • Sudden complete loss of vision

    Diabetic Nephropathy

    • Microvascular changes to and around kidney filtration mechanism
      • Caused by osmotic pressure placed on kidneys by excreted glucose and protein
      • Damage to kidneys can increase BP.

    Neuropathic – nerve damage caused by chronically elevated BGL.

    Pathology

    • Thickening and closing of capillary membrane around nerves decreases nerve.  perfusion
      • Demyelization of nerves slows/disrupts nerve conduction.

    Specific Processes

    • Peripheral (sensorimotor) polyneuropathy
      • Paresthesia
      • Decreased proprioception.
      • Charcot joints [3].
      • Decreased deep tendon reflex.
      • Autonomic neuropathy  affects every organ of the body.  Cardiovascular Neuropathy  Fixed, tachycardic HR.
      • Orthostatic hypotension
      • Silent MI Gastrointestinal Neuropathy  Delay gastric emptying.
      • Constipation or diarrhea
      • Wide swings in BGL due to inconsistent GI absorption of glucose
      • Renal/Bladder Neuropathy
      • Urinary retention with decreased sensation of fullness
      • UTIs

    Adrenal Medulla Neuropathy

    • Hypoglycemic unawareness
      • Adrenal glands no longer respond to hypoglycemic conditions.

    Sudomotor Neuropathy  anhidrosis (absent sweating) related to diabetic neuropathy.

    • Sexual Dysfunction  Reduced vaginal lubrication.  Decreased libido.
      • Vaginal infections
      • Erectile dysfunction/retrograde ejaculation  Cranial mononeuropathies

    Others

     Hypertension – most common complication in people with diabetes but may not bedirectly caused by diabetes.

    • High cholesterol = HTN
      • Kidney damage = HTN
      • Vascular damage = HTN
      • Erectile dysfunction = HTN related medications

    Metabolic Syndrome  interrelated conditions typical of type II diabetes

    • Atherosclerosis – blood vessel wall thickening, sclerosing, and becoming occluded by plaque.
    • Retina – the part of the eye that receives and sends images.
    • Charcot Joints – neuropathy related joint changes, often found in the foot, caused by abnormal weight distribution.
    • Explain the psychological and sociological effects of diabetes in the individual and family.

    Implementing nutritional changes can affect the entire family.

    • Hypoglycemia/DKA/HHS can be traumatic experiences for the family.
      • Children with diabetes have a significant impact on their family.
      • Administering injections
      • Sudden blindness caused by diabetes can be the first indication of diabetes.
    • Compare and contrast the pharmacological management and nursing implicationsassociated with people with diabetes.
      • General Nursing Considerations  Monitor BGL
      • Beta-blockers may block S&S of hypoglycemia.

    Ultra long acting insulin provides additional glucose control and lasts for more than 24 hrs

    [1] Lactic Acidosis S&S – myalgia, sluggishness, somnolence, hyperventilation

    • Apply the concepts of nutrition to the care of persons with diabetes
      • Nutrition, meal planning, weight control, and increased activity are the foundation of diabetes management.
      • Control total caloric intake to attain or maintain a reasonable body weight,
      • Control of blood glucose levels, and normalization of lipids and blood pressure to prevent heart disease.
      • Registered dietician and RNs responsible for design and educate about aspects of a therapeutic plan.
      • A meal plan for diabetes focuses on the percentages of calories that come from carbohydrates, proteins, and fats. OH=risk for hypoglycemia.
    • Appraise the learning needs and develop teaching plans for the person with diabetes.
      • Nursing management of patients with diabetes can involve treatment of a wide variety of physiologic disorders, depending on the patient’s health status and whether the patient is newly diagnosed or seeking care for an unrelated health problem. Monitor glc levels,  Assess self-care skills.
        • Provide basic education.
        • Reinforce the education provided by the specialist and refer patients for follow-up care.
    • Identify the nursing responsibility in the short and long-term management (including discharge instructions) of the person with diabetes.
      • Teachpt about diet = limit carbs, increase protein, limit fats, medication, exercise @ least 3X/wk, sleep, encourage weight loss, self-management skills, monitor blood glc and prevent complications.
        • Teach pt and family members S&S of hypo and hyperglycemia.
        • Diabetes management has five components:

     nutritional therapy, exercise, monitoring, pharmacologic therapy, and education.

     Need to do constant assessment.

    o Diabetes

    1. Type I and II Diabetes ( know the differences)
    • Clinical Manifestations – hypoglycemia & hyperglycemia

    Note: Additional info below if you want to go over it, if not continue part C. Nutrition Hypoglycemia- < 65, devastating effects on the CNS b/c relies on glc for energy if no glc lead to cell death.

    *How can it happen?

    • Too much insulin circulating, overly high dose of oral hypoglycemic.
    • Reduced clearance of insulin from the body because of renal insufficiency *Who is at risk?
    • Decreased nutritional intake.
    • Increase metabolism d/t exercise.
    • Alcohol can reduce glucose levels too by blunting the release of glucose from the liver.
    • Can be more severe if the early signs are blunted – pt. isn’t aware – one thing you might see is a change in mental status in the elderly.

    *S&S

    Anxiety, palpitations, hunger, paresthesia (numbness at lip), sweating, shakiness.

    *If it continues to drop – where the CNs would be involved

    • Difficulty thinking, dizzy, fatigue, sleepiness, slurred speech, weakness lack of  coordination.

    *If continues to be untreated: seizures coma

    If a patient suffers from hypogly frequently – they may be unaware of early symptoms – this patient should increase their BS control number to avoid hypogly events.

    Hyperglycemia = Diabetic Ketoacidosis (DKA) BG > 250

    *Causes – missed dose of insulin /inadequate insulin d/t increases insulin needs secondary to stress or infection

    New dx of DM 1 *How is it diagnosed?

    • ketones in the urine
    • arterial pH <7.30
    • serum bicarb <15
    • Positive anion gap

    *S&S

    The three P’s.

    • Pt. becomes dehydrated- electrolyte imbalance. Increase or decrease K+  Fluid shift from intracellular to the extracellular.
    • Leads to dilution AL hyponatremia.
    • Patient at risk/f hypovolemia 2’ to the osmotic diuresis.

    *If not treated what happens?

    • Hypotension, tachycardia secondary fluid vol. loss.
    • Kussmaul respiration develop – these are rapid deep respirations this is a  compensatory mechanism for acidosis.
    • fruity acetone breath – because of the ketone bodies s
    • n/v
    • lethargy, coma *Treatment
    • Fluid replacement – NS (isotonic)
    • Insulin administration
    • Correction of electrolyte imbalance.

    C. Nutrition – timing of snacks when giving insulin, general diet teaching

    • If a patient is in Lispro (rapid acting insulin) give it w/food bc it works quickly. Highest risk
    • for hypoglycemia is when it reaches peak level so here is when you need a snack for
    • the patient. Know peak time=snack time
    • N 3561 Exam 1 Exam Blueprint
    • Diabetic diet = limiting carbs or counting carbs. Pt edu @ bedside but need support when they go home they need to consult a dietician to help them with diet at home.  D. Acute and chronic complications: DKA, HHNS, hypoglycemia , effects on organs.
    • *DKA
    • hypotensive tachy secondary vol. loss.
    • kussmauls respirations develop – these are rapid deep respirations this is a

    compensatory mechanism for acidosis. fruity acetone breath – because of the ketone bodies n/v

    • lethargy
    • Coma

    *HHNS-Hyperosmolar Hyperglycemic Non-Ketosis or Hyperglycemic

    • Hyperosmolar State (HHS) is serious event, glucose levels rise toward 600 +
    • Characterized by hyperglycemia hyperosmolarity and dehydration without ketoacidosis (big distinguishing factor)
    • *It occurs when there is sufficient insulin to prevent the breakdown of fat and ketone release BUT not enough insulin to prevent severe hyperglycemia
    • *Because of this the body compensates this leads to extreme hyperosmolarity leads to osmotic diuresis –
    • The patient became severely dehydrated!!!! And suffers from electrolyte.
    • imbalances (severe)
    • They may also present with neuro defects.
    • *It is less common then DKA
    • Does have a higher mortality rate than DKA. Hypoglycemia
    • *If insulin continues to drop – the CNs would be involved
    • Difficulty thinking, dizzy, fatigue, sleepiness, slurred speech, weakness lack of coordination.
    • *If continues to be untreated: seizures coma
    • If a patient suffers from hypoglycemia frequently – they may be unaware of early symptoms – this patient should increase their BS control number to avoid hypoglycemia event.

    What are the long-term effects of DM on organs?

    • The immune system can be impacted – this can lead to infection and poor wound healing, foot ulcers,
    • Puts patients at risk for longer hospital stays – sepsis – tissue damage Vascular effects & heart failure.
    • Can be macrovascular (large arteries ) and microvascular ( small bld vessels)
    • Eyes (Retinopathy)
    • Gums (Periodontal)
    • Kidneys (Nephropathy)
    • PVD & PAD
    • Neurological effect
    • Diabetic peripheral neuropathy
    • Autonomic neuropathy – gastropareses (pt eats and stomach doesn’t empty or nauseous) ED orthostatic hypertension.
    • Urinary problems – difficulty starting stream.
    • inability to empty bladder completely
    • leads to UTI,
    • Cardiovascular disease – most likely will have some sort of cardio problem.
    • 75% higher risk for blockage.
    • fertility issues, liver dz, amputations

    Sick day management. Exercise management,

    *Sick day management keep monitoring blood glucose because blood sugar can go up. Illness or stress can trigger hyperglycemia. If a diabetic pt is admitted to hosp. and A1C is high find out why maybe underlying infection.

    • *Exercise at the same time of day (preferably when blood glucose levels are at their peak) and for the same duration each session. Inspect your feet daily after exercise.
    • Avoid exercise in extreme heat or cold. Avoid exercise during periods of poor metabolic control.
    • Eat a snack at the end of the exercise session and at bedtime and monitor the blood glucose level more frequently.
    • Know the insulins – onset, peak and duration, metformin too,  Know the insulins – onset, peak and duration, metformin too. Onset Peak Duration
    • *Rapid acting lispro – 10–15 minutes 1 hours 2-4 hrs.
    • Used for rapid reduction of glucose level, to treat postprandial hyperglycemia,  and/or to prevent nocturnal hypoglycemia.
    • *Short acting regular (Humulin R, Novolin)  30–60 minutes 2–3 hours 4–6 hours  given 20–30 minutes before a meal.
    • alone or w/long acting
    • *Intermediate acting: NPH (neutral protamine Hagedorn)  2–4 hours 4–12 hours 16–20 hours  taken after food.
    • *Very long acting: glargine (Lantus) detemir (Levemir) glargine  1-6 hrs. (no peak, cont.) 24 hrs. or 24–36hrs  Used for basal dose.

    * Metformin oral antidiabetic.

    • Inhibit production of glc by the liver. start pt @ lower dose possible and then gradually increase it.
    • Med will work to decrease the amount of
    • circulating glc. Need to monitor blood glc and take it every day. Can be used in comb w/insulin or other antidiabetic agents.
    • *Extra info!
    • *Pts on metformin discontinue the oral agent 24 to 48 hours before surgery, if glc not well controlled with diet and an oral antidiabetic agent before surgery) need to continue with insulin injections after discharge.
    • *Pt with minor surgery and stable glc level no dextrose is infused during the surgery.
    • After surgery, these patients may require small doses of regular insulin until the usual diet and oral agent are resumed.
    • *Metformin should be stopped 48 hours prior to and for 48 hours after the use of contrast agent or until kidney function is evaluated and normal.

    *NOTE: prof said peak onset and duration commit to memory!

    • The primary goal of treatment to maximize glycemic control for both type 1 and 2.
    • Achieve normal glc levels (euglycemia) without hypoglycemia while maintaining a high quality of life.

    Sick day management

    If pt sick they should increase their blood sugar checks What can increase blood sugar?

    If conscious: oral glucose administration, can give any form of a carbohydrate like juice soda, bread, or crackers.

    • Carbs that contain fat are not recommended – like ice cream.
    • Once taken recheck BS in 15 mins.
    • If unable to swallow – and has IV access- give D50 25-50 ml.
    • If no IV access- 1mg IM glucagon
    • Teach family members about the symptoms and how to treat them.
    • Check blood sugar levels 15 minutes after treatment.

    Effect of exercise – education needed.

    • *Exercise 3X wk.
    • teach pt that blood sugar will decrease so they need to know how to respond,
    • Check blood sugar before exercise, and if exercising for a long period of time check blood sugar before and after. If heavy exercise (check during).
    • They should have candy & eat it if hypoglycemia symptoms.
    • If using insulin, abdomen is best bc better absorption rate.
    • *Increased blood pressure associated with exercise may aggravate diabetic retinopathy and increase the risk of a hemorrhage into the vitreous or retina.

    Practice questions

    1. The nurse is reviewing laboratory values and notes that a patient will soon begin treatment for diabetes mellitus. Which glycosylated hemoglobin (A1C) level is on the patient’s medical record?
      1. A.1.7%
      1. B.3.4%
      1. C.5.2%
      1. D.6.8%
      1. C.6.8%

    Rationale:

    According to the American Diabetic Association diagnostic criteria, a hemoglobin A1C greater than or equal to 6.5% support the diagnosis of diabetes mellitus.

    • The nurse correlates which laboratory values as a diagnostic for DKA? Select all that apply.
      • A. serum bicarbonate of 15
      • B. negative anion gap
      • C. serum glucose of 350
      • D. positive anion gap
      • E. arterial pH of 7.36
      • C, d
    • The nurse is preparing to instruct a patient with type 1 diabetes mellitus on the complication of diabetic ketoacidosis. Which pathologic process should the nurse review with the patient about this complication?
      • A.A decreased amount of glucagon causes low protein levels
      • B. An excess amount of insulin drives all glucose into the cells
    • C. A deficit of insulin causes fat stores to be used as an energy source
      • D.An increase occurs in the breakdown of glucose molecules with hypoglycemia
      • C.A deficit of insulin causes fat stores to be used as an energy source

    Rationale: Untreated the glucose deficit in the cells causes fat store to break down to provide energy…..increased ketones….ketones are acids….causes metabolic acidosis DKA = Metabolic Acidosis

    • The nurse is providing discharge instructions to a patient with type 2 diabetes mellitus.

    Which patient statement indicates teaching about foot care at home has been successful?

    • A. “I always buy my shoes as soon as the stores open
      • B. “I will walk barefooted as long as I am in the house”
      • C. “I will check my feet for cuts and bruises every night”
      • D. “If I get a blister, I will just put alcohol on it and bandage it
      • C . “I will check my feet for cuts and bruises every night”

    Rationale: Visual inspection of the feet each day in important in preventing more serious complications. Shoes should be purchased later in the day when feet are at their largest. Footwear should always be worn. The patient should be instructed to never walk barefoot. Foot wounds should be treated by a healthcare professional.

    • 5. The nurse identifies the nursing diagnosis RISK FOR INJURY as appropriate for a patient with type 2 diabetes mellitus because of peripheral neuropathy involving both feet. Which assessment would support this diagnosis?
      • A.Loss of normal reflexes
        • B.Normal sensation to touch
        • C.States “I can’t feel my feet anymore”
        • D.States “I have been having chest pain”
        • C.States “I can’t feel my feet anymore”
    • Rationale: Diabetics are at risk for injury due to multiple factors. Neuropathies alter sensation, gait, and muscle control. There is an increased risk of accidents, burns, falls, and trauma.

    Vascular Problems:

    Vascular Problems: (Kim R)

    The 6 P’s to Assess Arterial Occlusion:

    • Pain
    • Pallor
    • Pulselessness
    • Paralysis
    • Paresthesia
    • Poikilothermic – decreased temp. in leg Vascular Problems
    • Compare & contrast signs & symptoms of arterial vs. venous – (be able to recognize thedifference )-  disorders.
    • Discuss the role of common risk     factors associated with the      of atherosclerosis.
      • Atherosclerosis – plaque buildup in artery walls. Plaque is fat deposits, cholesterol, and other substances = decreased blood flow.
        • If it becomes brittle or inflamed, it ruptures and causes blood clot = increased  blockage of arteries.
        • Peripheral Arterial Disease (PAD) is usually caused by atherosclerosis.  Atherosclerosis can cause artery narrowing (stenosis), obstruction via  thrombosis, aneurysm, ulceration, and ruptures.
        • Risk factors:
        • Modifiable Risk Factors:   Tobacco use
        •  Diets high in fat
        • Hypertension
        • Diabetes
        • Hyperlipidemia
        • Stress
        • Sedentary lifestyle
        • Elevated C-reactive protein
        • Hyperhomocysteinemia (abnormally high level of homocysteine in the blood, conventionally
        • described as above 15 μmol/L.
        • As a consequence of the biochemical reactions in which homocysteine is involved, deficiencies of vitamin B , folic acid, and vitamin B can lead  ₆₁₂ to high homocysteine levels)  Nonmodifiable Risk Factors:
        • Increased age
        • Female gender
        • Family predisposition/genetics.
    • Discuss medical, surgical, and nursing management of venous & arterial disorders.

    ARTERIAL DISORDERS

    • Arterial disorders include atherosclerosis, PAD, Upper extremity arterial occlusion disease, aortoiliac disease, aneurysms, dissecting aorta, and arterial embolisms/thrombosis.
      • PAD: commonly found in femoral-popliteal and below the knee in diabetics
      • Medical: Treated with
        • exercise like walking and arm-ergometer exercises to decrease pain associated with claudication.
          • Vasodilators, Antiplatelets: aspirin and clopidogrel, and statins used.
        • Surgical:
        • Stent in artery to hold it open,
        • Endarterectomy – removal of plaque, Arterial Bypass, and Grafts (high complication rate postop).
        • Nursing:

     lower legs below heart (neutral or dependent position),  encourage walking/moderate exercise.

    • Upper Extremity Occlusion Disease: less common and less severe. Usually result from trauma or atherosclerosis.
      • Medical: stents, bypass, grafts.
        • Nursing: BP in both arms, use of doppler flow if pulses hard to find. Same signs as in legs.
      • Aortoiliac Disease:
        • stenosis or occlusion in aorta causes butt and lower back pain, or impotence in men.
          • Surgery is necessary to fix.
          • Assess all pulse placements in arms and legs, I&Os, and abdominalsounds.
      • Aneurysms:
        • The sac dilated off weak point in an artery.
          • Thoracic aneurysms are most common and caused by atherosclerosis. Requires surgery and post-op care.
          • Dissecting Aorta: tear in aorta; more common in men. Causes chest pain that shoots to shoulder and mistaken as MI.
          • Arterial embolism and thrombosis: Acute occlusion of emboli mainly develop from thrombi in the heart from Afib/MI/CHF.
          • 6 P’s associated with acute occlusion.
      • Medical: Heparin therapy immediately! thrombolytics
      • Surgical: Embolectomy and thrombectomy
      • Nursing: bed rest before surgery, protect affected area, anticoagulation  therapy, and start walking after surgery.  Assess pulse, Doppler, and ABI.

    VENOUS DISORDERS

    • Venous disorders include DVT, PE, chronic insufficiency/Post thrombotic syndrome, leg ulcers, varicose veins.
      • DVT and PE are clinically silent.
      • DVT: unilateral thrombosis frequently accompanied by phlebitis.
      • Virchow’s Triad: 3 main risk factors leading to DVT are 1. Stasis, 2. Hyper coagulability, and 3. Vessel Wall Injury.
      • Edema, swelling, tenderness, warmth, feeling of heaviness in legs.
      • Medical: Anticoagulation therapy (prevents new thrombus formation NOT dissolve already formed thrombus), thrombolytics.
      • Nursing: monitor bleeding, elevate leg above heart, compression stockings, walking once anticoagulation therapy starts, bed exercises
      • Venous insufficiency from obstruction or blood reflux of valves.

    Post thrombotic syndrome: chronic stasis, edema, pain, and dermatitis.

    • Nursing: Elevate legs, graduated compression stockings, sleep with feet  elevated, walking, keep skin clean and dry.

    Venous ulcers – more common than PAD ulcers.

    • Occur at media land lateral malleolus, large, superficial, exudative aka WET ULCER.
      • Nursing: Debridement of ulcer, wound dressings, negative pressure wound therapy, hyperoxygenation.

    Varicose Veins: bad valves cause backflow of blood to outer, superficial veins.

    • Causes pain, dull ache, feeling of fullness, ankle edema.
      • Surgical:
        • vein stripping if needed but usually not necessary.
          • Sclerotherapy helps but does not cure them.
      • Nursing: elevate legs, change positions often, avoid restrictive clothes.

     Remember severity of pain NOT related to size of varicosities.

    • Develop a teaching plan for a patient with arterial/venous occlusive diseases. Discourage tobacco use.
      • Keep warm temperature to prevent vasoconstriction.
      • Manage stress.
      • Proper clothes that are not restrictive/tight = decreased blood flow and venous stasis.
      • Take meds as prescribed.
      • Promote exercise to increase circulation.
      • Protect skin and extremities from trauma because of delayed wound healing.
      • Wear protective shoes and pad pressure areas. Inspect feet and legs often.
      • Encourage meticulous hygiene.
      • Promote good nutrition for wound healing – Increase protein intake, vitamin A and C, and Zinc.
      • Include family in teaching, provide written material, and refer to resources such as exercise groups or support groups for smoking cessation.
    • Describe complications of peripheral vascular disorders and measures to prevent theiroccurrence.
      • Bleeds from heparin
      • Thrombosis, PE
      • Contraindications to peripheral thrombolytic therapy include active internal bleeding, cerebrovascular hemorrhage, recent major surgery, uncontrolled hypertension, and pregnancy.
      • Cellulitis, dermatitis, and ulceration from venous insufficiency
    • Identify & describe nursing intervention priorities for patient with vascular problemsincluding cellulitis.

    Cellulitis:

    • Common infection caused by limb swelling by allowing bacteria to enter subcutaneous skin layer.
      • Signs of swelling, localized redness, warmth, and pain accompanied with fever/chills/sweating.
      • Pitting “orange peel” appearance. Interventions
      • Elevate affected area 3-6 inches above heart level, apply cool/moist packs to site every 2 hours to resolve inflammation, then finish with a warm pack.
      • Caution with warm packs in patients with decreased sensory of temperature like diabetics (could cause burns).

    Thrombophlebitis – heparin, coumadin (warfarin), Lovenox – teaching involved, labs to monitor, signs of complications.

    • Prevention of clots:
      • Lovenox as prophylactic  Ambulate
      • sequential stockings/hose.
      • If clot developed, Heparin (anticoagulant) is used to prevent further clotting. (SubQ).  Monitor aPTT for dose adjustment.
      • If aPTT goes too HIGH = too much thinning blood = Give protamine sulfate(Vitamin K).
      • Monitor platelet count because it can cause issues with them. Should be greater than 100,000 platelets.
      • Monitor for bleeding (nose bleeds, bruises, gums)
      • Enoxaparin (Lovenox) given SubQ as prophylaxis and treatment of VTE.
      • Air bubbles at end DON’T push out.
      • Fewer bleeding complications than heparin.
      • Less monitoring required. Just platelet count.
      • After heparin and Lovenox use in hospital and going home, put on either Coumadin (Warfarin) or Xarelto.
      • Coumadin – Oral anticoagulant helps get up to therapeutic range so given with Heparin near the end of hospital stay.
      • Coumadin use PT and INR to monitor. Want above the “normal” range.
      • Xarelto – no antidote, caution. Expensive!
      • Meds that decrease clot formation & treat PAD:
      • Lovenox – Antithrombo.
      • Aspirin – thins blood
      • Plavix – antiplatelet
      • Pletal – anticoagulant
      • Trental – anticoagulant

    Raynaud’s disease (what is it , who is at risk , what do they need to avoid)

    • A form of intermittent arterial vasoconstriction of the fingertips and toes = coldness, pain, tingling, numbness, and pallor.
      • Primary Raynaud’s: occurs in absence of an underlying disease.
      • Secondary Raynaud’s: (Syndrome) Associated with underlying diseases like lupus, rheumatoid arthritis, scleroderma (common), trauma, or obstructive arterial lesions.
      • Triggered by stress and cold conditions.
      • Very common in women.
      • Medical management: avoid smoking and the cold.
      • Calcium channel blockers can relieve symptoms.
      • Nursing management: Avoid stressful situations, wear warm layers in cold, stop smoking.
      • Uncommon complications – gangrene and amputation.
      • Postural hypotension as an adverse effect of calcium channel blocker medications.

    For all of the above topics , recognize risk factors, symptoms, management both medical and nursing, treatment – know medication if it is indicated for diagnosis –

  • Paisley Ward iHuman Case: nr 602 Week

    In the ever-evolving landscape of medical education, innovative tools like iHuman have revolutionized the way students learn and practice patient care. One such compelling case study is that of Paisley Ward, a 16-year-old patient presenting with a persistent cough and shortness of breath.

    This article on Paisley Ward iHuman Case delves into the intricacies of Paisley’s case, offering valuable insights from NR 602 Week and exploring the various aspects of patient assessment, diagnosis, and care in a primary care setting.

    Paisley Ward iHuman Case

    What is the iHuman Case for Paisley Ward?

    The iHuman case for Paisley Ward is a virtual patient simulation designed to provide medical students and healthcare professionals with a realistic and interactive learning experience. This case study is part of the curriculum for NR 602 Week, a course focused on advanced practice nursing in primary care settings.

    Overview of NR 602 Week and its significance

    NR 602 Week is a crucial component of the nursing curriculum, particularly for those pursuing advanced practice roles. This course emphasizes the development of critical thinking skills, clinical decision-making, and comprehensive patient assessment in primary care settings. The significance of NR 602 Week lies in its ability to bridge the gap between theoretical knowledge and practical application, preparing future healthcare providers for the complexities of real-world patient care.

    Key components of the iHuman case study

    The iHuman case study for Paisley Ward encompasses several key components that mirror real-life patient encounters:

    1. Patient history and presentation
    2. Physical examination
    3. Diagnostic reasoning
    4. Treatment planning
    5. Patient education

    These components work together to create a holistic learning experience, allowing students to practice their skills in a safe, controlled environment.

    Understanding Paisley Ward’s scenario

    Paisley Ward is a 16-year-old patient who presents to the primary care clinic with a chief complaint of cough and shortness of breath. The case provides students with an opportunity to explore the complexities of respiratory issues in adolescents, considering various factors such as environmental triggers, medical history, and lifestyle influences.

    How to conduct a thorough physical exam in the iHuman case?

    Conducting a thorough physical examination is crucial in accurately assessing Paisley Ward’s condition. The iHuman case provides a platform for students to practice this essential skill virtually.

    Steps to perform a physical exam effectively

    1. General appearance: Observe Paisley’s overall demeanor, posture, and any signs of distress.
    2. Vital signs: Check temperature, heart rate, respiratory rate, and blood pressure.
    3. Head and neck examination: Assess for any signs of nasal congestion, sinus tenderness, or lymphadenopathy.
    4. Chest examination: Perform inspection, palpation, percussion, and auscultation of the lungs and heart.
    5. Abdominal examination: Rule out any referred pain or related gastrointestinal issues.
    6. Extremities: Check for any signs of cyanosis or clubbing.

    What to look for in a patient with cough

    When examining a patient like Paisley who presents with a cough, it’s essential to pay close attention to the following:

    1. Cough characteristics: Frequency, duration, and quality (dry or productive)
    2. Associated symptoms: Wheezing, chest pain, or shortness of breath
    3. Respiratory rate and pattern: Any signs of labored breathing or use of accessory muscles
    4. Lung sounds: Presence of wheezes, crackles, or diminished breath sounds
    5. Sputum production: Color, consistency, and amount if present

    Importance of patient history in diagnosis

    Obtaining a comprehensive patient history is crucial in formulating an accurate diagnosis. In Paisley’s case, the history reveals several important details:

    1. Duration of symptoms: Cough for the last 3 weeks
    2. Associated symptoms: Shortness of breath that started 3 weeks ago
    3. Medical history: History of reactive airway disease and eczema
    4. Environmental factors: Neighbors smoke within the building
    5. Stress factors: Experiencing more stress lately due to her parents’ hectic work schedules

    This information provides valuable context for understanding Paisley’s current condition and guides the differential diagnosis process.

    What are the differential diagnoses for Paisley Ward?

    Developing a list of potential differential diagnoses is a critical step in the clinical reasoning process. For Paisley Ward, considering her presenting symptoms and history, the following conditions should be considered:

    Common conditions related to cough and shortness of breath

    1. Acute asthma exacerbation
    2. Bronchitis
    3. Pneumonia
    4. Upper respiratory tract infection
    5. Allergic rhinitis
    6. Gastroesophageal reflux disease (GERD)
    7. Paradoxical vocal cord movement
    8. Anxiety-induced hyperventilation

    Analyzing the HPI of Paisley Ward

    The History of Present Illness (HPI) for Paisley Ward provides crucial information for narrowing down the differential diagnoses. Key points from her HPI include:

    1. Persistent cough for 3 weeks
    2. Shortness of breath occurring with the cough
    3. No chest pain reported
    4. History of reactive airway disease
    5. Recent increase in stress levels

    These details help focus the diagnostic process and guide further questioning and examination.

    Evaluating the role of ROS in differential diagnosis

    The Review of Systems (ROS) plays a vital role in the differential diagnosis process. For Paisley’s case, the ROS might reveal:

    1. Respiratory: Presence of wheezing or chest tightness
    2. ENT: History of congestion and runny nose
    3. Skin: Any recent exacerbations of eczema
    4. Gastrointestinal: Possible symptoms of GERD
    5. Psychological: Stress levels and anxiety symptoms

    By systematically reviewing these systems, healthcare providers can gather additional information to support or rule out potential diagnoses.

    How to obtain a comprehensive HPI for Paisley Ward?

    Obtaining a comprehensive History of Present Illness (HPI) is crucial for accurate diagnosis and treatment planning. Here’s how to approach this process effectively:

    Steps in collecting an effective HPI

    1. Start with open-ended questions to allow Paisley to describe her symptoms in her own words.
    2. Follow up with specific questions to clarify details about the onset, duration, and characteristics of her symptoms.
    3. Explore any aggravating or alleviating factors.
    4. Inquire about any previous episodes or similar symptoms.
    5. Ask about any self-treatment measures she has tried.

    Asking 2 open-ended patient-centric questions

    To encourage Paisley to share more about her experience, consider asking these open-ended questions:

    1. “Can you tell me more about when you first noticed your cough and shortness of breath?”
    2. “How have these symptoms been affecting your daily activities and quality of life?”

    These questions allow Paisley to provide a narrative of her illness, often revealing important details that might not be captured through direct questioning.

    Identifying key symptoms and their duration

    When collecting the HPI, it’s crucial to identify and document the following:

    1. Cough: Duration of 3 weeks, characteristics (dry or productive)
    2. Shortness of breath: Onset coinciding with the cough, severity, and triggers
    3. Associated symptoms: Presence of wheezing, chest tightness, or fatigue
    4. Environmental factors: Exposure to smoke from neighbors
    5. Stress levels: Recent increase due to parents’ work schedules

    Documenting these key symptoms and their duration provides a clear picture of Paisley’s condition and helps in formulating an appropriate treatment plan.

    What new insights can be derived from NR 602 Week 5?

    As the case study progresses into NR 602 Week 5, new insights emerge that shed light on Paisley’s condition and the broader implications for primary care practice.

    Understanding changes in Paisley Ward’s condition

    Week 5 may reveal changes in Paisley’s symptoms, response to initial treatments, or new findings from additional tests. These changes could include:

    1. Improvement or worsening of cough and shortness of breath
    2. Results from pulmonary function tests or chest X-rays
    3. Response to any prescribed medications
    4. Emergence of new symptoms or concerns

    Impact of recent findings on primary care

    The new insights gained from Paisley’s case have several implications for primary care practice:

    1. Importance of longitudinal follow-up in chronic respiratory conditions
    2. Need for comprehensive environmental assessments in respiratory cases
    3. Role of stress management in overall health outcomes
    4. Significance of patient education in managing chronic conditions

    Lessons learned from the case study

    Key takeaways from Paisley Ward’s case include:

    1. The importance of considering both physiological and psychosocial factors in patient care
    2. The value of a thorough history and physical examination in diagnosis
    3. The need for a patient-centered approach in developing treatment plans
    4. The role of interdisciplinary collaboration in managing complex cases

    What resources are available for studying Paisley Ward’s case?

    To fully benefit from the Paisley Ward iHuman case, students can leverage various resources to enhance their learning experience.

    Utilizing study documents effectively

    Study documents provided for the Paisley Ward case may include:

    1. Case background information
    2. Laboratory and diagnostic test results
    3. Guidelines for physical examination techniques
    4. Differential diagnosis checklists
    5. Treatment protocols for common respiratory conditions

    These documents serve as valuable references throughout the case study and can be used to cross-check findings and decisions.

    Where to find additional information on iHuman cases

    Additional information on iHuman cases can be found through:

    1. The iHuman platform’s resource library
    2. Course-specific materials provided by instructors
    3. Peer-reviewed journals focusing on medical education and simulation
    4. Online medical databases and resources like PubMed and UpToDate

    Leveraging Studocu for in-depth analysis

    Studocu, an online platform for sharing study materials, can be a valuable resource for students working on the Paisley Ward case. It may offer:

    1. Shared notes from peers who have completed the case
    2. Study guides and summaries related to NR 602 Week
    3. Discussion forums for collaborative learning
    4. Sample care plans and SOAP notes

    However, it’s important to use these resources as supplements to official course materials and to maintain academic integrity.

    Related Article: NR 602 Week 7 iHuman Case 5

    FAQs

    What does iHuman do?

     iHuman is a virtual patient simulation platform that provides interactive, case-based learning experiences for healthcare students and professionals. It allows users to practice patient assessment, diagnosis, and treatment planning in a risk-free environment.

    Is iHuman a documentary?

    No, iHuman is not a documentary. It is an educational software platform used for medical and nursing education to simulate patient encounters.

    How to access iHuman?

     iHuman is typically accessed through educational institutions that have subscribed to the platform. Students and faculty members are usually provided with login credentials to access the system through a web browser.

    Who is the founder of iHuman?

     iHuman was developed by i-Human Patients, Inc., which was later acquired by Kaplan, Inc. The specific founder’s name is not widely publicized, as it’s a product of a company rather than an individual’s creation.

  • Focused Exam on COPD and Ellipta A Shadow Health Transcript Summary

    Chronic Obstructive Pulmonary Disease (COPD) is a progressive respiratory condition that affects millions of people worldwide. As one of the leading causes of morbidity and mortality, understanding COPD and its management is crucial for healthcare providers and patients alike.

    This article 0n “Focused Exam on COPD and Ellipta A Shadow Health Transcript Summary” will delve into the various aspects of COPD, including diagnosis, treatment options, and the role of medications like Ellipta in managing this chronic lung disease.

    Focused Exam on COPD and Ellipta A Shadow Health Transcript Summary

    What is COPD and How is it Diagnosed?

    COPD, or Chronic Obstructive Pulmonary Disease, is a group of lung diseases characterized by airflow limitation and breathing difficulties. The two main forms of COPD are chronic bronchitis and emphysema. These conditions often coexist and can significantly impact a person’s quality of life.

    What are the common signs of COPD?

    The primary symptoms of COPD include:

    1. Persistent cough (often referred to as “smoker’s cough”)
    2. Increased mucus production
    3. Shortness of breath, especially during physical activities
    4. Wheezing
    5. Chest tightness
    6. Frequent respiratory infections

    As the disease progresses, patients may experience more severe symptoms, including:

    1. Fatigue
    2. Weight loss
    3. Swelling in the ankles, feet, or legs
    4. Cyanosis (bluish discoloration of the lips or fingernail beds)

    How is the diagnosis of COPD confirmed?

    Diagnosing COPD involves a comprehensive approach that includes:

    1. Medical history: Healthcare providers will inquire about smoking history, exposure to lung irritants, and family history of COPD.
    2. Physical examination: A thorough examination of the chest and lungs is performed to detect any abnormalities in breathing patterns or lung sounds.
    3. Pulmonary function tests: These tests, particularly spirometry, are crucial in diagnosing COPD. The most important measurements include:
      • Forced Expiratory Volume in 1 second (FEV1)
      • Forced Vital Capacity (FVC)
      • FEV1/FVC ratio
    4. Imaging studies: Chest X-rays and CT scans can help identify lung damage and rule out other conditions.
    5. Arterial blood gas analysis: This test measures oxygen and carbon dioxide levels in the blood, providing information about lung function.

    What role does a chest radiograph play in COPD diagnosis?

    A chest radiograph, or chest X-ray, plays a supportive role in COPD diagnosis. While it cannot definitively diagnose COPD, it can:

    1. Rule out other lung conditions that may mimic COPD symptoms
    2. Identify lung hyperinflation, a common feature in advanced COPD
    3. Detect complications such as pneumonia or lung cancer
    4. Evaluate the size and shape of the heart, which may be affected in severe COPD

    It’s important to note that chest radiographs may appear normal in early stages of COPD, and therefore, should not be used as the sole diagnostic tool.

    What are the Treatment Options for Patients with COPD?

    Managing COPD requires a multifaceted approach that combines pharmacological and non-pharmacological interventions. The goal of treatment is to relieve symptoms, prevent exacerbations, and slow disease progression.

    How does pulmonary rehabilitation assist COPD patients?

    Pulmonary rehabilitation is a comprehensive program that helps COPD patients improve their overall health and quality of life. It typically includes:

    1. Exercise training: To improve cardiovascular fitness and muscle strength
    2. Breathing techniques: To help manage breathlessness
    3. Nutritional counseling: To address weight issues common in COPD
    4. Education: To help patients better understand and manage their condition
    5. Psychological support: To address anxiety and depression often associated with COPD

    Studies have shown that pulmonary rehabilitation can significantly improve exercise capacity, reduce hospitalization rates, and enhance quality of life for COPD patients.

    What medications are commonly prescribed for COPD treatment?

    Several classes of medications are used to manage COPD:

    1. Bronchodilators: These medications relax airway muscles and improve airflow. They include:
      • Short-acting beta-2 agonists (e.g., albuterol)
      • Long-acting beta-2 agonists (e.g., salmeterol, formoterol)
      • Short-acting anticholinergics (e.g., ipratropium)
      • Long-acting anticholinergics (e.g., tiotropium, umeclidinium)
    2. Inhaled corticosteroids: These reduce airway inflammation and are often combined with long-acting bronchodilators for patients with frequent exacerbations.
    3. Phosphodiesterase-4 inhibitors: Medications like roflumilast can help reduce inflammation and exacerbations in severe COPD.
    4. Antibiotics: Used to treat respiratory infections that can trigger COPD exacerbations.
    5. Oxygen therapy: Supplemental oxygen is prescribed for patients with severe COPD and low blood oxygen levels.

    How does the Ellipta inhaler work for COPD management?

    The Ellipta inhaler is a dry powder inhaler developed by GSK (GlaxoSmithKline) for the management of COPD and asthma. It delivers various medications, including:

    1. Fluticasone furoate/vilanterol (Breo Ellipta): A combination of an inhaled corticosteroid and a long-acting beta-2 agonist
    2. Umeclidinium/vilanterol (Anoro Ellipta): A combination of a long-acting anticholinergic and a long-acting beta-2 agonist

    The Ellipta inhaler works by delivering a precise dose of medication directly to the lungs. Its design makes it easy to use, requiring fewer steps compared to some other inhalers. This can improve medication adherence, which is crucial for effective COPD management.

    Clinical trials have shown that medications delivered via the Ellipta inhaler can significantly improve lung function, reduce exacerbations, and enhance quality of life for COPD patients.

    Understanding COPD Exacerbations

    COPD exacerbations are acute worsening of respiratory symptoms that require additional therapy. They can significantly impact a patient’s quality of life and accelerate disease progression.

    What triggers a COPD exacerbation?

    Common triggers for COPD exacerbations include:

    1. Respiratory infections (viral or bacterial)
    2. Air pollution
    3. Exposure to irritants (e.g., smoke, dust)
    4. Changes in weather
    5. Discontinuation of COPD medications
    6. Comorbid conditions (e.g., heart failure, pulmonary embolism)

    What are the symptoms of a COPD exacerbation?

    Symptoms of a COPD exacerbation typically include:

    1. Increased breathlessness
    2. Increased cough frequency and severity
    3. Changes in sputum color or volume
    4. Chest tightness
    5. Fatigue
    6. Fever (in case of infection)
    7. Confusion or drowsiness (in severe cases)

    How can patients with COPD prevent exacerbations?

    Preventing COPD exacerbations is crucial for maintaining lung function and quality of life. Strategies include:

    1. Adherence to prescribed medications
    2. Smoking cessation
    3. Regular vaccinations (influenza and pneumococcal)
    4. Avoiding triggers and air pollutants
    5. Proper inhaler technique
    6. Pulmonary rehabilitation
    7. Regular follow-ups with healthcare providers
    8. Early recognition and treatment of symptoms

    What is the Role of Subjective Data in COPD Management?

    Subjective data, or information provided by the patient about their symptoms and experiences, plays a crucial role in COPD management.

    How do healthcare providers use patient data in treatment planning?

    Healthcare providers use patient data to:

    1. Assess symptom severity and impact on daily life
    2. Identify triggers for exacerbations
    3. Evaluate treatment efficacy
    4. Adjust medication dosages or types
    5. Determine the need for additional interventions (e.g., oxygen therapy, pulmonary rehabilitation)
    6. Monitor disease progression over time

    What subjective data should be collected during a focused exam?

    During a focused exam for COPD, healthcare providers should collect the following subjective data:

    1. Severity and frequency of breathlessness
    2. Cough characteristics (frequency, productivity, color of sputum)
    3. Impact of symptoms on daily activities and quality of life
    4. Frequency and severity of exacerbations
    5. Smoking history and current status
    6. Occupational exposure to lung irritants
    7. Medication adherence and side effects
    8. Sleep quality and presence of nocturnal symptoms
    9. Exercise tolerance and limitations

    How does subjective data influence COPD treatment decisions?

    Subjective data significantly influences COPD treatment decisions by:

    1. Guiding medication adjustments based on symptom control
    2. Determining the need for additional therapies (e.g., pulmonary rehabilitation, oxygen therapy)
    3. Identifying barriers to treatment adherence
    4. Assessing the effectiveness of current management strategies
    5. Informing decisions about lifestyle modifications
    6. Helping to recognize and prevent exacerbations early

    Evaluating COPD Results and Lung Function

    Assessing lung function is crucial for diagnosing COPD, monitoring disease progression, and evaluating treatment effectiveness.

    What pulmonary function tests are used in COPD assessment?

    Key pulmonary function tests used in COPD assessment include:

    1. Spirometry: Measures FEV1, FVC, and FEV1/FVC ratio
    2. Lung volume measurements: Assess total lung capacity and residual volume
    3. Diffusing capacity: Evaluates gas exchange efficiency
    4. Six-minute walk test: Assesses exercise capacity and oxygen requirements
    5. Arterial blood gas analysis: Measures oxygen and carbon dioxide levels in the blood

    How are COPD results interpreted by healthcare providers?

    Healthcare providers interpret COPD results by:

    1. Comparing measured values to predicted values based on age, height, sex, and ethnicity
    2. Assessing the degree of airflow limitation using FEV1 % predicted
    3. Evaluating the FEV1/FVC ratio to confirm obstructive lung disease
    4. Considering the presence of reversibility after bronchodilator administration
    5. Assessing lung volumes to detect hyperinflation
    6. Interpreting diffusing capacity to evaluate the presence of emphysema
    7. Analyzing arterial blood gases to assess oxygenation and ventilation

    What is the significance of airflow limitation in COPD?

    Airflow limitation is the hallmark of COPD and has several important implications:

    1. Diagnosis: An FEV1/FVC ratio < 0.7 post-bronchodilator confirms airflow obstruction
    2. Disease severity: The degree of airflow limitation (based on FEV1 % predicted) helps classify COPD severity
    3. Prognosis: Lower FEV1 values are associated with increased mortality and exacerbation risk
    4. Treatment decisions: The severity of airflow limitation guides therapeutic choices
    5. Monitoring: Changes in FEV1 over time reflect disease progression or treatment efficacy

    What Lifestyle Changes Can Help Manage COPD?

    Lifestyle modifications play a crucial role in COPD management, complementing medical treatments and improving overall health outcomes.

    How important is smoking cessation for COPD patients?

    Smoking cessation is the single most important intervention for COPD patients who smoke. It can:

    1. Slow the rate of lung function decline
    2. Reduce exacerbation frequency
    3. Improve response to medications
    4. Enhance overall quality of life
    5. Decrease mortality risk

    Healthcare providers should offer support, counseling, and pharmacological interventions to help patients quit smoking.

    What role does oxygen therapy play in COPD treatment?

    Oxygen therapy is a vital component of treatment for patients with severe COPD and chronic hypoxemia. It can:

    1. Improve survival in patients with severe resting hypoxemia
    2. Reduce pulmonary hypertension
    3. Improve exercise capacity and quality of life
    4. Reduce hospitalizations and exacerbations

    Oxygen therapy may be prescribed for use during sleep, exercise, or continuously, depending on the patient’s needs.

    How can patients with COPD improve their overall lung health?

    Patients with COPD can improve their lung health through various strategies:

    1. Regular exercise: Improves cardiovascular fitness and muscle strength
    2. Proper nutrition: Maintains a healthy weight and supports immune function
    3. Avoiding triggers: Minimizes exposure to air pollutants and irritants
    4. Stress management: Reduces anxiety and improves overall well-being
    5. Vaccination: Prevents respiratory infections that can exacerbate COPD
    6. Proper inhaler technique: Ensures effective medication delivery
    7. Breathing exercises: Improves lung efficiency and reduces breathlessness
    8. Adequate sleep: Supports overall health and immune function
    9. Staying hydrated: Helps maintain proper mucus consistency

    Related Article

    Shadow Health Focused Exam, COPD- Subjective Data Collection

    FAQs (Focused Exam on COPD and Ellipta A Shadow Health Transcript Summary)

    1. What are the primary symptoms of COPD? The primary symptoms of COPD include persistent cough, increased mucus production, shortness of breath (especially during physical activities), wheezing, and chest tightness.
    2. Describe the pathophysiology of COPD. COPD is characterized by chronic inflammation of the airways, leading to structural changes, narrowing of the airways, and destruction of lung tissue. This results in airflow limitation, air trapping, and reduced gas exchange capacity.
    3. What are the common risk factors for developing COPD? Common risk factors for COPD include smoking, long-term exposure to air pollutants or occupational dust, genetic factors (alpha-1 antitrypsin deficiency), history of childhood respiratory infections, and advanced age.
    4. How is COPD diagnosed? COPD is diagnosed through a combination of clinical evaluation, spirometry (which confirms airflow obstruction), and other pulmonary function tests. Additional tests like chest X-rays and CT scans may be used to assess lung damage and rule out other conditions.
  • Differences between Genogram and Ecomap with Examples

    Introduction: Genogram and Ecomap

    Genograms and ecomaps are key in understanding relationships, whether within a family or between an individual and their social environment. These visual representations help nurses understand both the internal family dynamics and external support systems that influence a patient’s health outcomes.

    A genogram is a sophisticated visual tool that goes beyond a traditional family tree to map relationships, health patterns, and generational influences within the family structure. Meanwhile, an ecomap (sometimes referred to as an eco-map) illustrates how individuals and families connect with their external environment, including community organizations and support networks.

    Importance of Genograms and Ecomaps

    Healthcare providers, especially nurses, benefit tremendously from incorporating these visual assessment techniques into their practice. Here’s why:

    • Holistic Assessment: Genograms provide crucial insights into hereditary conditions and family health patterns that might impact current treatment plans.
    • Identifying Resources: A social worker might use an ecomap to understand available support systems when developing discharge plans.
    • Uncovering Hidden Factors: A genogram may uncover relationship dynamics that affect medication adherence or treatment compliance.
    • Communication Tool: These diagrams create a visual language that makes it easier to understand complex family situations during interdisciplinary team meetings.

    Genogram and Ecomap Guide with Examples

    Here’s a step-by-step guide for creating both a genogram and an ecomap with common genogram and ecomap symbols, including examples.

    Let’s start with a genogram:

    Guide on Creating a Genogram in Nursing

    Common Genogram Symbols

    genogram and ecomap symbols

    Step 1: Gather Comprehensive Information

    Start by collecting detailed information spanning at least three generations. Include:

    • Names, birth/death dates
    • Health conditions, with special attention to substance abuse patterns
    • Major life events and transitions
    • Relationship qualities between family members

    Step 2: Select Your Central Focus

    For nursing assessments, typically place the patient (client) at the center of the genogram. This provides context for understanding how family history impacts their current health status.

    Step 3: Construct the Basic Framework

    • Use squares for males, circles for females
    • Arrange generations horizontally, with oldest at top
    • Connect partners with horizontal lines
    • Draw vertical lines connecting parents to children
    • Use standardized symbols for marriage, divorce, and other relationships

    Step 4: Add Relationship Indicators

    Different line styles between individuals are used to indicate relationship quality:

    • Solid lines for strong, positive connections
    • Jagged lines for conflictual relationships
    • Dotted lines for distant or estranged relationships
    • Use colors or patterns to highlight specific traits or conditions that run in the family.
    • Create a legend explaining what each color or pattern represents.

    Step 5: Incorporate Health Information

    As a nursing student, this step is particularly important. Document:

    • Chronic conditions
    • Mental health diagnoses
    • Substance use patterns
    • Age and cause of death for deceased family members

    Step 6: Include Emotional Relationships

    • Use different line styles to show the emotional bonds between family members.
    • Indicate particularly strong alliances or estranged relationships.

    Step 7: Add Contextual Information

    • Include relevant social, cultural, or historical events that impacted the family.
    • Note major moves, changes in socioeconomic status, or other significant life changes.

    Step 8: Review and Refine

    • Check the genogram for accuracy and completeness.
    • Ensure all symbols and lines are clear and consistent.
    • Add any additional notes or explanations as needed.

    Step 9: Create a Legend

    • Provide a clear legend explaining all symbols, lines, and colors used in your genogram.
    • This helps others interpret your genogram correctly.

    Step 10: Update as Needed

    • Genograms are living documents. Update them as new information becomes available or as family circumstances change.

    Genogram Example

    Comprehensive SOAP Note for Dysuria Patient with Family Genome

    Patient Initials: ___J.S____ Age: 37 years old_______ Gender: _Female______

    SUBJECTIVE DATA:                                                          

     Chief Complaint (CC): I have a burning sensation during urination.’

    History of Present Illness (HPI): Jane Smith (J.S), a 37-year-old woman, is a third-generation Asian American woman whose grandparents came from Japan. She presents to the clinic complaining of discomfort around the pelvic area and a burning sensation when passing urine. She also reports the increased frequency of urination, passing water three times in less than one and half hours. J.S admits experiencing a strong urge to urinate over the last six days and hastens to add that the urine looks cloudy when accompanied by a fish-like odor. She admits she has been active with several male partners over the last three years, with her partners not using condoms or other barrier protection. She denies nausea, vomiting, myalgia blood in urine, vulvar/ vaginal irritation; she also reports a white vaginal discharge and no flank pain.

    Genogram Example

    Guide on Creating an Ecomap in Nursing

    Basic Ecomap Structure

    genogram and ecomap examples
    Figure 2: Ecomap Symbols Chart

    Step 1: Identify Your Central Focus

    Place your patient or family unit in the center circle of the ecomap. This forms the foundation for mapping external connections.

    Step 2: Map Key External Systems

    Identify and draw circles representing significant external influences, such as:

    • Healthcare systems
    • Educational institutions
    • Workplace environments
    • Religious/spiritual communities
    • Government assistance programs
    • Friend networks

    Step 3: Establish Connection Types

    Draw lines between the central circle and external systems, where:

    • Solid lines represent strong, supportive connections
    • Dashed lines indicate tenuous relationships
    • Jagged lines show stressful or conflictual interactions

    Step 4: Indicate Flow Direction

    Add arrows to show energy and resource exchange:

    • Single-headed arrows for one-way support
    • Double-headed arrows for reciprocal relationships
    • Note specific types of support (e.g., “emotional,” “financial,” “informational”)

    Step 5: Identify Stressors and Supports

    Label connections clearly to indicate whether each external system functions as:

    • A source of support
    • A significant stressor
    • Both support and stress (common with family relationships)

    Genogram Example

    Summative Assessment: Family and Community Assessment

    Identifying Data

    The child, C.K, is a second born in a family of four. Her mother left home when she was seven and a half years following domestic violence. Additionally, her elder sister died of pneumonia at six years. Therefore, C.K. and her other two younger siblings, N.K, six years, and L.K, three years living with their father.

    Developmental Stage and Family’s History

    They are from a below-average family and barely afford two meals a day. The father, Mr. K, is an alcoholic and unemployed, making it difficult to provide for his children. Mr. K reported that his wife could not keep up with the challenges, and she always despised him, which resulted in frequent domestic violence, where she decided to leave, leaving behind the children. She was also an alcoholic and used heroin which affected her ability to raise her children.

    The children are malnourished as they rarely get enough food. C.K is the eldest child among the three and does most of the chores in the house, including babysitting her youngest sibling and cleaning. However, she misses school most of the time to take care of her siblings or the father’s financial constraints. She claims that her father has physically abused her severely. In this case, the father denies her a chance to mingle with other children or adults in the neighborhood to avoid sharing the incidences and is always harsh with her. As a result, she is mostly restricted from leaving her house.

    However, she ended up sharing what she was going through with her neighbor after the pain became unbearable. During this time, the neighbor brought her to the hospital for a check-up. C.K. seemed sickly, weak, unkempt, withdrawn, and underweight for her age. We found that she had been physically abused severally and was wounded after the examination. She was then transferred to the pediatric wing for further treatment and check-up. We then reported the case to the police to take legal action against Mr. K. We found him at his home with the other two unkempt children, who were visibly unkempt. He was arrested and charged with the abuse. The other children were also taken to the hospital for further examination. They were malnourished and weak. After receiving treatment, C.K. and her siblings were taken to a child rescue center to receive better care. They have improved in the last two weeks, and plans are underway on how C.K. can rejoin school once she is fully recovered.

    Environmental Data

    The family lives in an isolated area. They live in a decapacitated two-bedroomed house. The house is not properly roofed, and C.K. reports that water leaks into the house at times during the rainy seasons. The living conditions are unsafe, and they lack basic needs such as water and toilets. In this regard, the environment places the family at risk of waterborne diseases and the children at risk of respiratory complications.

    Family Structure

    The family’s structure can be defined as a single-parent family. It comprises Mr. K as the family head and his three children. However, they were a nuclear family until the mother left home, never to be seen again.

    Family Functions

    The only family function in Mr. K’s home is the social control of the children. In this case, they are limited to how the children should socialize with the external society. However, it is harmful to prevent C.K. from revealing that he has been physically abusing C.K. severally. Nonetheless, the children do not socialize with others; they do not receive proper maintenance, physical care, love, and nurture, and the father does not produce any goods or services.

    Family Stress and Coping

    Mr. K and the children have stress but no appropriate coping strategies. Specifically, Mr. K has to provide for his three young children but does not have the means to provide. In this case, he takes alcohol to cope with the situation. The two younger children cry when they lack food.

    Family Composition

    As earlier identified, the family is composed of four people, Mr. K, C.K, N.K, and L.K. However, they were initially a family of six, but C.K.’s elder sister died of pneumonia, and the mother no longer stays with them. While the father is a single parent, he finds it challenging to provide for the children all by himself. He also abuses alcohol which negatively affects his ability to provide and take care of his children, leading to child neglect and abuse.

    Ecomap                                     

    Ecomap Example

    The Critical Differences: When to Use Genograms vs. Ecomaps

    While like genograms in some ways, ecomaps serve distinct purposes in nursing assessment:

    Genogram FocusEcomap Focus
    Internal family dynamicsExternal support systems
    Generational health patternsCurrent social relationships
    Hereditary conditionsCommunity services access
    Family relationship qualityResource availability

    The right tool depends on your specific assessment needs. Often, the most comprehensive picture emerges when both tools are used together, allowing healthcare providers to understand both internal and external factors that shape patient health.

    Frequently Asked Questions (FAQs) on Genograms and Ecomaps

    What is a genogram and ecomap?

    A genogram is a visual representation of a person’s family relationships and medical history across multiple generations. It uses symbols and lines to depict family structures, hereditary patterns, and psychological factors.

    An ecomap, on the other hand, is a diagram that shows the social and personal relationships of an individual or family with their environment. It illustrates connections to external systems such as schools, work, healthcare, and community resources.

    What is the purpose of an ecomap?

    The primary purposes of an ecomap are:

    • To visualize an individual’s or family’s connections to their social environment
    • To identify sources of support and stress in a person’s life
    • To assess the strength and quality of relationships with various systems
    • To help in planning interventions by highlighting areas of need or potential resources
    • To facilitate discussions about a person’s social network and support system

    What is a genogram used for?

    Genograms serve several purposes:

    • Visualizing family structures and relationships across generations
    • Identifying patterns of health, behavior, or relationships within a family
    • Exploring family dynamics and potential hereditary issues
    • Facilitating discussions about family history and connections
    • Assisting in medical and psychological assessments by revealing potential genetic or behavioral patterns
    • Aiding in family therapy by providing a clear picture of family relationships and patterns

    What is the difference between a genogram and a culturagram?

    While both tools are used to understand families, they have different focuses:

    Genogram:

    • Focuses on family structure, relationships, and patterns across generations
    • Uses standardized symbols to represent family members and relationships
    • Typically includes medical and psychological information

    Culturagram:

    • Focuses on the cultural aspects of a family or individual
    • Highlights factors like reasons for migration, legal status, language, health beliefs, and cultural values
    • Designed to understand the impact of culture on family dynamics and individual behavior
    • Does not use standardized symbols but rather text boxes or sections for different cultural elements

    What are the disadvantages of genograms?

    While genograms are useful tools, they do have some limitations:

    • They can oversimplify complex family relationships
    • They may not capture the full emotional quality of relationships
    • They can be time-consuming to create, especially for large families
    • They may bring up sensitive or painful family issues
    • They rely on the accuracy of reported information, which can be subjective or incomplete
    • They provide a static view and need regular updating to remain relevant
    • They may not adequately represent non-traditional family structures without modification

    Is family mapping the same as a genogram?

    While family mapping and genograms are related concepts, they are not exactly the same:

    • Genogram: A specific, structured tool using standardized symbols to represent family relationships, medical history, and patterns across generations.
    • Family Mapping: A broader term that can include various ways of visually representing family relationships. It might use genograms, but could also include other methods like family trees, timelines, or more freeform representations of family connections.

    In essence, a genogram is a specific type of family mapping, but not all family mapping is necessarily a genogram. Family mapping might be less formal and more flexible in its representation, while genograms follow more standardized conventions.

    How do ecomaps use different symbols than genograms?

    Ecomaps use circles connected by various line types, while genograms provide more detailed representations of individuals using gender-specific symbols. Ecomaps show external connections, whereas genograms display family relationships.

    Can I use digital tools to create these assessments?

    Yes, several digital platforms offer templates for creating professional genograms and ecomaps. However, many nursing students find that hand-drawing these tools during initial learning helps develop a deeper understanding of the relationships they represent.

    How often should I update these tools when working with patients?

    These visual tools represent a snapshot in time. In nursing practice, it’s advisable to update them when significant changes occur in the patient’s condition, family structure, or support system—particularly during major life transitions or health crises.

    What if my patient doesn’t want to share certain information?

    Respect for privacy is paramount. Document only the information your patient consents to share, and be sensitive to cultural differences in how family information is discussed. Remember that unauthorized disclosure of sensitive information is strictly prohibited under privacy regulations.