Search results for: “mental health”

  • Jake Mason iHuman Case Study Example

    Jake Mason is an 18-month-old male presenting with a chief complaint of “cough and difficulty breathing” brought to urgent care by his father. The toddler has been experiencing worsening respiratory symptoms, including a productive cough worse at night, fever, and decreased appetite over the past 2-3 days.

    In this comprehensive guide, we’ll walk you through how to approach his case, from initial history-taking through physical examination to the final diagnosis of pneumonia and respiratory management. You’ll learn the key clinical reasoning steps specific to pediatric respiratory cases, what the iHuman grading rubric expects, and a complete step-by-step solution to help you confidently navigate this challenging pediatric simulation.

    Jake Mason iHuman

    Jake Mason iHuman Case Overview (Doorway Information)

    Patient Overview: Jake Mason is an 18-month-old male presenting with a chief complaint of “cough and difficulty breathing” that has been worsening over the past 2-3 days. His father reports that Jake has been having a productive cough that is significantly worse at night, accompanied by fever and decreased appetite. The child has been exposed to secondhand smoke and sick children at daycare.

    Key Background Information:

    • Age/Gender: 18-month-old male
    • Chief Complaint: Cough and difficulty breathing
    • Duration: 2-3 days of worsening symptoms
    • Cough Characteristics: Productive with yellow sputum, worse at night
    • Associated Symptoms: Fever, rhinorrhea, decreased appetite
    • Environmental Exposures: Secondhand smoke, sick children at daycare
    • Presenting Concerns: Respiratory distress, intercostal retractions, fine crackles
    • Current Status: Brought to urgent care by father for evaluation

    The patient appears ill and in mild respiratory distress with visible work of breathing. His presentation is classic for pediatric lower respiratory tract infection, making this an excellent case for learning systematic pediatric respiratory assessment and age-specific management strategies.

    Jake Mason iHuman (18 months old male) – Respiratory Assessment

    • CC: Cough and difficulty breathing
    • MSAP: Productive cough worse at night with yellow sputum, fever, respiratory distress with intercostal retractions
    • Associated symptoms: Rhinorrhea, decreased appetite, exposure to secondhand smoke
    • Environmental factors: Daycare exposure to sick children, secondhand smoke exposure
    • Respiratory distress indicators: Fine crackles, intercostal retractions, increased work of breathing

    History Questions:

    • How can I help you today?
    • When did you first notice Jake having trouble breathing?
    • Can you describe his cough? (dry, wet, barking, honking)
    • Has he been producing any sputum? What color?
    • Is the cough worse at any particular time of day?
    • Has he had a fever? How high?
    • How has his appetite been?
    • Has he been drinking fluids normally?
    • Any changes in his activity level or playfulness?
    • Has he been exposed to anyone who’s been sick?
    • Does anyone in the household smoke?
    • What is his vaccination status?
    • Has he had any similar episodes before?
    • Any family history of asthma or respiratory problems?
    • Has he been to daycare recently?
    • Any known allergies?
    • Is he taking any medications?
    • Any recent travel?
    • How has his sleep been affected?
    • Any difficulty feeding or taking bottles?
    • Have you noticed any color changes around his mouth or fingernails?
    • Any unusual breathing patterns or sounds?

    Physical Exam:

    • Vitals: temperature, heart rate, respiratory rate, blood pressure, oxygen saturation
    • General appearance: level of distress, activity level, alertness
    • Skin: color, temperature, capillary refill
    • HEENT:
      • Examine the ears, nose, and throat
      • Look for signs of upper respiratory infection
      • Check for nasal congestion/discharge
    • Neck: lymph nodes, any swelling
    • Chest wall & lungs:
      • Visual inspection for retractions, use of accessory muscles
      • Palpate chest for tenderness, expansion
      • Percuss the lung fields
      • Auscultate all lung fields systematically
    • Heart:
      • Auscultate for murmurs, rate, rhythm
      • Check for signs of cardiac stress
    • Abdomen:
      • Inspect, auscultate, palpate
      • Check for hepatomegaly
    • Extremities:
      • Check perfusion, clubbing, cyanosis
      • Assess muscle tone and reflexes

    Assessment Note:

    J.M. is an 18-month-old male presenting with 2-3 day history of worsening productive cough, fever, and respiratory distress. Physical exam notable for intercostal retractions, fine crackles on auscultation, and mild tachypnea. Environmental exposures include secondhand smoke and recent daycare attendance with exposure to sick children. Clinical presentation consistent with community-acquired pneumonia.

    Likely Diagnosis: Community-acquired pneumonia Supporting Evidence: Productive cough with purulent sputum, fever, respiratory distress, fine crackles, age-appropriate risk factors

    Jake Mason iHuman Plan:

    • Immediate Management:
      • Oxygen saturation monitoring
      • Supplemental oxygen if SpO2 < 92%
      • Elevate the head of the bed
      • Humidified oxygen therapy
    • Diagnostic Testing:
      • Chest X-ray to confirm diagnosis
      • Complete blood count with differential
      • Blood cultures if severely ill
      • Rapid viral panel (RSV, influenza)
      • Sputum culture (if obtainable)
    • Pharmacological Treatment:
      • Age-appropriate antibiotic therapy (amoxicillin first-line)
      • Fever management with acetaminophen or ibuprofen
      • Consider a bronchodilator trial if wheezing is present
    • Supportive Care:
      • Encourage fluid intake
      • Rest and activity as tolerated
      • Humidification
      • Close monitoring of respiratory status
    • Education and Follow-up:
      • Return precautions for parents
      • Follow-up in 24-48 hours
      • Complete the antibiotic course
      • Smoking cessation counseling for the household

    Jake Mason SOAP Note

    Jake Mason iHuman

    Patient: Jake Mason Subjective Data

    CC: 18-month-old male brought by father with “cough and difficulty breathing”

    HPI: Jake Mason is an 18-month-old male who presents to urgent care with a 2-3 day history of worsening cough and respiratory symptoms. The father reports that Jake initially had what seemed like a cold with a runny nose and low-grade fever, but over the past two days has developed a productive cough that is significantly worse at night. The cough produces yellow-colored sputum. Jake has had a decreased appetite and has been less active than usual. Father notes that Jake seems to be working harder to breathe and has been more irritable, especially at night. The child attends daycare where several children have been sick with similar symptoms. There is secondhand smoke exposure in the home from the father’s smoking.

    Medications: None currently. Acetaminophen as needed for fever.

    Allergies: No known drug allergies

    PMH: Full-term delivery, no complications. Up to date on vaccinations, including pneumococcal conjugate vaccine.

    Family History: No significant family history of respiratory or cardiac disease. Father smokes cigarettes.

    Social History: Lives with father and paternal grandmother. Attends daycare 4 days per week. Recently exposed to multiple sick children at daycare.

    Environmental: Secondhand smoke exposure from the father’s cigarette use inside the home.

    Objective Data

    ROS:

    • General: Decreased activity level, irritability, decreased appetite, fever
    • HEENT: Rhinorrhea with clear to yellow discharge, no ear pain reported
    • Respiratory: Productive cough worse at night, mild respiratory distress
    • Cardiovascular: No known heart problems
    • GI: Decreased appetite, normal bowel movements, adequate fluid intake
    • GU: Normal urination pattern
    • Neurologic: Alert but somewhat irritable, normal development for age

    Vital Signs:

    • Temperature: 101.2°F (38.4°C)
    • Heart Rate: 125 bpm
    • Respiratory Rate: 32 breaths/min
    • Blood Pressure: 95/60 mmHg
    • Oxygen Saturation: 94% on room air
    • Weight: 24 lbs (10.9 kg)

    Assessment

    General: 18-month-old male appears mildly ill, alert but somewhat irritable. Mild respiratory distress with increased work of breathing.

    Vital Signs: Febrile, mild tachypnea, oxygen saturation borderline low for age.

    HEENT: Nasal congestion with yellow rhinorrhea. Throat without erythema or exudate. Tympanic membranes are clear bilaterally.

    Respiratory: Mild intercostal retractions noted. Fine crackles were heard in the bilateral lower lung fields. No wheezing. Equal chest expansion.

    Cardiovascular: Regular rate and rhythm, no murmurs. Capillary refill < 3 seconds.

    Abdomen: Soft, non-tender, bowel sounds present. No hepatomegaly.

    Extremities: Warm, well-perfused. No clubbing or cyanosis.

    Skin: Warm and dry, appropriate color for ethnicity.

    Differential Diagnoses

    Community-Acquired Pneumonia: Most likely diagnosis given productive cough with purulent sputum, fever, fine crackles on auscultation, and mild respiratory distress. Age and daycare exposure are consistent risk factors.

    Viral Upper Respiratory Infection: Could present with cough and rhinorrhea, but is less likely to cause significant respiratory distress and fine crackles. Usually self-limiting.

    Bronchiolitis: Common in this age group, especially with RSV. However, typically presents with wheezing and more significant respiratory distress.

    Asthma Exacerbation: Could cause cough and respiratory symptoms, but is usually associated with wheezing and a family history. No previous episodes reported.

    Most Likely Diagnosis: Community-acquired pneumonia evidenced by productive cough with purulent sputum, fever, fine crackles on auscultation, mild respiratory distress, and appropriate epidemiologic risk factors.

    Complete Step-by-Step Guide to Writing the Jake Mason iHuman Case Study

    Step 1: Pre-Case Preparation and Pediatric Considerations

    Key Pediatric Factors to Remember:

    • Age-specific normal vital signs (18-month-old: HR 80-130, RR 20-30, BP varies)
    • Developmental considerations for assessment
    • Age-appropriate communication with the caregiver
    • Vaccination status relevance
    • Environmental exposure importance

    Initial Clinical Mindset: Approach with pediatric respiratory conditions as the primary consideration. Age makes viral and bacterial respiratory infections most likely, with pneumonia being a significant concern given symptom severity.

    Step 2: Conducting Pediatric History of Present Illness (HPI)

    Use the OLDCARTS method while considering pediatric-specific factors:

    Onset: When did symptoms start, and how did they progress

    Location: Where are the symptoms (chest, throat, nose)

    • Target response: Productive cough from chest, nasal congestion

    Duration: How long do coughing episodes last

    • Important detail: Persistent cough, worse at night, disrupting sleep

    Character: Description of cough quality and sputum

    • Critical descriptor: Productive cough with yellow sputum

    Aggravating factors: What makes symptoms worse

    • Essential findings: Night time, lying flat, activity

    Relieving factors: What provides relief

    • Key response: Sitting upright, rest, humidified air

    Timing: Pattern of symptoms

    • Important pattern: Progressive worsening, nocturnal exacerbation

    Severity: Impact on function

    • Pediatric consideration: Decreased activity, poor feeding, sleep disruption

    Step 3: Pediatric Review of Systems (ROS)

    General: Energy level, appetite changes, sleep disturbances, fever patterns

    Respiratory:

    • Work of breathing changes
    • Cough character and timing
    • Sputum production
    • Breathing difficulty with activity

    Cardiovascular:

    • Feeding tolerance (important in infants/toddlers)
    • Activity level changes
    • Color changes

    GI: Appetite changes, vomiting, feeding difficulties

    Infectious: Fever patterns, exposures, vaccination status

    Step 4: Environmental and Social History

    Daycare/School Exposures:

    • Recent sick contacts
    • Outbreak information
    • Vaccination compliance

    Home Environment:

    • Smoking exposure (critical risk factor)
    • Air quality factors
    • Household illness

    Developmental History:

    • Meeting milestones
    • Previous respiratory illnesses
    • Feeding and growth patterns

    Step 5: Pediatric Physical Examination Strategy

    Approach Considerations:

    • Examine the child on the parent’s lap if possible
    • Least invasive procedures first
    • Use distraction techniques
    • Age-appropriate equipment

    Respiratory Focus:

    • Observe the work of breathing before touching the child
    • Count the respiratory rate for a full minute
    • Look for retractions, nasal flaring, and head bobbing
    • Auscultate systematically with a pediatric stethoscope
    • Assess oxygen saturation

    Expected Findings:

    • Mild tachypnea (RR 28-35 for age)
    • Fine crackles in affected areas
    • Possible intercostal retractions
    • Fever
    • Oxygen saturation 92-94%

    Step 6: Developing Pediatric Differential Diagnoses

    Primary Considerations:

    Community-Acquired Pneumonia

    • Supporting evidence: Age, daycare exposure, productive cough, fever, crackles
    • Most common bacterial: Streptococcus pneumoniae

    Viral Respiratory Infection

    • Supporting evidence: Season, daycare exposure, gradual onset
    • Consider: RSV, rhinovirus, influenza

    Bronchiolitis

    • Supporting evidence: Age group, viral prodrome
    • Expected: Wheezing, more severe distress

    Step 7: Diagnostic Test Interpretation

    Expected Key Tests:

    • Chest X-ray: May show consolidation or infiltrates
    • CBC: Possible leukocytosis with bacterial infection
    • Rapid viral panel: Rule out RSV, influenza
    • Oxygen saturation: Monitor respiratory status
    • Blood cultures: If severely ill or hospitalized

    Step 8: Pediatric-Specific Diagnosis and Management

    Primary Diagnosis: Community-acquired pneumonia

    Justification:

    • Age-appropriate presentation
    • Classic symptom progression
    • Physical exam findings are consistent
    • Risk factors present (daycare, smoke exposure)

    Step 9: Comprehensive Pediatric Management Plan

    Immediate Assessment:

    • Severity stratification
    • Need for hospitalization vs outpatient management
    • Respiratory support requirements

    Pharmacological Management:

    • First-line antibiotic: Amoxicillin 90 mg/kg/day divided twice daily
    • Alternative: Amoxicillin-clavulanate if atypical bacteria are suspected
    • Fever management: Acetaminophen 15 mg/kg every 4-6 hours or ibuprofen 10 mg/kg every 6-8 hours

    Supportive Care:

    • Humidified air
    • Adequate hydration
    • Rest with activity as tolerated
    • Oxygen supplementation if SpO2 < 92%

    Monitoring:

    • Daily assessment for the first 2-3 days
    • Return precautions for worsening
    • Complete the antibiotic course

    Prevention:

    • Smoking cessation counseling for the family
    • Hand hygiene education
    • Vaccination compliance

    Step 10: Pediatric Documentation and Safety

    Key Safety Considerations:

    • Clear return precautions for parents
    • Signs of respiratory distress requiring immediate care
    • Medication dosing safety
    • Follow-up scheduling

    Parent Education Topics:

    • Expected course of illness
    • Medication administration
    • When to seek immediate care
    • Environmental modifications

    Jake Mason iHuman Case Summary

    Grading Criteria for Pediatric Cases:

    (1) History Taking (Major Points): Focus on age-appropriate questioning and caregiver interview skills. Essential questions include the onset and progression of symptoms, cough characteristics, fever patterns, changes in feeding and activity, exposure history (including daycare and smoking), and vaccination status. The rubric rewards students who ask about environmental exposures and developmental considerations specific to pediatric patients.

    (2) Physical Examination (High Weight): Pediatric-focused examination with age-appropriate techniques. Must-do components: vital signs with age-specific norms, respiratory assessment including work of breathing, auscultation technique for toddlers, and assessment of hydration status. Pro tip: The rubric awards points for observing the child before examination and using appropriate restraint/comfort techniques.

    (3) Differential Diagnosis (Critical for Scoring): Age-appropriate differentials with understanding of pediatric disease patterns. Expected differentials: community-acquired pneumonia, viral respiratory infection, bronchiolitis. Scoring secret: Understanding age-specific epidemiology and risk factors.

    (4) Final Diagnosis & MSAP: Must correctly identify pneumonia with supporting evidence and age-appropriate reasoning.

    (5) Management Plan (Heavily Weighted): Pediatric-specific treatment including weight-based medication dosing, supportive care measures, and family education. High-scoring responses include: appropriate antibiotic selection and dosing, symptom management, follow-up planning, and prevention strategies.

    (6) Family Communication: Demonstrate clear communication with caregivers, including return precautions and expectations for recovery.

    Jake Mason Clinical Summary Example

    Jake Mason iHuman

    Patient Summary – Jake Mason

    Situation: 18-month-old male presenting with 2-3 day history of productive cough, fever, and mild respiratory distress.

    Background: Healthy toddler with daycare exposure to ill children and household secondhand smoke exposure. Up-to-date on immunizations, including pneumococcal vaccine.

    Assessment: Physical examination notable for fever (101.2°F), mild tachypnea (RR 32), oxygen saturation 94%, fine crackles bilateral lower lobes, and mild intercostal retractions. No signs of severe respiratory distress.

    Primary Diagnosis: Community-acquired pneumonia, mild severity, suitable for outpatient management.

    Recommendation:

    • Amoxicillin 90 mg/kg/day divided BID x 10 days
    • Supportive care with humidification and adequate hydration
    • Acetaminophen for fever management
    • Close follow-up in 24-48 hours
    • Return the precautions provided to the father
    • Smoking cessation counseling for household members

    Patient/Family Education: Explained pneumonia in age-appropriate terms for the caregiver, emphasized the importance of medication compliance, provided clear return precautions for worsening respiratory distress, and discussed environmental modifications to reduce future risk.

    Key Success Factors for Jake Mason Case

    Pediatric-Specific Considerations:

    • Understand normal vital signs for an 18-month-old
    • Recognize age-appropriate disease patterns
    • Use proper examination techniques for toddlers
    • Calculate weight-based medication dosing
    • Provide appropriate caregiver education

    Clinical Reasoning Focus:

    • Systematic approach to pediatric respiratory distress
    • Integration of environmental and social factors
    • Age-appropriate differential diagnosis
    • Evidence-based treatment decisions
    • Family-centered care approach

    Common Pitfalls to Avoid:

    • Using adult normal values for vital signs
    • Inadequate assessment of work of breathing
    • Missing environmental risk factors
    • Inappropriate antibiotic dosing
    • Insufficient parent education

    Frequently Asked Questions

    Q1: What is the most likely diagnosis for Jake Mason’s respiratory symptoms?

    Community-acquired pneumonia is the most likely diagnosis based on his productive cough with purulent sputum, fever, fine crackles on examination, and mild respiratory distress. The combination of daycare exposure and secondhand smoke creates an appropriate risk factor for bacterial pneumonia in this age group.

    Q2: What are the critical physical exam components for scoring well in pediatric respiratory cases?

    Essential components include observing work of breathing before touching the child, obtaining accurate vital signs with age-appropriate norms, systematic respiratory auscultation, assessment for retractions and accessory muscle use, and evaluation of hydration status. Don’t forget to assess oxygen saturation, the overall appearance of illness.

    Q3: How do I determine if this case requires hospitalization vs outpatient management?

    Outpatient management is appropriate for this case based on: age > 3 months, ability to maintain oral intake, oxygen saturation > 92%, mild respiratory distress without severe retractions, and reliable caregivers for follow-up. Hospitalization would be considered for severe respiratory distress, poor oral intake, or social concerns.

    Q4: What is the appropriate antibiotic choice and dosing for pediatric pneumonia?

    First-line treatment is amoxicillin 90 mg/kg/day divided twice daily for 10 days. This high-dose amoxicillin covers the most common bacterial pathogen (Streptococcus pneumoniae), including some resistant strains. Alternative options include amoxicillin-clavulanate for broader coverage or macrolides if atypical bacteria are suspected.

  • Florence Blackman iHuman Case Study

    Florence Blackman is a 66-year-old female presenting with intermittent squeezing chest pain that occurs with exertion and radiates to her left arm.

    In this comprehensive guide, we’ll walk you through how to approach her case, from initial history-taking through physical examination to the final diagnosis of stable angina and coronary artery disease. You’ll learn the key clinical reasoning steps, what the iHuman grading rubric expects, and a complete step-by-step solution to help you confidently navigate this cardiovascular case simulation.

    Florence Blackman Ihuman

    Florence Blackman Ihuman Case Overview (Doorway Information)

    Patient Overview: Florence Blackman is a 66-year-old Caucasian female presenting with a chief complaint of “intermittent squeezing chest pain” that has been occurring over the past 2 weeks. She describes experiencing exertional mid-chest pain with a “squeezing feeling” that radiates to her left arm, particularly when skiing cross-country in cold weather. The pain is accompanied by dyspnea on exertion and is consistently relieved by rest.

    Key Background Information:

    • Age/Gender: 66-year-old female
    • Chief Complaint: Intermittent squeezing chest pain
    • Duration: 2 weeks of symptoms
    • Pain Characteristics: Exertional, radiates to left arm, relieved by rest, worse in cold
    • Associated Symptoms: Dyspnea on exertion
    • Significant History: Hypertension, hyperlipidemia, former smoker (quit 15 years ago), family history of heart disease
    • Current Medications: Hydrochlorothiazide (HCTZ) 12.5mg daily
    • Occupation: Marketing executive with demanding work schedule
    • Lifestyle: Active with regular aerobic exercise, but reports high stress levels

    The patient appears alert and oriented, currently pain-free at presentation, with stable vital signs. Her presentation is classic for cardiac-related chest pain, making this an excellent case for learning systematic cardiovascular assessment and differential diagnosis skills.

    Florence Blackman (66 y/o female) – Chest Pain Assessment

    • CC: Intermittent squeezing chest pain
      • MSAP: Exertional “squeezing” mid-chest pain radiating to left arm, relieved by
      rest, worse with cold
      • Associated dyspnea on exertion
      • History: HLD, HTN, previous smoker, family hx of heart disease
      • Stressful work
    • History Questions:
      − How can I help you today?
      − Any other symptoms we should discuss?
      − Do you have any allergies?
      − Are you taking any OTC or herbal medications?
      − Any new or recent changes in medications?
      − What does the pain / discomfort in your chest feel like? (squeezing, pressure,
      crushing, burning, stabbing, aching, tingling, suffocating)
      − How severe (scale 1−10) is the pain in your chest?
      − Does anything make the pain in your chest better or worse?
      − What are the events surrounding the start of your chest pain?
      − Is there a pattern to your chest pain?
      − Have you had any trauma to your chest?
      − Does the pain in your chest radiate someplace else? Where?
      − Do you have unusual heartbeats (palpitations)?
      − Does the pain get worse with breathing?
      − Does your pain awaken you from your sleep?
      − Is your pain affected by what, when, or how much you eat?
      − Do you presently have heartburn, a food or acid taste in your mouth?
      − Do you drink alcohol? If so, what do you drink and how many drinks per day?
      − Do you have any of the following problems: fatigue, difficulty sleeping,
      unintentional weight loss or gain, fevers, night sweats?
      − Do you experience: SOB, wheezing, difÏculty catching breath, chronic cough,
      sputum production?
      − Does anything make your shortness of breath better or worse?
      − How long does your SOB last?
      − Do you have any of the following: heat or cold intolerance, increased thirst,
      increased sweating, frequent urination, change in appetite?
      − Do you have any of the following: dizziness, fainting, spinning room, seizures,
      weakness, numbness, tingling, tremor?
      − Do you have problems with: N/V, constipation, diarrhea, coffee grounds in your
      vomit, dark tarry stool, bright red blood in your BM, early satiety, bloating?
      − How is your overall health?
      − Tell me about your work.
      − Tell me about daily exercise or sports that you play.

    Physical Exam:

    • − Vitals: pulse, BP, respirations
    • − Examine skin
    • − Neck: measure JVP (jugular venous pressure)
    • − Neck: auscultate carotid arteries
    • − Chest wall & lungs:
    • o Visual inspection of anterior & posterior chest
    • o Palpate anterior & posterior chest
    • o Auscultate lungs
    • − Heart:
    • o Palpate for PMI (Point of Maximal Impact)
    • o Auscultate heart
    • − Abdomen:
    • o Auscultate abdominal/femoral arteries
    • o Palpate abdomen
    • − Extremities: Visual inspection of extremities


    Assessment note:

    F.B. is a 66 y/o Caucasian female presenting with 2−week h/o new onset, intermittent, stable chest pain which radiates to the L arm, occurs with SOB, is worse with cold temperatures and exertion, and improved by rest. On physical exam she is pain free with stable vital signs. PMH risk factors include: distant history of smoking (5 pack/years), a history of HTN, high cholesterol, and a family history of coronaryvascular disease

    Stress test: 2−mm ST segment depression in inferior leads, 2, 3, and aVF and V3−6

    Diagnosis: Coronary artery disease: stable angina

    Plan:

    • − Determine need for coronary angiography based on stress test results and ECHO.Her Duke score of 10.5 is slightly above moderate risk, and arguments could be both a trial at medication intervention since the pt needs improvement on both HTN and HLD
    • Augment management of preexisting HTN and HLD with a BB (metoprolol 25 mg XR daily); a statin (atorvastatin 40 mg daily); and ASA 81 mg daily
    • Continue use of HCTZ 25 mg daily
    • Encourage lifestyle modification:
    • Decrease the intensity of aerobic workouts for the next 3 months
    • D/c alcohol for the next 2 months as I start a statin
    • f/u in 3−4 weeks

    Florence Blackman SOAP Note

    Patient: Florence Blackman Subjective Data

    CC: 66-year-old female presents with “intermittent squeezing chest pain”
    HPI: 66-year-old female presents today with complaints of exertional mid-chest pain that has been occurring for the past 2 weeks. The patient describes the pain as a “squeezing feeling” that radiates to her left arm while she was cross country skiing in extreme cold weather. The patient states that the pain worsens in cold weather and is accompanied by dyspnea that is only alleviated with rest. The patient reports the chest pain to be moderate and reports a 6/10 on a pain scale when episodes occur. The patient reports a history of hypertension and hypercholesterolemia and reports a family history of heart disease. Upon physical examination, the patient is slightly overweight with a BMI of 25.5 but has a normal physical examination.
    Medications: Hydrochlorothiazide (HCTZ) 12.5mg daily
    Allergies: (medication, environmental, food) The patient denies any medication, environmental or food allergies
    PMH: Hypertension and hypercholesterolemia. Denies other chronic
    medical conditions.
    LNMP/OB History (if indicated): The patient has no living children.
    PSH: Denies any surgical or dental procedures.
    Sexual History (if indicated): Deferred for this exam.
    1/14/21 dws
    Hospitalizations: None.
    Health Maintenance: Reports going to primary care provider every 4 months to monitor her cholesterol and blood pressure.
    Immunizations: Immunizations are up to date. Completed all childhood vaccines.
    Family History: Paternal history of stroke. Maternal history of heart disease. Her sister had open heart surgery at age 58.

    Substances (Tobacco, alcohol, illicit drugs, caffeine):The patient denies illicit drug use. The patient was a history smoking cigarettes (5 pack a year) and quit 15 years ago. Reports mild caffeine intake and reports
    drinking 1-2 glasses of wine a day. Denies history of alcohol abuse or excessive alcohol consumption.
    Home environment: The patient lives alone in a loft and reports a safe home environment.
    Employment type: Currently a marketing executive with her own firm. Reports work hours and “long and demanding.”
    Diet: Eats fast food and goes out to eat at restaurants regularly.
    Sleep: Sleeps adequately and denies chest pain or dyspnea during sleep
    Exercise: Active lifestyle. Performs aerobic exercises three times a week
    Safety: Reports feeling safe at home. Denies history of physical or verbal abuse.

    Objective Data

    ROS: (Perform an appropriate ROS based on the C/C and HPI; documented in i-Human assignment; performed in final focused exam
    General: Reports usual state of good health in addition to hypertension which is controlled with medication and exercise. Denies fever, chills, recent weight gain or loss, weakness, or fatigue. Eye contact is appropriate with clear speech. Reports the need to lose weight due to being slightly overweight, evidenced by a BMI of 25.5. Reports her weight has stated consistent.
    Skin, Hair and Nails: Denies any recent lesions, rashes, changes in texture, or moles.
    HEENT: Denies headaches, blurry vision, or vision changes. Denies ear problems or ear pain. Denies sinus problems or pain. Denies nasal congestion, cough, runny nose, sore throat, or sputum production. Denies
    difficulty swallowing, pain in the jaw or neck.
    NECK: Denies pain or stiffness of the neck. Denies swollen glands/lumps in neck.
    Thorax and Lungs: Reports dyspnea with chest pain that is alleviated with rest. Reports worsening dyspnea and chest pain with exertion. Denies history of lung disease, allergies, or asthma. Denies wheezing, trouble catching her breath. Denies orthopnea, or paroxysmal nocturnal dyspnea.
    Cardiovascular: Reports a history of mild hypertension that is managedwith medication (HCTZ 12.5mg daily) and hypercholesterolemia. Reports “squeezing” chest pain with dyspnea during exertion that is alleviated with rest. Reports the chest pain lasts a few minutes and has been occurring intermittently for the past two weeks, specifically during cross-country skiing. Reports pain is moderate and rates it a 6/10 on a pain scale. Reports chest pain is sometimes precipitated by exercise. The patient denies decreased exercise tolerance. Denies syncope, palpitations, dizziness, or pressure with or without exertion or with getting angry.
    Peripheral Vascular: Denies upper and lower extremity edema, coldness,
    leg cramps, skin ulcers or varicose veins.
    Abdomen: Denies nausea, vomiting, constipation, diarrhea, coffee grounds in vomit, dark tarry stools, bright red blood in bowel movements, bloating or early satiety.
    Genitourinary: This exam was deferred.
    Metabolic/Hematologic: Denies thyroid disease, heat/cold intolerance, excessive hunger, thirst, or history of diabetes. Denies history of anemia.
    Psychiatric: Denies history of nervousness, depression, lack of interest, sadness, memory loss, mood changes, or hearing voices that are not there. Denies difficulty falling or staying asleep. Denies ideas or self-harm or suicidal ideation.
    Musculoskeletal: Reports chest pain that radiates to left arm during exertion. Reports full range of motion in upper and lower extremities. Denies pain in other extremities. Denies any weakness or muscle wasting
    of the upper or lower extremities. Denies difficulty walking or performing ADLs without assistance.
    Neurologic: Denies history of stroke, syncope, seizures, or frequent/incapacitating headaches. Denies tremors, decreased alertness, or loss of sensation.
    Vital Signs:
    Temperature: 98.5 F, Pulse: 74, BP: 132/90, Respirations: 18
    SpO2: 96%

    Assessment

    General: Slightly overweight middle-aged female, appears stated age, alert, and oriented x 4. No grimacing, respiratory or emotional distress noted. Skin, Hair and Nails: Skin is warm and dry with no lesions noted. Thickness and distribution pattern is typical for the patients’ gender and age. Capillary refill is less than 3 seconds in fingers and toes.
    HEENT: The head is normocephalic and atraumatic. The scalp is nontender and has no visible scaliness, edema, masses, lumps, deformities, scars, rashes, nevi, or other lesions. There is no eyelid ptosis, erythema or swelling noted. Conjunctiva is pink with no discharge. Sclerae is anicteric. There is no edema, redness or tenderness noted on the orbital area. Both pupils are brisk and reactive to light. Normal appearing external ears. No deformities, or edema noted. No discharge noted. Normal appearing external auditory canals. Tympanic membrane translucent, non-injected, and pinkish gray in color. No scarring or discharge noted. Oropharynx not injected. Clear mucosa. Tonsils without exudate. Tongue pink in color and symmetrical. No swelling or ulcerations. Intact Gag reflex. No hoarseness noted. No unusual or foul swelling odor of the breath.
    NECK: No lesions, or edema noted. No stiffness or pain noted. Full range of motion of the neck noted. Thyroid moves with swallowing. No pathologically enlarged lymph nodes noted in the cervical, supraclavicular, or axillary chains.
    Thorax and Lungs: Anterior and posterior chest: Thorax is atraumatic, without deformity. Normal symmetrical respiratory effort with excursion. No costochondral point tenderness noted. No evident rib fractures. No vertebral tenderness. The anterior lung fields are resonant. The rest of the lung fields are resonant. All lungs fields are clear to auscultation. No wheezing, crackles or stridor noted. Symmetrical expansion and unlabored breathing are also noted.
    Cardiovascular: Chest is symmetric, with no scars noted. No cardiac heaves or lifts. No edema noted. PMI is nondisplaced and noted at the midclavicular line, in fifth intercostal space. Normal Jugular venous
    pressure. Normal heart rate and rhythm, normal S1 and S2 without murmur, click, gallop, or rub. No splitting of the heart sounds heard.
    Peripheral Vascular: Extremities are warm and dry. Carotid pulses 2+ bilaterally. Radial pulses 2+ bilaterally. No peripheral edema, varicosities, or ulcerations noted.
    Abdomen: Abdomen is soft to palpation. Nontender to upper quadrant and epigastric palpation. The patient’s symptoms cannot be produced with applied epigastric pressure. Bowel sounds normoactive in all 4 quadrants. No masses or bruits noted. Rectal examination was deferred.
    Genitourinary: Deferred for this exam.
    Psychiatric: Affect and speech is clear and appropriate. Calm emotional state. Concentration, activity level and attention are appropriate. No increased activity or agitation noted during examination.
    Musculoskeletal: No asymmetry or deformity of the back noted. No tenderness or spasm noted of the paraspinal muscles. Steady gait with a normal posture noted. Test strength is 5/5 bilaterally. Full range of motion of the upper and lower extremities. No pain noted during ROM.
    Neurologic: Alert, oriented to person, place, time, and situation. Pupils equal to light and accommodation. Facial movements are symmetrical. Head turning and shoulder shrug are intact to resistance. Tongue is midline with normal movements and no atrophy. Speech is fluent and clear. Deep tendon reflexes of the triceps, biceps, brachioradialis, and patella have a brisk response (2+).

    Differential Diagnoses


    Myocardial infarction: The patient reports with intermittent chest pain with exertion and dyspnea that radiates to the left arm for the past two weeks. The patient reports that when the chest pain occurs, the pain is moderate and reports a 6/10 on a pain scale. The recurrent chest pain may imply it is not an MI, since most MI’s present with constant chest pain but the possibility of an MI may still need to be ruled out.
    Stable Angina: The patient reports with intermittent chest pain with exertion and dyspnea that radiates to the left arm for the past two weeks. The patient reports the chest pain lasts a few minutes and is alleviated with rest. Chest pain with exertion is a common finding with stable angina, especially when episodes last a few minutes.
    Unstable Angina: The patient reports with intermittent chest pain with exertion and dyspnea that radiates to the left arm for the past two weeks. The patient reports the chest pain lasts a few minutes and is alleviated with rest. Unstable angina occurs without exertion, and during sleeping or resting. Since the patient reports alleviation with rest, it may not be unstable angina, but still needs to be ruled out.
    Anxiety attack: The patient reports with intermittent chest pain with exertion and dyspnea that radiates to the left arm for the past two weeks. The patient reports the chest pain lasts a few minutes and is alleviated with rest. The patient states she has a high-stress career and enjoys cross country skiing to alleviate the stress of her job. However, anxiety attacks can occur during exertion, along with dyspnea and chest pain. It is unlikely that the patient has anxiety attacks that causes intermittent chest pain and dyspnea,
    but it may also be ruled out.
    Most Likely Diagnosis: Stable Angina evidenced by intermittent chest pain with exertion and dyspnea that radiates to the left arm that lasts a few minutes and is alleviated with rest. ECG was normal sinus rhythm. Troponin levels were within normal limits. Chest Xray was normal. The patient was also diagnosed with Coronary artery disease. Cholesterol was high, at 245mg/dl. LDL was moderately elevated at 140mg/dl and Triglycerides were also elevated at 175 mg/dl.

    Plan

    Health Promotion: (appropriate screening, disease prevention, and health promotion according to the patient’s age, gender, and identified risk factors…not diagnosis specific)
    ✓ Wellness Check- Continue to get lipid panel screening every 4 months to maintain and lower Cholesterol, Triglycerides, and LDL.
    ✓ Lose weight to lower cholesterol and blood pressure.
    ✓ Refrain or reduce intake of salty, fast foods, or restaurant meals. Try to cook or prepare healthy meals to lose weight and reduce sodium intake.
    Screening
    ✓ Diabetes screening (women with HTN, CAD, overweight and the over age of 45 have increased risk for DM)
    ✓ Cancer screening- Cervical cancer screening (Pap smears every 3 years) Breast cancer (yearly mammogram), Immunizations
    ✓ Seasonal Flu vaccine
    ✓ Covid-19 vaccine

    Florence Blackman Ihuman Soap Note
    Florence Blackman Ihuman Soap Note

    Complete Step-by-Step Guide to Writing the Florence Blackman iHuman Case Study

    Completing the Florence Blackman iHuman case requires a systematic approach that mirrors real clinical practice. This comprehensive guide will walk you through each section of the simulation, providing specific strategies and key points to ensure you achieve the required 70% score.

    Step 1: Pre-Case Preparation and Initial Approach

    Before diving into the case, take a moment to review the doorway information and formulate your initial clinical approach.

    Key Information to Note:

    • 66-year-old female with “intermittent squeezing chest pain”
    • 2-week duration of symptoms
    • Consider immediate cardiac risk factors: age, gender, symptom description

    Initial Clinical Mindset: Approach this case with cardiovascular conditions as your primary consideration. The age, gender, and symptom description immediately suggest potential coronary artery disease, making this a high-priority assessment requiring systematic evaluation.

    Step 2: Conducting the History of Present Illness (HPI)

    The HPI is crucial for establishing the foundation of your diagnosis. Use the OLDCARTS method systematically:

    Onset: Ask about when the chest pain started and what she was doing

    • Key points to elicit: Started 2 weeks ago during cross-country skiing in cold weather

    Location: Determine the exact location and radiation pattern

    • Target response: Mid-chest pain radiating to left arm

    Duration: How long do episodes last

    • Important detail: Episodes last 5-10 minutes, then resolve

    Character: Detailed description of pain quality

    • Critical descriptor: “Squeezing” sensation (classic for angina)

    Aggravating factors: What makes it worse

    • Essential findings: Cold weather, physical exertion/exercise

    Relieving factors: What provides relief

    • Key response: Rest consistently relieves symptoms

    Timing/Treatment: Pattern and current treatments

    • Important pattern: Predictable with exertion, initially helped by reducing activity intensity

    Severity: Pain scale rating

    • Typical response: 6-7/10 during episodes

    Associated Symptoms:

    • Ask specifically about: dyspnea on exertion, palpitations, nausea, diaphoresis
    • Key finding: Shortness of breath accompanying chest pain

    Step 3: Review of Systems (ROS)

    Conduct a thorough but focused ROS, paying special attention to cardiovascular and related systems:

    Cardiovascular:

    • Chest pain/pressure (already covered in HPI)
    • Palpitations, irregular heartbeats
    • Exercise tolerance changes
    • Syncope or near-syncope
    • Orthopnea, paroxysmal nocturnal dyspnea

    Respiratory:

    • Shortness of breath patterns
    • Cough, sputum production
    • Wheezing

    General:

    • Fatigue levels, weight changes
    • Night sweats, fevers

    Gastrointestinal:

    • Rule out GERD symptoms that could mimic cardiac pain
    • Nausea and vomiting during episodes

    Step 4: Past Medical History, Social History, and Family History

    Past Medical History:

    • Hypertension (currently managed with HCTZ)
    • Hyperlipidemia
    • Previous smoking history (5 pack-years, quit 15 years ago)
    • Previous hospitalizations, surgeries

    Family History:

    • Critical finding: Strong family history of heart disease
    • Maternal history of heart disease, sister with open heart surgery at age 58
    • Paternal history of stroke

    Social History:

    • Occupation: Marketing executive with a demanding schedule
    • Exercise habits: Regular aerobic exercise 3x/week
    • Alcohol: 1-2 glasses of wine daily
    • Tobacco: Former smoker (significant risk factor)
    • Diet: Reports frequent fast food and restaurant meals

    Step 5: Physical Examination Strategy

    Perform a comprehensive cardiovascular-focused physical exam:

    Vital Signs:

    • Expected findings: Mild hypertension (132/90), normal other vitals
    • Note: Patient should be pain-free at rest during exam

    Cardiovascular Examination:

    1. Inspection: Look for visible cardiac impulses, chest wall abnormalities
    2. Palpation:
      • Point of Maximal Impulse (PMI) – should be non-displaced
      • Check for heaves, lifts, thrills
    3. Auscultation:
      • All four cardiac areas
      • Listen for murmurs, gallops, rubs
      • Expected: Normal S1, S2 without abnormal sounds

    Additional Key Exams:

    • Jugular Venous Pressure (JVP): Assess for elevated pressure
    • Carotid Arteries: Auscultate for bruits
    • Lung Examination: Rule out heart failure signs
    • Peripheral Pulses: Check radial, dorsalis pedis pulses
    • Extremities: Look for edema, clubbing, cyanosis

    Step 6: Developing Differential Diagnoses

    Propose at least 3-4 appropriate differentials with rationales:

    Primary Consideration: Stable Angina

    • Supporting evidence: Predictable exertional pattern, relief with rest, classic radiation, risk factors

    Secondary Considerations:

    1. Unstable Angina
      • Rationale to exclude: Symptoms are predictable and consistently relieved by rest
    2. Myocardial Infarction
      • Rationale to consider: New onset chest pain with cardiac risk factors
      • Rationale to exclude: Intermittent nature, consistent relief with rest
    3. Atypical Chest Pain/Anxiety
      • Rationale: High-stress occupation could contribute
      • Less likely: Classic cardiac symptoms and significant risk factors

    Step 7: Diagnostic Test Interpretation

    Interpret provided test results to support your diagnosis:

    Expected Key Findings:

    • ECG: May show signs of ischemia during stress testing
    • Stress Test: 2-mm ST depression in inferior and lateral leads
    • Lipid Panel: Elevated cholesterol (245 mg/dl), LDL (140 mg/dl)
    • Troponins: Normal (rules out acute MI)
    • Chest X-ray: Normal cardiac silhouette

    Clinical Correlation: Use test results to support a stable angina diagnosis and rule out acute coronary syndrome.

    Step 8: Final Diagnosis and Most Significant Active Problem (MSAP)

    Primary Diagnosis: Stable Angina Pectoris secondary to Coronary Artery Disease

    Justification:

    • Classic exertional chest pain with a predictable pattern
    • Relief with rest
    • Radiation to left arm
    • Multiple cardiac risk factors
    • Stress test evidence of exercise-induced ischemia

    MSAP Selection: Choose “Stable Angina” or “Coronary Artery Disease” as your Most Significant Active Problem, as this represents the primary condition requiring immediate management.

    Step 9: Comprehensive Management Plan

    Develop a multi-faceted treatment approach:

    Immediate Management:

    1. Risk Stratification: Duke Treadmill Score calculation
    2. Consider cardiac catheterization based on stress test results

    Pharmacological Interventions:

    1. Antiplatelet Therapy: Aspirin 81mg daily
    2. Beta-blocker: Metoprolol XR 25mg daily for rate control and anti-ischemic effect
    3. Statin Therapy: Atorvastatin 40mg daily for cholesterol management
    4. Continue HCTZ for blood pressure control

    Lifestyle Modifications:

    1. Dietary counseling: Reduce sodium, saturated fats
    2. Exercise modification: Temporarily reduce intensity for 3 months
    3. Stress management: Address work-related stress
    4. Smoking cessation maintenance: Continue abstinence

    Follow-up Plan:

    • Return visit in 3-4 weeks to assess symptom improvement
    • Monitor medication tolerance and effectiveness
    • Consider a cardiology referral if symptoms persist

    Step 10: Documentation and Submission Tips

    Writing Your Summary:

    • Create a concise 350-word summary explaining your clinical reasoning
    • Include how you arrived at the problem list
    • Cite specific assessment findings and lab correlations
    • Use professional medical terminology

    Key Documentation Elements:

    1. Assessment Statement: Brief patient summary with key findings
    2. Clinical Reasoning: Explain diagnostic thought process
    3. Evidence Correlation: Link physical findings to test results
    4. Management Rationale: Justify treatment choices

    Final Submission Checklist:

    • ✓ Complete history with OLDCARTS method
    • ✓ Comprehensive cardiovascular physical exam
    • ✓ Appropriate differential diagnoses with rationales
    • ✓ Correct final diagnosis and MSAP
    • ✓ Evidence-based management plan
    • ✓ Professional documentation with proper citations

    Florence Blackman Human Case Summary

    Grading Criteria: The Florence Blackman iHuman case will evaluate you across several critical domains to ensure comprehensive cardiovascular assessment skills. Here’s what you need to focus on to maximize your score:

    (1) History Taking (Major Points): You must ask targeted questions about chest pain characteristics to get full credit. Essential questions include: pain quality (squeezing/pressure), radiation pattern, triggers (exertion/cold), alleviating factors (rest), associated symptoms (dyspnea), and timing/duration. Don’t miss asking about: cardiac risk factors (smoking history, family history, hypertension, hyperlipidemia), medication compliance, and lifestyle factors. The rubric specifically rewards students who ask about pain severity using a 1-10 scale and relationship to physical activity.

    (2) Physical Examination (High Weight): Focus your exam on cardiovascular and respiratory systems. Must-do components: vital signs (noting elevated BP), cardiac auscultation for murmurs/gallops, lung auscultation, jugular venous pressure assessment, and peripheral pulse examination. Pro tip: The rubric awards points for checking Point of Maximal Impulse (PMI) and examining carotid arteries – many students forget these key cardiac exam elements.

    (3) Differential Diagnosis (Critical for Scoring): You need to propose at least 3 appropriate differentials with brief rationales. Expected differentials include: stable angina, unstable angina, myocardial infarction, and potentially anxiety/panic disorder. Scoring secret: The rubric rewards students who can distinguish between stable and unstable angina based on symptom patterns and triggers.

    (4) Final Diagnosis & MSAP: You must correctly identify stable angina secondary to coronary artery disease as your Most Significant Active Problem (MSAP). Justification is key – cite the exertional nature, radiation pattern, and relief with rest as supporting evidence.

    (5) Management Plan (Heavily Weighted): The rubric expects comprehensive management including: cardiac stress testing, medication optimization (beta-blockers, statins, aspirin), lifestyle modifications, and appropriate follow-up timing. High-scoring responses mention: Duke Treadmill Score interpretation and the need for possible cardiac catheterization based on stress test results.

    (6) Patient Communication: Demonstrate empathy and clear explanation of the condition. Bonus points for: discussing lifestyle modifications specifically (diet changes, exercise modifications, stress management) and explaining warning signs that require immediate medical attention.

    Example of a High-Scoring Clinical Summary

    Florence Blackman Ihuman

    Here’s how a top-performing student might document this case:

    Patient Summary – Florence Blackman

    Situation: 66-year-old female presenting with 2-week history of exertional chest pain with classic anginal features.

    Background: Significant cardiac risk factors including hypertension, hyperlipidemia, former tobacco use (5 pack-years), and strong family history of coronary disease. Currently on suboptimal antihypertensive therapy (HCTZ monotherapy with BP 132/90).

    Assessment: Physical examination notable for stable vital signs with mild hypertension. Cardiac exam reveals normal heart sounds without murmurs. Stress testing demonstrated 2-mm ST depression in inferior and lateral leads, consistent with exercise-induced ischemia. Primary Diagnosis: Stable angina pectoris secondary to coronary artery disease.

    Recommendation:

    • Initiate dual antiplatelet therapy (ASA 81mg daily)
    • Add beta-blocker (metoprolol XR 25mg daily) for rate control and anti-ischemic effect
    • Optimize lipid management (atorvastatin 40mg daily)
    • Consider cardiac catheterization based on Duke Treadmill Score of 10.5 (moderate-high risk)
    • Lifestyle counseling: dietary modifications, temporary exercise limitation, smoking cessation maintenance
    • Follow-up in 3-4 weeks to assess symptom improvement and medication tolerance

    Patient Education Provided: Explained stable angina pathophysiology, importance of medication compliance, activity modification during treatment initiation, and clear instructions to seek immediate care for rest pain or prolonged symptoms exceeding 10 minutes.

    Conclusion

    By following this comprehensive approach to the Florence Blackman case, you’ll demonstrate the clinical reasoning skills that iHuman evaluates. Remember, success in cardiovascular cases requires systematic thinking: gather detailed history about pain characteristics, perform focused but thorough physical examination, consider appropriate differentials, and develop evidence-based management plans. The key is treating each iHuman simulation as you would a real patient encounter – be thorough, think critically, and always prioritize patient safety. With this guide, you’re well-prepared to excel in this challenging but rewarding case simulation.

    Frequently Asked Questions

    Q1: What is the correct diagnosis for Florence Blackman’s chest pain?

    A: Florence Blackman‘s primary diagnosis is stable angina secondary to coronary artery disease. The key distinguishing features that point to stable angina include the predictable pattern of exertional chest pain that consistently resolves with rest, the classic “squeezing” quality with radiation to the left arm, and the reproducible triggers (cold weather and physical activity). Students often struggle between stable and unstable angina, but remember that stable angina has a predictable pattern and is relieved by rest, whereas unstable angina occurs at rest or with minimal exertion and represents a medical emergency.

    Q2: What are the critical physical exam components I need to perform to score well?

    A: Essential physical exam elements include measuring vital signs (noting elevated BP), assessing jugular venous pressure (JVP), auscultating carotid arteries, performing comprehensive cardiac auscultation including palpating for Point of Maximal Impulse (PMI), and conducting thorough lung examination. Many students miss points by skipping the JVP assessment and carotid artery examination, which are crucial for evaluating cardiovascular status. Don’t forget to examine the extremities for peripheral circulation and check for any signs of heart failure such as edema.

    Q3: How do I pass the Florence Blackman case and meet the 70% requirement?

    A: You must score a cumulative 70% on the iHuman assessments to successfully complete the required lab component. To achieve this score, focus on thorough history-taking using the OLDCARTS method for symptom analysis, complete all recommended physical exam components, propose appropriate differential diagnoses (including stable angina, unstable angina, and myocardial infarction), and develop a comprehensive management plan that includes both pharmacological interventions and lifestyle modifications. The key is being systematic and not rushing through any section.

    Q4: What management interventions should I include in my treatment plan?

    A: The comprehensive management plan should address both immediate stabilization and long-term cardiovascular risk reduction. Include cardiac stress testing to evaluate ischemia, optimize existing medications (consider upgrading from HCTZ monotherapy to combination therapy), initiate cardioprotective medications (aspirin, beta-blockers like metoprolol, and statins for cholesterol management), and provide lifestyle counseling regarding diet, exercise modification during treatment initiation, and stress management. Students often forget to address the need for follow-up care and patient education about warning signs that require immediate medical attention, which are important components for comprehensive care and can impact your overall score.

  • How to Create an Abstract Poster Presentation with Example

    How to Create an Abstract Poster Presentation with Example

    How to Create an Abstract Poster Presentation with Example and Tips

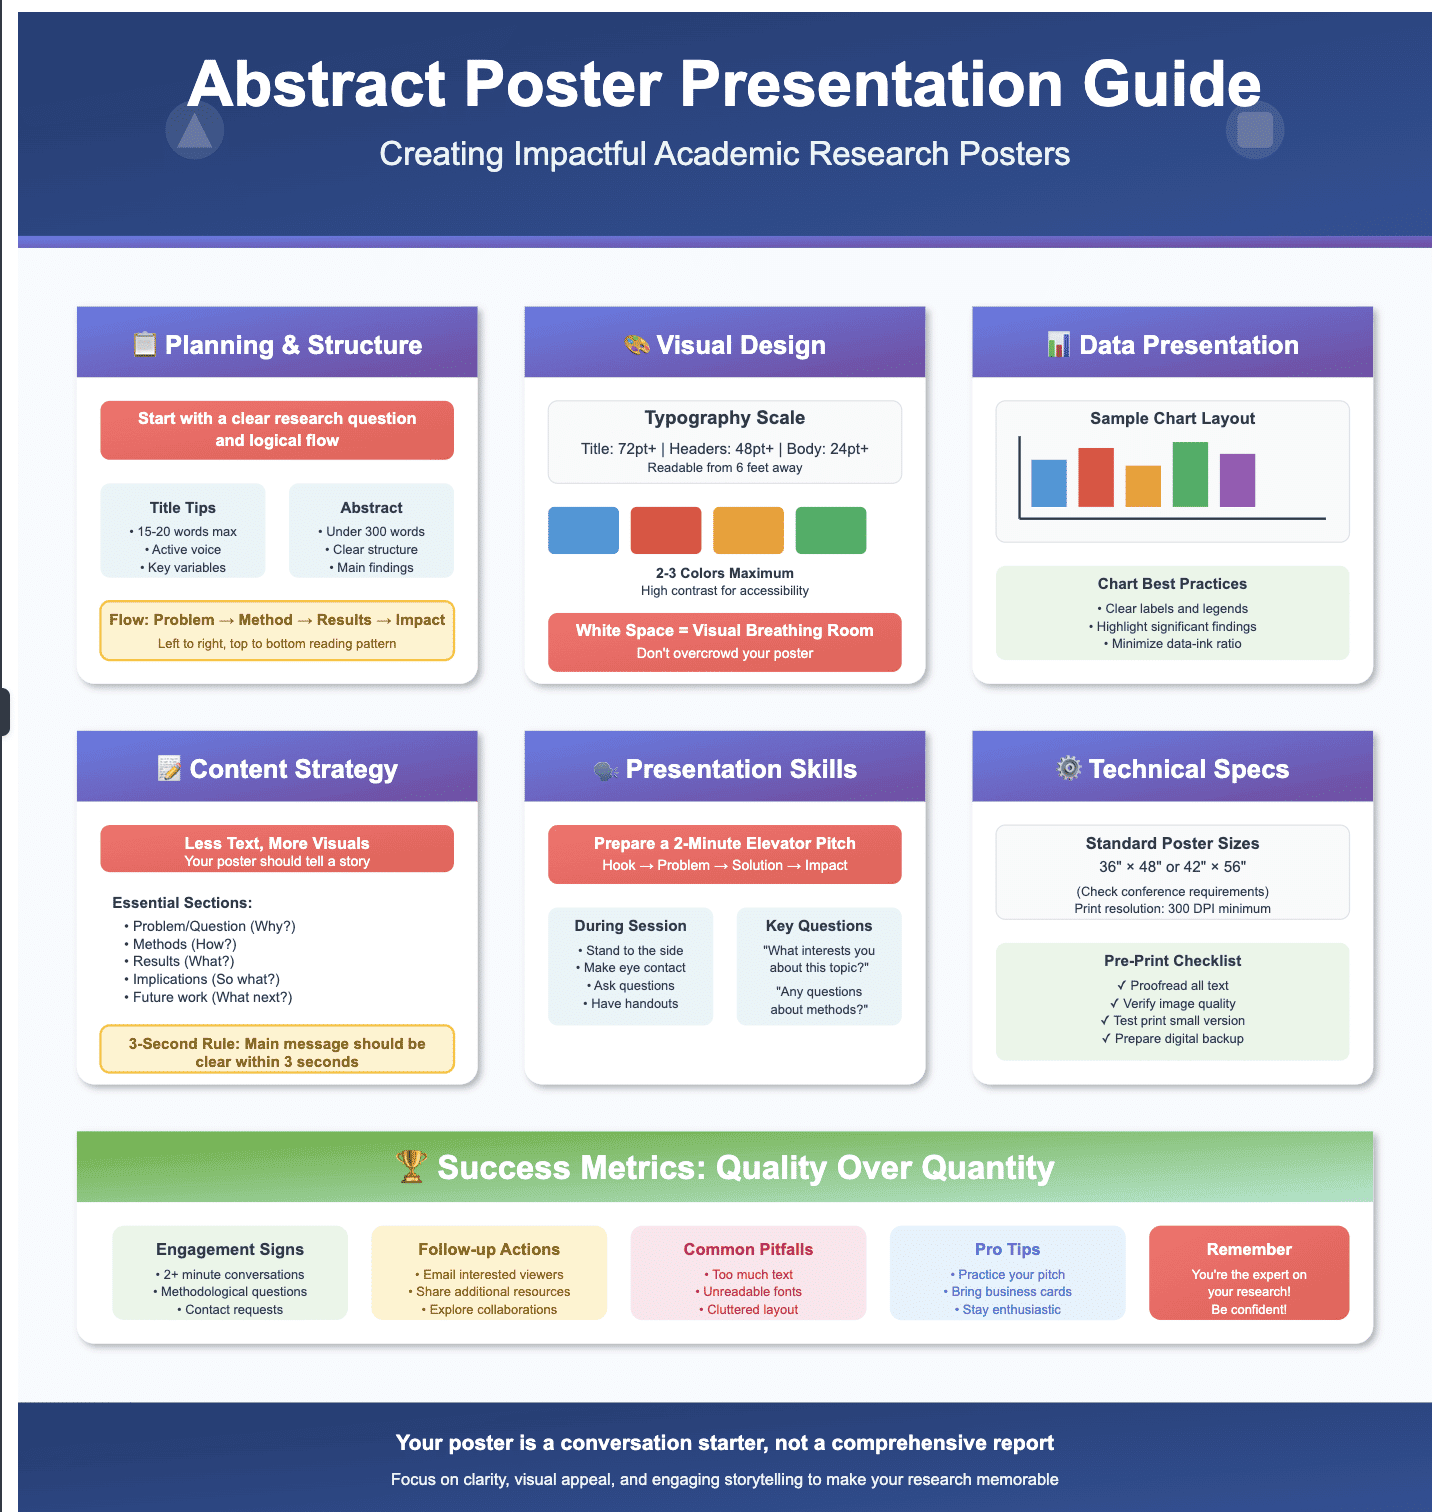
    Creating an abstract poster presentation is a valuable opportunity for college students to showcase their research projects in a concise and visually engaging format. This form of academic poster is commonly used at conferences, symposia, and poster sessions to effectively communicate research findings to a diverse audience.

    An effective poster presentation combines a well-structured abstract with a thoughtfully designed poster. The abstract is a short, concise overview of your research project, typically ranging from 100 to 300 words, and should clearly state your research question, methods used, key results, and the implications of your work. This summary not only guides the content of your poster but also helps attendees quickly grasp the essence of your study.

    When designing your poster, consider using a poster template to ensure a clean and organized layout. PowerPoint is a commonly used tool for creating posters, offering various scientific poster templates that can be customized to fit your needs. Pay attention to font choices and sizes to enhance readability, and use graphs and visuals to illustrate your findings effectively. Maintaining white space and avoiding clutter will make your poster more visually appealing and easier to navigate.

    Participating in a poster session allows you to engage directly with conference attendees, discuss your research findings, and receive feedback that can inform future research. It’s an excellent platform for networking and developing your presentation skills, especially if you’re considering transitioning to an oral presentation format in the future.

    What is a poster presentation?

    A poster presentation is a visual method of communicating your research project at an academic event or conference, such as a symposium or poster session. It involves creating a research poster, often using a poster template in tools like PowerPoint, and presenting your poster to conference attendees in a more informal, one-on-one setting than an oral presentation.

    Unlike a scientific paper, a poster offers a concise research poster format that highlights key elements of your study: your research question, methods used, research findings, and the implications of your work. An effective poster is visually appealing, easy to understand, and includes key visuals like a graph, table, or image that support your findings. The readability of your poster depends on thoughtful poster design, appropriate font choices, clear layout, and good use of white space.

    Why is a poster important for a research project?

    How to Create an Abstract Poster Presentation with Example
    Why is a poster important for a research project

    Here’s why creating a scientific poster is crucial:

    1. Clarify and Communicate Your Research

    Designing a concise research poster compels you to distill your study’s essence—your research question, methods used, key findings, and the implications of your work—into an accessible format. This process not only deepens your comprehension but also hones your ability to convey complex ideas succinctly. An effective poster utilizes clear font choices, strategic white space, and informative visuals like graphs to enhance readability and engagement.

    2. Receive Constructive Feedback

    Presenting at a poster session offers a unique opportunity for direct interaction with conference attendees. Engaging discussions can provide valuable insights, challenge your assumptions, and suggest avenues for future research. This immediate feedback loop is instrumental in refining your work and considering new perspectives.

    3. Enhance Your Academic Profile

    Participating in poster presentations demonstrates your active involvement in scholarly activities. Including these experiences in your CV showcases your commitment to research and your ability to communicate findings effectively. It’s a testament to your initiative and can distinguish you in competitive academic or professional settings.

    4. Develop Presentation Skills

    Creating and delivering a poster presentation cultivates essential skills such as public speaking, visual communication, and audience engagement. These competencies are transferable and beneficial across various academic and professional contexts. Utilizing tools like PowerPoint and adhering to a well-structured poster template can aid in crafting a compelling narrative.

    5. Foster Networking and Collaboration

    Engaging with peers and experts during poster sessions can lead to meaningful connections, potential collaborations, and mentorship opportunities. Discussing your research findings in person allows for dynamic exchanges that can inspire new ideas and partnerships.

    6. Contribute to the Academic Community

    By sharing your work through a poster display, you contribute to the collective knowledge of your field. Your insights can inform others’ research, spark discussions, and influence ongoing studies. This collaborative spirit is at the heart of academic advancement.

    How to choose the right poster template?

    Selecting the appropriate poster template is a crucial step in crafting an effective poster presentation. A well-chosen template not only enhances the visual appeal of your scientific poster but also ensures that your research findings are communicated clearly and professionally. Here are key considerations to guide you in choosing the right template:

    1. Align with Conference Requirements

    Before selecting a poster template, review the submission guidelines provided by the event or conference organizers. These guidelines often specify the required poster size, orientation (landscape or portrait), and any mandatory elements such as institutional logos. Adhering to these specifications is essential for your poster display to be accepted and properly presented.

    2. Choose the Appropriate Poster Size

    Common poster sizes include 36×48 inches, 42×60 inches, and A0 dimensions. Your choice should accommodate the amount of content you intend to present without overcrowding. A larger poster board allows for more white space, which improves readability and overall poster design.

    3. Utilize User-Friendly Software

    Tools like PowerPoint are widely used for creating research posters due to their accessibility and ease of use. Many institutions and online platforms offer free PowerPoint poster templates that can be customized to fit your needs. These templates often come with predefined sections for your poster abstract, methods used, graphs, and other essential components.

    4. Prioritize Readability and Visual Hierarchy

    An effective poster employs clear font choices and sizes to guide the reader through the content. Use larger fonts for headings and ensure that the body text is legible from a reasonable distance. Incorporate graphs and visuals to illustrate key points, and maintain consistent formatting throughout.

    5. Customize to Reflect Your Research

    While poster templates provide a structural foundation, it’s important to tailor them to your specific research project. Adjust color schemes, rearrange sections if necessary, and include elements that highlight the uniqueness of your study. This customization ensures that your poster presentation stands out and effectively communicates your research question and findings.

    Key Elements of a Research Poster

    Creating an effective poster presentation is essential for conveying your research project clearly and engagingly. A well-designed scientific poster not only summarizes your work but also captures the attention of conference attendees, facilitating meaningful discussions during poster sessions. This section outlines the critical components and design principles to help you craft a compelling academic poster.

    What are the essential components of a good poster presentation?

    What are the essential components of a good poster presentation?
    What are the essential components of a good poster presentation?

    An impactful research poster typically includes the following sections:

    1. Title: A concise and informative title (ideally under 10 words) that clearly reflects your research question.
    2. Authors and Affiliations: List all contributors and their institutional affiliations, often accompanied by institutional logos.
    3. Abstract: A brief poster abstract summarizing the purpose, methods, results, and conclusions of your study.
    4. Introduction: Provides background information and the rationale for your research project.
    5. Methods: Details the methods used in your study, including experimental design and data collection procedures.
    6. Results: Presents your findings using graphs, tables, and figures to illustrate key data points.
    7. Discussion/Conclusion: Interprets the results, discusses their significance, and outlines the implications of your work and potential future research directions.
    8. References: Cite all sources and literature referenced in your poster.
    9. Acknowledgments: Recognize individuals or organizations that supported your research.
    10. Contact Information: Provide your email or other contact details for attendees interested in discussing your work further.

    How to design your poster for maximum impact?

    Effective poster design enhances readability and engages your audience. Consider the following tips:

    • Layout: Organize content in a logical flow, typically from left to right and top to bottom. Use columns to separate sections clearly.
    • White Space: Incorporate sufficient white space to prevent clutter and make the poster more inviting.
    • Visuals: Use high-quality graphs, images, and charts to represent data visually. Ensure all visuals are clearly labeled and directly related to your content.
    • Color Scheme: Choose a consistent and professional color palette that enhances contrast and readability.
    • Consistency: Maintain uniformity in font styles, sizes, and formatting throughout the poster.
    • Simplicity: Aim for a concise research poster by summarizing information and avoiding excessive text.

    What font and format should you use for clarity?

    Choosing the right font and formatting is crucial for the readability of your scientific poster:

    • Font Type: Use sans-serif fonts like Arial, Calibri, or Helvetica for body text, as they are easier to read from a distance.
    • Font Size: Ensure that text is legible from at least 1.5 meters away. Recommended sizes are:
      • Title: 85–100 pt
      • Headings: 36–44 pt
      • Body Text: 24–32 pt
    • Formatting: Use bold headings to distinguish sections, bullet points for lists, and avoid using all caps, which can be hard to read.
    • Alignment: Left-align text for easier reading, and ensure consistent spacing between lines and paragraphs.

    Writing an Abstract for Your Poster

    Crafting a compelling poster abstract is a vital step in preparing an academic poster. This concise summary not only introduces your research project but also entices conference attendees to engage with your poster presentation during a poster session. An effective abstract succinctly conveys your study’s essence, ensuring clarity and impact.

    How to write a concise and effective poster abstract?

    A well-structured poster abstract typically follows the IMRaD format: Introduction, Methods, Results, and Discussion. This structure provides a logical flow, guiding readers through your research question, the methods used, the research findings, and the implications of your work.

    Key Tips:

    • Be Concise: Aim for 150–250 words, focusing on the most critical aspects of your study.
    • Use Clear Language: Avoid jargon and ensure that your abstract is understandable to a broad audience.
    • Highlight Novelty: Emphasize what makes your research project unique or significant.
    • Maintain Objectivity: Present your findings factually, without exaggeration.
    • Proofread: Ensure correct grammar and spelling to maintain professionalism.

    Remember, the abstract sets the tone for your poster presentation and can influence an attendee’s decision to learn more about your work.

    Nursing Poster Abstract Format

    A nursing poster abstract is a structured visual presentation format used to communicate nursing research, evidence-based practice projects, quality improvement initiatives, or clinical case studies at conferences and healthcare settings.

    An effective scientific poster abstract should encompass the following elements:

    1. Background: Provide context for your study, outlining the problem or gap your research addresses.
    2. Objective: Clearly state your research question or the purpose of your study.
    3. Methods: Briefly describe the methods used, including study design, data collection, and analysis techniques.
    4. Results: Summarize the key research findings, highlighting significant data points or trends.
    5. Conclusion: Discuss the implications of your work, its relevance to the field, and potential directions for future research.

    Avoid including detailed data, graphs, or references in the abstract; these are better suited for the main body of your research poster.

    Core Structure:

    Header Section:

    • Concise title (15-20 words) with nursing focus
    • “Abstract Poster Presentation” subtitle
    • Author names with nursing credentials (RN, BSN, MSN, PhD)
    • Healthcare institution/unit affiliations

    Abstract Block (250-300 words):

    • Background/Problem: Clinical significance and patient impact
    • Objective: Clear, measurable nursing practice goal
    • Methods/Approach: Study design, setting, population, intervention
    • Results/Outcomes: Key findings with specific metrics and clinical significance
    • Implications for Nursing Practice: How findings change patient care and practice

    Visual Layout:

    • Professional design with healthcare-appropriate colors (blues, greens)
    • Large fonts (Title: 72pt+, Headers: 48pt+, Body: 24pt+) for 4-6 foot viewing distance
    • Logical flow from problem identification through practice implications
    • Data visualization using charts, graphs, and infographics
    • 40-50% white space for clean, readable appearance

    This format bridges research and clinical practice, translating evidence into actionable insights that improve patient care and advance nursing practice in healthcare settings

    Poster Abstract Example

    Here's professional nursing poster abstract for a nursing case study
    professional nursing poster abstract for a nursing case study

    What to include in your abstract for a scientific poster?

    Essential Components (250-300 words total):

    1. Background/Introduction (2-3 sentences)

    • State the research problem or clinical issue
    • Provide context and significance
    • Include relevant statistics or prevalence data
    • Identify the knowledge gap your work addresses

    Example: “Hospital-acquired infections affect 1.7 million patients annually, contributing to 99,000 deaths. Current prevention protocols show inconsistent implementation across units.”

    2. Objective/Purpose (1-2 sentences)

    • Clear, specific aim of your study or project
    • Use action verbs (evaluate, compare, determine, assess)
    • Include primary endpoint or main outcome measure

    Example: “To evaluate the effectiveness of a standardized hand hygiene protocol in reducing infection rates in medical-surgical units.”

    3. Methods/Design (3-4 sentences)

    • Study design (RCT, cohort, case-control, quality improvement)
    • Setting and participants (sample size, inclusion criteria)
    • Key interventions or exposures
    • Primary outcome measures and data collection methods
    • Statistical analysis approach (if applicable)

    Example: “Pre-post intervention study in two 32-bed units over 6 months. Implemented standardized protocol with staff education and compliance monitoring. Measured infection rates, hand hygiene compliance, and length of stay using hospital surveillance data.”

    4. Results (3-4 sentences)

    • Primary outcome with specific numbers and statistics
    • Secondary outcomes and key findings
    • Include effect sizes, confidence intervals, or p-values
    • Report clinically meaningful changes

    Example: “Infection rates decreased from 4.2 to 1.8 per 1,000 patient days (58% reduction, p<0.001). Hand hygiene compliance increased from 67% to 91%. Length of stay decreased by 1.2 days (95% CI: 0.8-1.6).”

    5. Conclusions/Implications (2-3 sentences)

    • State main finding clearly
    • Clinical or practical significance
    • Broader implications for practice, policy, or future research
    • Limitations (if space allows)

    Example: “Standardized protocols significantly reduce healthcare-associated infections when combined with staff education and monitoring. Results support organization-wide implementation with potential cost savings of $2.3 million annually.”

    Scientific Poster Abstract example
    Scientific Poster Abstract example

    Common mistakes to avoid when writing an abstract.

    To ensure your poster abstract is effective, steer clear of these common pitfalls:

    • Lack of Clarity: Avoid vague statements; be specific about your study’s purpose and findings.
    • Overuse of Jargon: Excessive technical language can alienate readers unfamiliar with the terminology.
    • Omitting Key Information: Ensure all critical components, background, objective, methods, results, and conclusion are included.
    • Including Excessive Detail: The abstract should provide a summary, not exhaustive details or data.
    • Poor Grammar and Spelling: Errors can undermine the credibility of your poster presentation.
    • Ignoring Guidelines: Adhere to any specific instructions regarding word count, font, or format provided by the event or conference organizers.

    Preparing Your Poster for Presentation

    Preparing your research poster for a symposium involves more than just compiling data; it requires thoughtful design and strategic planning to effectively communicate your research findings. An effective poster presentation not only showcases your work but also engages conference attendees, sparking meaningful discussions during the poster session.

    Abstract Poster Presentation example
    Abstract Poster Presentation example

    How to prepare your poster for a symposium?

    • Understand the Symposium Guidelines: Before you begin, familiarize yourself with the submission requirements of the event or conference. These may include specifications on poster size, orientation, and mandatory elements like institutional logos.
    • Select an Appropriate Poster Template: Utilize a poster template that aligns with the symposium’s standards. Many institutions provide scientific poster templates compatible with PowerPoint, facilitating consistency and adherence to formatting guidelines.
    • Craft a Concise Abstract: Your poster abstract should succinctly summarize your research project, highlighting the research question, methods used, key results, and the implications of your work. Aim for clarity and brevity to quickly convey the essence of your study.
    • Design for Readability: Ensure your poster design incorporates readable fonts, appropriate format, and logical flow. Use headings and subheadings to guide viewers through your content, and maintain consistency in font styles and sizes.
    • Incorporate Visual Elements: Enhance your poster with graphs, charts, and images that effectively illustrate your data. Visuals should be high-quality and directly relevant to your content, aiding in the comprehension of complex information.
    • Prepare for Interaction: Anticipate questions from attendees and prepare concise explanations of your work. Consider creating handouts or supplementary materials for interested viewers.

    What are the best practices for a poster session?

    • Engage with Attendees: Stand by your poster board during the poster session, ready to discuss your research findings. Be approachable and open to questions, facilitating a two-way dialogue.
    • Deliver a Clear Oral Presentation: Prepare a brief oral presentation summarizing your research project. Practice delivering this summary confidently, ensuring you can convey your message effectively within a short time frame.
    • Utilize Visual Aids: Point to specific sections of your academic poster during discussions to illustrate key points. This interactive approach helps conference attendees better understand your work.
    • Gather Feedback: Use the opportunity to receive constructive feedback on your research. Engaging with a diverse audience can provide new perspectives and ideas for future research.

    How to make your poster visually appealing?

    • Maintain a Clean Layout: Organize your poster design using columns and sections, allowing for easy navigation. Incorporate sufficient white space to prevent clutter and enhance readability
    • Choose Appropriate Fonts and Colors: Select sans-serif fonts like Arial or Helvetica for clarity. Use a consistent font size hierarchy: larger for titles, medium for headings, and smaller for body text. Opt for a color scheme with 2-3 complementary colors, ensuring high contrast between text and background. 
    • Use High-Quality Visuals: Incorporate clear, high-resolution graphs and images that directly support your content. Ensure all visuals are properly labeled and integrated seamlessly into your poster template.
    • Highlight Key Information: Use bolding or color accents to draw attention to important findings or sections. However, use these features sparingly to avoid overwhelming the viewer.
    • Ensure Accessibility: Design your scientific poster with accessibility in mind. Use color combinations that are distinguishable for individuals with color vision deficiencies and ensure text is legible from a distance.

    Presenting Your Poster to an Audience

    Presenting your research poster effectively is crucial for engaging conference attendees and conveying your findings succinctly. This section guides engaging your audience, delivering an impactful oral presentation, and adeptly handling questions during your poster session.

    How to engage attendees during your poster presentation?

    Engagement begins with the visual appeal of your poster design. Utilize a clean layout, readable fonts, and strategic use of white space to draw attention. Incorporate graphs and visuals to illustrate key points, ensuring they are clear and directly related to your research findings.

    During the poster session, position yourself beside your poster board, ready to interact with attendees. Greet passersby with a friendly demeanor, making eye contact and offering a brief overview of your research project. This approach invites questions and fosters dialogue.

    To prepare for diverse interactions, consider role-playing exercises that simulate various attendee scenarios. Such activities can boost confidence and readiness to engage with different audience types. 

    What should you include in your oral presentation?

    Your oral presentation should complement your poster, providing a concise narrative of your research project. Aim for a brief “elevator pitch” lasting no more than two minutes, covering:

    • Introduction: State your research question and its significance.
    • Methods: Summarize the methods used in your study.
    • Results: Highlight key research findings.
    • Conclusion: Discuss the implications of your work and potential future research directions.

    Tailor your presentation to your audience, avoiding jargon and emphasizing clarity. Practice delivering your summary to ensure a confident and engaging delivery.

    How to handle questions from conference attendees?

    Anticipate questions by familiarizing yourself with all aspects of your research project, including data, methodology, and conclusions. When addressing questions:

    • Listen Carefully: Ensure you understand the question before responding.
    • Respond Clearly: Provide concise answers, referencing specific parts of your poster when applicable.
    • Admit Uncertainty: If unsure, acknowledge it and suggest areas for future research.
    • Encourage Dialogue: Engage in discussions that may provide new insights or perspectives on your work.

    Remember, questions are opportunities to delve deeper into your research and demonstrate your expertise.

    Tips for a Successful Poster Presentation

    Tips for a Successful Poster Presentation

    When it comes to creating an abstract poster presentation that captivates your audience, there are several key tips to keep in mind. These expert tips for designing an abstract poster will help you make a lasting impression and effectively communicate your research.

    • Choose a high-traffic location: To ensure maximum visibility, select a location for your poster that is easily accessible and attracts a large number of conference attendees.
    • Practice your presentation: Rehearse your presentation multiple times to gain confidence and refine your delivery. This will help you smoothly convey your research findings and answer questions with ease.
    • Engage in discussions: Encourage attendees to engage with your poster by inviting questions and initiating meaningful discussions. This will not only enhance the overall impact of your presentation but also provide valuable insights and potential collaborations.
    • Seek feedback: Take advantage of the opportunity to seek feedback from mentors or colleagues. Their insights can help you improve your presentation skills and refine your research message.

    By following these tips, you can optimize your abstract poster presentation and increase your chances of creating a memorable experience for both yourself and your audience

    Where to find research poster templates and design inspiration?

    Utilizing pre-designed poster templates can streamline the creation process and ensure adherence to standard poster sizes and formats. Here are some resources:

    • Canva: Offers a variety of customizable research poster templates suitable for different fields and purposes. 
    • PosterNerd: Provides free PowerPoint templates for scientific posters, accommodating various poster sizes and orientations. 
    • Adobe Express: Features a selection of research poster templates that can be tailored to your specific needs, with options for incorporating institutional logos and branding. 
    • Venngage: Offers professional research poster templates with intuitive design tools, allowing for easy customization and incorporation of visual elements.

    Frequently Asked Questions

    How to write an abstract of a presentation?

    To write an abstract for a poster presentation or oral presentation, start by clearly stating your research question, followed by a brief overview of the methods used, key research findings, and the implications of your work. Keep it concise, focused, and relevant to the audience. Aim for clarity and avoid technical jargon.

    What does abstract mean on a poster board?

    On a poster board, the abstract refers to a short summary of the research project being presented. This poster abstract helps conference attendees quickly understand the purpose, methodology, results, and significance of the study without reading the entire poster.

    How to write a poster presentation?

    To write a poster presentation, begin with a compelling title, then organize your content using clear headings like Introduction, Methods, Results, and Conclusion. Use visuals like graphs, charts, and images to support your findings. Follow a poster template and maintain consistent font, format, and poster design for readability. End with key research findings and potential future research directions.

    How many words should an abstract be for a poster?

    A typical poster abstract should be between 150 and 300 words, depending on the submission guidelines of the event or conference. It should be concise yet informative, summarizing the most important elements of the research project.

    Frequently Asked Questions About Poster Presentations

    Can you present a poster at more than one conference?

    Yes, you can present the same poster at multiple conferences, but with important considerations:

    ✅ Generally Acceptable:

    • Presenting at different types of conferences (local, national, international)
    • Sharing with different audiences or specialties
    • Educational or quality improvement projects
    • Student research presentations

    ⚠️ Check First:

    • Conference submission guidelines (some prohibit previously presented work)
    • Funding agency requirements
    • Institution policies
    • Journal submission plans (some journals won’t accept previously presented research)

    Best Practice: Always disclose previous presentations in your submission and update your poster with new data or insights when possible.

    How to cite a poster presentation APA, MLA and AMA

    APA Style (7th Edition):

    Author, A. A. (Year, Month Day). Title of poster [Poster presentation]. Name of Conference, Location.

    Example:

    Johnson, S. M., & Rodriguez, M. L. (2024, March 15). Reducing hospital readmissions through patient education interventions [Poster presentation]. American Nurses Association Annual Conference, Chicago, IL.

    MLA Style:

    Author Last Name, First Name. "Title of Poster." Conference Name, Date, Location. Poster presentation.

    AMA Style:

    Author AA. Title of poster. Poster presented at: Conference Name; Date; Location.

    How to cite poster presentations that weren’t published (AMCAS)

    For AMCAS (American Medical College Application Service) applications:

    Research/Presentations Section:

    • Title: Full title of your poster
    • Type: Select “Poster Presentation”
    • Status: “Completed”
    • Date: Presentation date
    • Description: Brief summary of research and your role

    Example Entry:

    Title: "Impact of Telemedicine on Rural Healthcare Access"
    Type: Poster Presentation
    Date: 03/2024
    Organization: State Medical Student Research Symposium
    Description: Conducted literature review and data analysis examining telemedicine adoption in rural areas. Presented findings on improved patient outcomes and access barriers. Served as lead researcher and presenter.

    Note: Even unpublished poster presentations demonstrate research experience and should be included in your application.

    What is a poster presentation?

    Definition: A poster presentation is a visual display of research findings, case studies, or projects presented at conferences, symposiums, or academic meetings.

    Key Characteristics:

    • Visual Format: Large format display (typically 36″×48″ or 42″×56″)
    • Standalone Summary: Can be understood without oral presentation
    • Interactive Element: Presenter available for questions and discussion
    • Structured Content: Background, methods, results, conclusions
    • Professional Audience: Peers, researchers, clinicians, students

    Types:

    • Research studies
    • Quality improvement projects
    • Case studies
    • Literature reviews
    • Evidence-based practice initiatives

    Purpose: Share knowledge, network with peers, receive feedback, advance career development

    How to dress for a poster presentation

    Professional Business Attire Guidelines:

    👔 Men:

    • Suit or dress pants with button-down shirt
    • Tie (conservative colors/patterns)
    • Dress shoes (polished, closed-toe)
    • Blazer or suit jacket (optional but recommended)
    • Avoid: Jeans, sneakers, casual shirts, loud patterns

    👗 Women:

    • Business suit, dress, or professional separates
    • Closed-toe shoes (comfortable for standing)
    • Conservative necklines and hemlines
    • Professional blazer or cardigan
    • Avoid: Revealing clothing, casual wear, excessive jewelry

    🎯 General Tips:

    • Comfort is key – you’ll be standing for hours
    • Layer appropriately – conference rooms vary in temperature
    • Name tag visibility – avoid high necklines that hide badges
    • Pocket for business cards – easy access for networking
    • Conservative colors – navy, black, gray, earth tones
    • Well-groomed appearance – professional hairstyle, minimal fragrance

    Conference-Specific: Check if the event has specific dress codes or cultural considerations.

    How to cite a poster presentation on CV

    Academic CV Format:

    Section: “Presentations” or “Scholarly Presentations”

    Poster Presentations
    
    Johnson, S.M., Rodriguez, M.L., Chen, P. (2024). "Reducing Hospital Readmissions Through Patient Education Interventions." American Nurses Association Annual Conference, Chicago, IL, March 15, 2024.
    
    Smith, J.A., Johnson, S.M. (2023). "Telemedicine Adoption in Rural Healthcare Settings." State Medical Research Symposium, Denver, CO, October 12, 2023.

    Professional/Clinical CV Format:

    PRESENTATIONS AND RESEARCH
    
    2024    "Reducing Hospital Readmissions Through Patient Education"
            Poster presentation, American Nurses Association Conference, Chicago, IL
    
    2023    "Telemedicine in Rural Healthcare" 
            Poster presentation, State Medical Research Symposium, Denver, CO

    Formatting Tips:

    • Chronological order (most recent first)
    • Complete citation including all authors
    • Venue and location clearly identified
    • Consistent formatting throughout section
    • Separate from publications if you have both

    How long should a poster presentation be?

    Poster Session Duration:

    • Typical session: 1-3 hours
    • Individual interactions: 2-10 minutes per viewer
    • Elevator pitch: 30-60 seconds
    • Detailed discussion: 5-15 minutes for interested parties

    Presentation Components:

    📋 Poster Content Reading Time:

    • Quick scan: 30 seconds (title and main results)
    • Complete reading: 3-5 minutes
    • Detailed study: 10-15 minutes

    🗣️ Verbal Presentation Lengths:

    • Elevator pitch: 30-60 seconds (main finding)
    • Standard summary: 2-3 minutes (overview)
    • Detailed explanation: 5-10 minutes (methodology discussion)
    • Q&A session: Variable (2-15 minutes)

    ⏰ Preparation Tips:

    • Practice multiple versions: 30-second, 2-minute, and 5-minute summaries
    • Gauge audience interest: Start short, expand if they’re engaged
    • Be flexible: Adapt to viewer’s time constraints and interest level
    • Stay available: Remain by your poster for the entire session duration

    Session Expectations: You should be prepared to discuss your work for the entire poster session duration, typically 90 minutes to 3 hours, with individual conversations varying based on audience interest.

    How to list Poster presentation on CV

    Detailed CV Formatting Guide:

    Academic/Research CV:

    Section Header Options:

    • “Presentations”
    • “Scholarly Presentations”
    • “Conference Presentations”
    • “Research Presentations”

    Format 1 – Full Citation Style:

    PRESENTATIONS
    
    Peer-Reviewed Poster Presentations
    Johnson, S.M., Rodriguez, M.L., & Chen, P.K. (2024, March). Reducing hospital readmissions through evidence-based patient education interventions. Poster presented at the American Nurses Association Annual Conference, Chicago, IL.
    
    Smith, J.A., Johnson, S.M., & Williams, R.T. (2023, October). Telemedicine adoption barriers in rural healthcare settings: A systematic review. Poster presented at the National Rural Health Conference, Denver, CO.

    Format 2 – Structured List:

    POSTER PRESENTATIONS
    
    2024    Johnson, S.M., Rodriguez, M.L., Chen, P.K. "Reducing Hospital Readmissions Through Evidence-Based Patient Education." American Nurses Association Annual Conference, Chicago, IL.
    
    2023    Smith, J.A., Johnson, S.M., Williams, R.T. "Telemedicine Adoption Barriers in Rural Healthcare: A Systematic Review." National Rural Health Conference, Denver, CO.

    Clinical/Professional CV:

    Condensed Format:

    PROFESSIONAL PRESENTATIONS
    
    2024    • "Patient Education and Readmission Reduction"
              ANA Annual Conference, Chicago, IL (Poster)
    
    2023    • "Rural Healthcare Technology Implementation" 
              National Rural Health Conference, Denver, CO (Poster)

    Categorization Options:

    By Presentation Type:

    • Invited Presentations
    • Peer-Reviewed Poster Presentations
    • Local/Regional Presentations

    By Career Stage:

    • Graduate Student Presentations
    • Professional Presentations
    • Collaborative Research Presentations

    By Topic Area:

    • Clinical Research Presentations
    • Quality Improvement Presentations
    • Educational Presentations

    Additional Tips:

    🔢 Numbering/Quantifying: If you have many presentations, consider adding a summary:

    PRESENTATIONS (Total: 12)
    Peer-reviewed poster presentations (8)
    Invited oral presentations (3)
    Regional conference presentations (1)

    👥 Author Order:

    • First author: Bold or underline your name
    • Contributing author: List all authors in order
    • Team presentations: Clearly indicate your role

    📍 Location Details:

    • Include city and state/country
    • Virtual presentations: Note “Virtual Conference”
    • International: Include country

    🏆 Recognition: If your poster won awards:

    2024    Johnson, S.M., et al. "Reducing Hospital Readmissions..." 
            American Nurses Association Conference, Chicago, IL
            *Recipient: Best Student Poster Award*

    📱 Digital Age Additions:

    Social media presentation hashtags (if relevant)

    QR codes linking to poster PDFs

    DOI numbers if available

    Online presentation links

  • How to Write a PICOT Question in 2025 | Explained with Examples

    How to write a PICOT Question

    Developing effective nursing PICOT topics is critical for nursing students and practicing nurses. The PICOT framework is the foundation for evidence-based nursing research, allowing healthcare professionals to formulate precise clinical questions that drive meaningful improvements in patient care. Whether you’re a nursing student working on a research paper or an experienced nurse seeking to enhance your practice, understanding how to craft well-structured PICOT questions is essential for conducting valuable research that contributes to the nursing profession. This comprehensive guide will walk you through everything you need to know about nursing PICOT topics, from understanding the basic framework to exploring over 200 example topics across various specialties.

    What is the PICO (T) Framework

    Nursing PICOT Topics

    The PICOT framework is a structured method for formulating clinical questions in nursing research. Each element of the acronym represents a key component that helps narrow down your research focus:

    • P (Population/Patient): Specifies the patient group or demographic of interest (e.g., adults with type 1 diabetes, premature babies, patients with breast cancer)
    • I (Intervention): Describes the main treatment, approach, or action being considered (e.g., skin-to-skin contact, blood pressure monitoring, pain relief medication)
    • C (Comparison): Identifies an alternative intervention or standard of care for comparison (e.g., drying and wrapping, traditional monitoring, placebo)
    • O (Outcome): Defines the expected or measurable result (e.g., improved oxygen saturation levels, lower blood pressure, reduced symptoms)
    • T (Time): Indicates the timeframe for measuring outcomes (e.g., within 6 weeks, over 12 months)

    Sometimes, you may see the acronym “PICO” used instead of “PICOT,” which simply omits the time element. Both formats are valid approaches to nursing research, though PICOT provides additional specificity with its temporal component. The PICO question format is particularly useful when time is not a critical factor in your research design.

    Why Are Nursing PICOT Topics Important?

    Nursing PICOT topics serve as the cornerstone of evidence-based practice, a fundamental principle in modern healthcare. By formulating a good PICOT question, you establish clear parameters for your research, making it easier to:

    1. Search for relevant evidence in the medical literature
    2. Evaluate the quality and applicability of existing research
    3. Apply findings directly to clinical practice
    4. Measure outcomes effectively
    5. Contribute meaningful data to the nursing knowledge base

    For nursing students working on a nursing research assignment, developing strong PICOT questions demonstrates critical thinking skills and academic rigor. For practicing nurses, these questions lead to improvements in nursing practice that can enhance patient care, reduce complications, and promote better health outcomes.

    How to Write a Good Nursing PICOT Question

    Here's a how to write a picot question infographic that explains how to develop effective PICO questions for evidence-based nursing practice. This is a crucial skill for BSN students to master as they begin conducting research and applying evidence to clinical practice. The infographic covers: What is a PICO Question? A structured approach to formulating clinical questions for evidence-based practice research that helps you find relevant evidence to inform nursing decisions and improve patient care. The PICO Framework Components: P - Population/Patient/Problem Who is your patient? What is their age, gender, ethnicity, disease, or condition? I - Intervention What treatment, diagnostic test, or exposure are you considering? C - Comparison What is the alternative to the intervention? Standard of care or different intervention? O - Outcome What are you trying to measure, improve, or affect? Should be specific and measurable T - Time Frame (Optional) The duration over which the outcome is measured Example PICO Questions: In adults with Type 2 diabetes (P), does a low-carbohydrate diet (I) compared to a low-fat diet (C) result in better glycemic control over a 6-month period? (O) In hospitalized elderly patients (P), does hourly rounding (I) compared to standard care (C) reduce the incidence of falls during hospitalization? (O)
    How to write a PICOT Question

    Creating effective nursing PICOT questions is both an art and a science. Here’s a step-by-step process to help you develop research questions that will yield valuable insights:

    1. Identify a Clinical Problem

    Begin by observing areas in your nursing practice or studies where improvements could be made. Good PICOT topics often emerge from real clinical challenges. For example, you might notice that patients with blood pressure issues respond differently to various monitoring approaches, or that breast cancer patients report varying levels of satisfaction with different education methods.

    2. Narrow Your Focus

    Rather than tackling broad issues, focus on specific aspects of care. Instead of studying “diabetes management” in general, you might focus on “monitoring blood glucose in adolescents with type 1 diabetes using continuous monitoring versus traditional methods.”

    3. Formulate Your Question

    Structure your clinical question using the PICOT format. For example:

    “In mechanically ventilated patients (P), how does regular repositioning (I) compared to standard care (C) affect oxygen saturation levels (O) during the first 48 hours of ventilation (T)?”

    4. Evaluate Your Question

    A good PICOT question should be:

    • Specific and clearly defined
    • Measurable through available methods
    • Achievable within your resources
    • Relevant to nursing practice
    • Time-bound with a clear timeframe

    5. Refine as Needed

    Don’t hesitate to revise your question as you learn more about the topic. The research process is iterative, and your question may evolve as you conduct your literature review.

    how to write a picot question
    How to write a PICOT question

    The Research Process for Nursing PICOT Topics

    Once you’ve selected a nursing PICOT topic and formulated your question, you’re ready to begin the research process. Here’s a brief overview of the steps involved:

    1. Literature Review: Search for existing evidence related to your PICOT question. This will help you understand what’s already known about your topic and identify gaps in the literature.
    2. Study Design: Develop an appropriate research methodology based on your question. This may involve quantitative methods, qualitative approaches, or mixed methods.
    3. Data Collection: Gather relevant data according to your research design. This could include patient records, surveys, interviews, or observations.
    4. Data Analysis: Analyze your findings using appropriate statistical or qualitative methods.
    5. Interpretation: Conclude your analysis and consider the implications for nursing practice.
    6. Dissemination: Share your findings through presentations, publications, or implementation in clinical settings.

    Throughout this process, the PICOT question serves as a guide, helping you maintain focus and ensuring that your research addresses a specific clinical question with practical relevance to nursing.

    Frequently Asked Questions

    What are some good nursing topics for evidence-based research beyond the traditional PICOT format?

    Evidence-based nursing research extends beyond the PICOT framework to include various methodologies such as qualitative studies, mixed methods research, and systematic reviews. Some useful areas to explore include nursing workforce issues, healthcare technology implementation, interprofessional collaboration, and healthcare ethics. The perfect nursing research topic should align with your interests while addressing significant gaps in current knowledge or practice.

    How can I develop a background question that will eventually lead to a good PICOT question?

    A background question is broader than a PICOT question and helps you understand the general context of your research area. Start by identifying a clinical issue you’re curious about, then ask who, what, where, when, why, and how questions to explore different dimensions. For example, “How does hypertension affect elderly patients?” Once you have this foundational understanding, you can refine your focus into a specific PICOT question about interventions for blood pressure monitoring among this population.

    What makes this a question worth pursuing in a nursing research assignment?

    A question worth pursuing in nursing research demonstrates clinical significance, addresses a knowledge gap, offers potential for practical application, and is feasible within available resources. The clinical question will address problems frequently encountered in practice and provide solutions that can improve patient outcomes. Additionally, questions that align with national health priorities or healthcare organization goals often receive more support and resources for implementation.

    How can I ensure my nursing essay follows the PICO framework while still covering questions based on the PICO example I’ve chosen?

    To ensure your nursing essay properly follows the PICO framework, start by clearly defining each component (Population, Intervention, Comparison, Outcome) in your introduction. Structure your essay with dedicated sections for each PICO element, supporting each with relevant evidence from the literature. Use the framework as an organizational tool throughout your paper, referring back to it when discussing findings and implications. Including multiple question examples related to your PICO topic can demonstrate your understanding of how the framework can be applied in various clinical scenarios.

  • Evidence-Based Practice Paper Example for Nursing Students

    Introduction

    Evidence-based practice represents the integration of best available evidence, clinical expertise, and patient preferences to make informed decisions about healthcare interventions. The use of evidence-based practice in nursing ensures that care decisions are grounded in scientific evidence rather than tradition or intuition alone. It directly contributes to improved patient outcomes, standardization of care, and advancement of the nursing profession as a whole. This guide explores the fundamentals of evidence-based practice, provides a clear evidence-based practice paper example, and offers practical guidance for nursing students looking to excel in this essential area of their education.

    What Is EBP in Nursing and Evidence-Based Practice?

    At its core, evidence-based practice involves three key components: the best evidence available from systematic research, clinical expertise from healthcare providers, and patient values and preferences. When a nurse uses evidence-based practice, they’re engaging in a deliberate process that combines research and evidence with clinical expertise to deliver optimal care.

    Evidence-based practice nursing research has become the cornerstone of modern nursing practice, informing everything from basic nursing care techniques to complex nursing interventions. The integration of evidence-based practice into daily clinical decision making distinguishes modern medical practice from traditional approaches.

    For nursing students, learning to navigate the world of evidence-based practice often begins with writing an EBP paper or nursing essay. An evidence based practice essay demonstrates your ability to find relevant evidence, evaluate its quality, and apply it to real-world nursing care situations. Learning how to write an evidence-based practice research paper is a fundamental skill in nursing education.

    Evidence-based practice paper example cycle

    The Structure of an Evidence-Based Practice Paper

    Before diving into examples, it’s important to understand the typical structure of an evidence-based practice paper. While formats may vary slightly depending on academic requirements, most EBP papers include the following components:

    1. Introduction and Base Knowledge

    This section introduces the clinical question or problem being addressed and provides context for why this issue is significant to nursing practice. The background should include relevant statistics or information that highlights the importance of the topic. The purpose of this paper should be clearly stated early in the introduction.

    2. PICOT Question and Research Question Formulation

    Many evidence-based practice papers use the PICOT framework to formulate a clear, searchable clinical question:

    • P: Population/Patient
    • I: Intervention
    • C: Comparison
    • O: Outcome
    • T: Time

    For example, a research question might be: “In hospitalized elderly patients (P), how does hourly rounding (I) compared to standard care (C) affect fall rates (O) during a hospital stay (T)?”

    3. Literature Search Strategy for Nursing Research

    This section details how relevant research evidence was located, including databases searched, keywords used, inclusion/exclusion criteria, and the number of studies identified and ultimately selected for review. This approach demonstrates how to find relevant evidence for a nursing paper focused on specific nursing topics and clinical questions.

    4. Evidence Appraisal in Practice Essay

    Here, the nursing student critically evaluates the quality of the research evidence found, often using standardized tools to assess different types of studies. This section demonstrates the ability to distinguish between strong and weak evidence, which is essential for best practice in nursing.

    5. Synthesis of Evidence and Current Best Evidence

    This crucial section summarizes the findings from the selected studies and identifies patterns, contradictions, or gaps in the available evidence. The synthesis of current best evidence forms the foundation for the practice recommendations and showcases the best evidence-based practice approach.

    6. Practice Recommendations Based on Research Evidence

    Based on the evidence synthesis, the paper outlines specific recommendations for nursing practice, including how to implement evidence-based practice in clinical settings to improve patient care. This section showcases how to use evidence-based practice to create tangible improvements in clinical nursing.

    7. Implementation of Evidence-Based Practice Plan

    This section details how the evidence-based intervention could be implemented in a specific clinical setting, including necessary resources, potential barriers, and strategies to overcome them. The implementation of evidence-based practice often requires a change in practice culture and careful planning.

    8. Evaluation Plan for Evidence-Based Nursing Practice

    Finally, the paper describes how the effectiveness of the implemented evidence-based practice would be measured, including specific outcomes and data collection methods. Measuring outcomes helps determine if the use of evidence-based practice has actually improved patient outcomes.

    🏆 Best Evidence-Based Practice Paper Example: Implementation of Hourly Rounding

    Let’s examine a sample evidence-based practice paper addressing fall prevention through hourly rounding in medical-surgical units. This nursing paper example demonstrates how to write an evidence-based practice paper that integrates research findings into clinical nursing practice.

    Title: Implementation of an Evidence-Based Hourly Rounding Protocol to Reduce Fall Rates in Medical-Surgical Units

    Introduction

    Falls in hospitalized patients represent a significant patient safety concern across healthcare settings. These adverse events affect approximately 700,000-1,000,000 patients annually in the United States, resulting in prolonged hospital stays, increased healthcare costs exceeding $50 billion annually, and substantial patient morbidity and mortality (Joint Commission, 2023). In medical-surgical units, where patients often have multiple risk factors including medication effects, unfamiliar environments, and varying levels of mobility impairment, fall rates can be particularly high. Evidence-based nursing interventions aimed at fall prevention have become a priority focus for quality improvement in the current healthcare landscape.

    The purpose of this paper is to examine the implementation of evidence-based hourly rounding as a structured approach to reduce fall rates in medical-surgical units. This paper will review available research evidence on hourly rounding protocols, synthesize the findings, and propose an implementation plan for integrating this evidence-based approach into clinical practice. By exploring this evidence-based practice nursing research topic, this paper aims to contribute to improved patient care and safety outcomes.

    PICOT Question: “In adult patients on medical-surgical units (P), how does the implementation of a standardized hourly rounding protocol (I) compared to routine care checks (C) affect inpatient fall rates (O) over a three-month period (T)?”

    Literature Search Strategy

    A comprehensive literature search was conducted using multiple electronic databases including CINAHL, PubMed, Medline, and the Cochrane Library. The search utilized the following keywords in various combinations: “hourly rounding,” “intentional rounding,” “nursing rounds,” “falls,” “fall prevention,” “inpatient,” “hospital,” and “medical-surgical.” To ensure relevance and currency of evidence, the search was limited to peer-reviewed research articles published in English within the past seven years (2016-2023).

    The initial search yielded 76 potential articles. After applying inclusion criteria (original research, adult inpatient setting, focus on hourly rounding and fall prevention) and exclusion criteria (pediatric settings, long-term care facilities, emergency departments, and non-research articles), 18 articles remained for full-text review. Following detailed evaluation for methodological quality and relevance to the PICOT question, 10 studies were selected for inclusion in this evidence-based practice research.

    Evidence Appraisal

    The selected studies were evaluated using the Johns Hopkins Nursing Evidence-Based Practice Rating Scale to assess quality. The final collection included three Level I randomized controlled trials, four Level II quasi-experimental studies, and three Level III observational studies. Quality ratings ranged from A (high quality) to B (good quality).

    Two of the randomized controlled trials (Mitchell et al., 2019; Garcia et al., 2022) demonstrated strong methodology with adequate sample sizes, clear intervention protocols, and robust statistical analysis. The quasi-experimental studies provided valuable before-and-after data from real clinical settings, though they lacked randomization. The observational studies offered important contextual insights into implementation challenges and facilitators for hourly rounding programs.

    The evidence consistently showed that structured hourly rounding protocols had positive effects on fall rates, though the magnitude of effect varied across studies. This variation appeared to correlate with implementation fidelity and staff engagement, highlighting the importance of these factors in successful evidence-based practice implementation.

    Synthesis of Evidence

    Analysis of the research evidence revealed several key findings regarding hourly rounding as an evidence-based fall prevention strategy:

    1. Efficacy: Eight of the ten studies reported statistically significant reductions in fall rates following implementation of structured hourly rounding protocols. Reduction percentages ranged from 18% to 55%, with a mean reduction of approximately 35% across studies (Mitchell et al., 2019; Harris, 2020; Chen et al., 2021; Garcia et al., 2022). This suggests strong evidence supporting the effectiveness of hourly rounding in fall prevention.
    2. Protocol Components: The studies that demonstrated the most substantial reductions in falls shared common elements in their hourly rounding protocols. These key components included:
      • Systematic assessment of the “4 Ps”: Pain, Position, Personal needs, and Placement of items
      • Documented completion of rounds
      • Consistent messaging to patients about when staff would return
      • Structured handoff between shifts regarding high-fall-risk patients
    3. Implementation Factors: Studies identified several factors influencing successful implementation, including leadership support, staff education, audit and feedback mechanisms, and integration into existing workflows. Garcia et al. (2022) found that units with designated “champion nurses” had 27% better protocol adherence and greater fall reductions than units without champions.
    4. Sustainability: Three longitudinal studies tracked outcomes beyond the initial implementation period. Harris (2020) demonstrated sustained reductions in fall rates over 18 months, while Chen et al. (2021) found some regression toward baseline rates after 12 months, suggesting the need for ongoing reinforcement of hourly rounding practices.
    5. Secondary Benefits: Beyond fall reduction, several studies reported additional positive outcomes associated with hourly rounding, including reduced call light use (25-43% reduction), improved patient satisfaction scores (8-15% improvement), and decreased pressure injury incidence (Davies, 2018; Mitchell et al., 2019).

    The synthesis of this relevant evidence provides a strong base for recommending hourly rounding as an evidence-based intervention for fall prevention in medical-surgical units. The best available evidence clearly supports structured approaches that incorporate specific assessment components and implementation strategies to achieve optimal outcomes.

    Practice Recommendations

    Based on the current best evidence reviewed, the following evidence-based practice recommendations are proposed for implementing hourly rounding to reduce falls in medical-surgical units:

    1. Implement a standardized hourly rounding protocol that includes:
      • Structured assessment of the “4 Ps” (Pain, Position, Personal needs, Placement of items)
      • Documentation of completed rounds in the electronic health record
      • Clear communication with patients about timing of return visits
      • Specific attention to fall risk factors identified through validated fall risk assessment tools
    2. Develop a comprehensive staff education program that includes:
      • Evidence supporting hourly rounding for fall prevention
      • Specific protocol steps and documentation requirements
      • Role-playing exercises to practice patient interactions
      • Strategies for integration into existing workflows
    3. Establish an implementation infrastructure with:
      • Unit-based champion nurses to support the change in practice
      • Regular audit and feedback mechanisms to monitor compliance
      • Visual cues in patient rooms and at nursing stations to prompt hourly rounds
      • Integration of rounding documentation into existing electronic health record systems
    4. Create a sustainability plan that includes:
      • Quarterly refresher education sessions
      • Recognition of high-performing staff and units
      • Regular sharing of outcome data with frontline staff
      • Integration of hourly rounding performance into unit quality metrics

    These recommendations represent the best evidence-based practice approach for implementing hourly rounding to reduce falls, based on synthesis of current research evidence integrated with clinical expertise.

    Implementation Plan

    The following implementation plan outlines the strategy for integrating evidence-based hourly rounding into clinical nursing practice on medical-surgical units:

    Phase 1: Preparation (Weeks 1-4)

    • Form an interdisciplinary implementation team including nursing leadership, staff nurses, quality improvement specialists, and informatics personnel
    • Customize the hourly rounding protocol based on evidence and unit-specific needs
    • Develop documentation tools within the electronic health record
    • Create educational materials including competency checklists, pocket guides, and visual reminders
    • Identify and train unit champions (2-3 per shift)
    • Collect baseline data on fall rates, call light usage, and patient satisfaction

    Phase 2: Education and Training (Weeks 5-6)

    • Conduct mandatory education sessions for all nursing staff using multiple modalities (in-person, online modules, simulation)
    • Hold special training sessions for unit champions focused on coaching and implementation support strategies
    • Educate ancillary staff and other departments on the new protocol and their supporting roles
    • Conduct pre-implementation readiness assessment

    Phase 3: Implementation (Weeks 7-18)

    • Begin hourly rounding with intensive support from unit champions and leadership
    • Conduct daily huddles to address implementation challenges
    • Perform weekly audits of protocol adherence through direct observation and documentation review
    • Provide real-time feedback and coaching to staff
    • Post weekly compliance data and preliminary outcome measures
    • Adjust processes as needed based on feedback and observed barriers

    Phase 4: Evaluation and Sustainability (Weeks 19-24)

    • Analyze data on fall rates, compliance rates, call light usage, and patient satisfaction
    • Compare outcomes to baseline and benchmarks
    • Identify factors associated with successful implementation
    • Develop long-term sustainability plan including regular refreshers and new staff orientation
    • Share outcomes with organizational leadership and consider spread to other units

    This implementation plan addresses potential barriers such as time constraints, competing priorities, and documentation burden by providing adequate preparation, training, and ongoing support. The phased approach allows for adaptation based on feedback and early results, maximizing the likelihood of successful integration of evidence-based practice into routine nursing care.

    Evidence-Based Practice Paper Example

    Evaluation Plan

    The effectiveness of the hourly rounding implementation will be evaluated using a comprehensive set of measures:

    Primary Outcome Measures:

    • Fall rates per 1,000 patient days (monthly)
    • Fall with injury rates per 1,000 patient days (monthly)
    • Percent compliance with hourly rounding protocol (weekly, based on documentation audits and direct observation)

    Secondary Outcome Measures:

    • Call light usage (frequency per patient day)
    • Patient satisfaction scores related to nursing responsiveness
    • Staff perceptions of feasibility and effectiveness (survey at 1 and 3 months post-implementation)
    • Time spent on rounding activities (random time samples)

    Process Measures:

    • Percentage of staff completing education program
    • Number of audit-feedback cycles completed
    • Documentation compliance rates
    • Unit champion activity logs

    Data will be collected continuously throughout the implementation period and analyzed monthly by the implementation team. Statistical analysis will include pre-post comparisons using appropriate tests (t-tests, chi-square, or non-parametric alternatives as indicated by data distribution).

    Success will be defined as:

    • ≥25% reduction in fall rates compared to baseline
    • ≥80% compliance with hourly rounding protocol
    • No significant increase in nursing workload measures
    • Maintenance of or improvement in patient satisfaction scores

    Results will be disseminated to staff via unit huddles, quality boards, and formal presentations. Findings will also be shared with organizational leadership and considered for presentation at professional conferences or publication to contribute to the broader evidence base on implementation of evidence-based practice in nursing.

    Key Components of Successful Evidence-Based Practice Papers

    What makes an evidence-based practice paper effective? Based on the example above, several elements stand out:

    Clear Clinical Focus and Research Topics

    Successful EBP papers address specific, relevant clinical questions that nurses encounter in practice. Choosing focused nursing topics helps bridge the gap between academic exercise and clinical application. The research question should be precise and answerable through evidence review.

    Strong PICOT Question Formulation

    A well-formulated PICOT question guides the entire paper and ensures that the literature search yields relevant research evidence. It serves as the foundation for all subsequent sections of your evidence-based practice essay.

    Comprehensive Literature Search Strategy

    Effective papers demonstrate thorough searching of multiple databases and careful selection of high-quality, recent research. They explicitly describe how evidence available was identified, screened, and selected for inclusion.

    Critical Appraisal Skills

    The ability to evaluate research quality is central to evidence-based practice. Strong papers show nuanced understanding of research methods and limitations, comparing the strengths and weaknesses of different types of evidence.

    Evidence-Based Approach to Implementation

    Papers that move beyond theory to address real-world implementation challenges demonstrate a deeper understanding of evidence-based practice in nursing. Considering barriers, facilitators, and specific strategies for implementing change shows practical knowledge of clinical settings.

    Integration of Evidence with Clinical Expertise

    The best evidence-based practice involves combining research findings with clinical expertise and judgment. Papers should demonstrate how evidence in making decisions is balanced with practical clinical considerations and patient preferences.

    Common Challenges in Writing Evidence-Based Practice Papers

    Nursing students often encounter several challenges when writing an evidence-based practice paper or nursing essay:

    Finding Relevant Research Evidence

    Sometimes the available evidence on a specific nursing practice is limited or of poor quality. Students must learn to broaden search terms appropriately without losing focus. This process requires understanding how to navigate nursing research databases effectively.

    Evaluating Contradictory Evidence

    When studies show conflicting results, students must learn to weigh evidence based on study design, sample size, and methodological rigor. This critical thinking skill is essential for determining what constitutes best evidence for practice.

    Translating Research to Clinical Practice

    Bridging the gap between research findings and practical nursing interventions requires critical thinking and creativity. Students must learn how to use evidence-based practice in real clinical nursing scenarios, not just theoretical situations.

    Addressing Implementation Barriers

    Realistic assessment of potential barriers to implementing evidence-based practice shows sophistication in understanding clinical settings. Successful papers acknowledge these challenges and propose strategies to overcome them.

    Tools and Resources for Evidence-Based Practice Nursing Research

    Several models and frameworks can guide the development of evidence-based practice papers and facilitate the implementation of evidence-based practice in nursing:

    1. The Johns Hopkins Nursing Evidence-Based Practice Model (JHNEBP): Provides a systematic approach to identifying, evaluating, and implementing research evidence in nursing practice.
    2. The ACE Star Model: Outlines five stages of knowledge transformation, from discovery to implementation of evidence-based practice.
    3. The Iowa Model: Offers a practical guide for implementing evidence-based practice changes in clinical settings, with particular attention to organizational factors.
    4. Evidence-Based Practice Guidelines: Various organizations publish evidence-based guidelines that synthesize current best evidence to guide clinical decision making:
      • The Joanna Briggs Institute
      • The Registered Nurses’ Association of Ontario (RNAO)
      • The Agency for Healthcare Research and Quality (AHRQ)
      • The National Institute for Health and Care Excellence (NICE)

    These resources provide valuable support for nursing students learning how to write an evidence-based practice paper and for practicing nurses seeking to implement evidence-based nursing interventions.

    Frequently Asked Questions

    How does evidence-based practice differ from research utilization in nursing?

    While related concepts, evidence-based practice is broader than research utilization. Research utilization focuses specifically on translating research findings into practice, while evidence-based practice integrates not only research evidence but also clinical expertise and patient preferences. EBP is a comprehensive decision-making approach that considers multiple forms of evidence beyond just research studies, making it more holistic in its application to clinical nursing.

    What are some examples of evidence-based practice models used in nursing education?

    Several models guide evidence-based nursing practice, including the Johns Hopkins Nursing EBP Model, the Iowa Model, the ACE Star Model, and the Stetler Model. Each provides a structured framework for identifying clinical questions, gathering and evaluating evidence, implementing changes, and assessing outcomes. These models offer systematic approaches to the integration of evidence-based practice in nursing and help students learn how to write evidence-based practice papers effectively.

    How can nursing students improve their skills in finding relevant research evidence?

    Improving research skills requires practice with database searching techniques, including using Boolean operators, applying filters effectively, and developing precise PICOT questions. University libraries often offer workshops specifically for nursing students on evidence-based literature searches. Additionally, working with a librarian who specializes in health sciences can significantly enhance search effectiveness and efficiency when preparing an evidence-based practice paper. Regular practice with different nursing topics will build confidence in finding evidence available for various clinical questions.

    What role do advanced practice nurses play in promoting evidence-based practice in clinical settings?

    Advanced practice nurses often serve as leaders in implementing evidence-based practice within healthcare organizations. They may conduct needs assessments, evaluate available evidence, develop evidence-based guidelines, lead implementation teams, and measure outcomes. Their advanced education equips them to bridge the gap between research and clinical practice, mentor other nurses in EBP methods, and advocate for system-level changes that support evidence-based care delivery. By modeling the use of evidence-based practice, they help create a culture that values evidence-informed clinical decisions throughout the nursing profession.

  • Journal Article Critique Sample and Writing Tips

    A journal article critique requires you to critically read a piece of research and identify and evaluate the strengths and weaknesses of the article. This comprehensive guide provides nursing students with everything needed to craft an outstanding critique, including a journal article critique sample that demonstrates critical thinking and scholarly engagement. Whether you’re facing your first article critique assignment or looking to refine your approach, this guide offers practical examples, methodology insights, and structured frameworks to help you excel.

    What Is an Article Critique?

    An article critique is a detailed analysis and evaluation of a scholarly work that requires careful examination of the author’s main arguments, research methods, and conclusions. Unlike a simple summary, an article critique demands that you engage critically with the text, identifying both its strengths and weaknesses while providing constructive feedback based on evidence.

    For nursing students, learning how to write an article critique effectively is particularly valuable as it develops the analytical skills necessary for evidence-based practice. When you critique an article, you’re essentially assessing its validity, reliability, and relevance to clinical practice—skills that directly translate to patient care. A thorough article critique involves evaluating its content from multiple perspectives while considering the broader implications for nursing practice.

    Journal Article Critique Sample

    The Importance of Learning How to Critique a Journal Article in Nursing Education

    Journal article critique skills are fundamental to nursing practice for several reasons:

    1. They help you evaluate research before applying findings to patient care
    2. They develop your critical eye for methodological flaws and bias
    3. They enhance your analytical thinking and academic writing abilities
    4. They prepare you for contributing to nursing research and publishing

    A well-executed journal article critique demonstrates your ability to think independently about complex healthcare issues while engaging with the broader research context. This skill is particularly valuable in a field where practices are constantly evolving based on new evidence.

    Essential Components of an Effective Article Critique Example

    Before examining journal article critique samples, let’s break down the key components that every critique should include:

    1. Introduction

    The introduction of your article critique should:

    • Identify the article being critiqued (title, author, publication details)
    • Provide a brief summary of the article’s main points
    • Present your thesis statement regarding your overall assessment
    • Outline the structure of your critique

    2. Summary

    A concise summary of the article includes:

    • The research question or purpose
    • Methodology used
    • Key findings
    • Main conclusions

    Remember that while you need to summarize, this section should be relatively brief—the focus of your journal article critique is on analysis, not summary.

    3. Critical Analysis

    This is where you analyze and evaluate the article’s content, including:

    • Methodology: Assess the research methods employed, sample size appropriateness, data collection methods, and analytical techniques.
    • Literature Review: Evaluate how well the author contextualizes their research within relevant literature.
    • Results and Discussion: Examine how data analysis was conducted and whether conclusions are justified by the evidence.
    • Strengths and Weaknesses: Highlight both positive aspects and areas for improvement.

    4. Conclusion

    Your conclusion should:

    • Summarize your main arguments
    • Restate your overall assessment
    • Suggest implications for nursing practice
    • Propose directions for future research

    How to Write an Article Critique: Step-by-Step Writing Process

    Follow these steps to craft a well-structured journal article critique:

    Step 1: Read the Article Thoroughly – First Step to Critique an Article

    Before you can critique an article effectively, you must first understand it completely:

    • Read the article multiple times
    • Take detailed notes
    • Identify the main arguments and key points
    • Understand the methodology and results

    Step 2: Analyze the Content and Identify Key Points

    Once you’ve thoroughly read the article:

    • Evaluate the clarity and coherence of the author’s arguments
    • Assess the quality and relevance of evidence used to support the claims
    • Examine the methodology for rigor and appropriateness
    • Consider potential sources of bias
    • Explore the key points of the article and how they relate to the overall purpose

    Step 3: Organize Your Thoughts

    Before writing, outline your critique:

    • Note specific strengths of the article
    • Identify areas where the article requires improvement
    • Gather evidence from the article to support your assessments
    • Plan how to structure your critique
    • Formulate suggestions for improvement that would strengthen the original article

    Step 4: Writing Article Critique – Putting It All Together

    When crafting an article critique:

    • Follow academic writing conventions
    • Use a formal, scholarly tone
    • Remain objective and balanced
    • Provide specific examples from the text to support your points
    • Focus on the core ideas rather than minor issues
    • Clearly articulate the thesis and purpose of the original article
    • Highlight the strengths as well as limitations of the research
    • Assess how well the article achieves its stated objectives

    Step 5: Review and Refine

    Before submitting:

    • Ensure your critique is well-structured and easy to follow
    • Check that your analysis is balanced, noting both strengths and weaknesses
    • Verify that your critique follows the required citation style (often APA)
    • Proofread carefully for clarity and conciseness
    How to Write a Journal Article Critique Sample

    Journal Article Critique Samples

    Example 1: Critique Example of a Quantitative Study

    The following journal article critique example demonstrates how to effectively analyze a nursing research article:

    Critique of “Impact of Nurse-Led Education on Diabetes Self-Management”

    This critique examines a research article by Johnson et al. (2022) published in the Journal of Advanced Nursing. The study investigates the effectiveness of nurse-led educational interventions on diabetes self-management outcomes.

    Summary: The authors conducted a randomized controlled trial with 120 type 2 diabetes patients, comparing standard care with an enhanced nurse-led educational program. The intervention group showed statistically significant improvements in HbA1c levels, self-efficacy scores, and adherence to self-management behaviors after six months.

    Methodology Analysis: The research methods employed in this study demonstrate several strengths. The randomized design reduces selection bias, while the sample size (n=120) provides adequate statistical power based on the authors’ calculations. However, the single-center nature of the study limits generalizability. Additionally, the researchers relied heavily on self-reported measures for several outcomes, introducing potential reporting bias.

    Strengths: The article presents a clear theoretical framework linking the intervention to expected outcomes. The authors provide constructive feedback on previous studies’ limitations and explicitly address how their methodology improves upon past research. The data analysis uses appropriate statistical techniques, with results clearly presented in well-organized tables.

    Weaknesses: The study lacks long-term follow-up beyond six months, limiting understanding of the intervention’s sustained impact. The discussion inadequately addresses potential confounding variables such as participants’ educational backgrounds. There is insufficient consideration of how the findings might apply to diverse cultural contexts.

    Overall Assessment: This article makes a valuable contribution to nursing knowledge regarding educational interventions for diabetes patients. Despite methodological limitations, the findings offer practical implications for clinical practice. Future research should focus on longer-term outcomes and broader population diversity.

    Example 2: Critique Journal Article for Qualitative Research Study

    Critique of “Nurses’ Experiences of Caring for COVID-19 Patients: A Phenomenological Study”

    This critique evaluates a qualitative study by Martinez and Lee (2023) published in the International Journal of Nursing Studies that explores nurses’ lived experiences during the COVID-19 pandemic.

    Summary: Using phenomenological methodology, the researchers conducted in-depth interviews with 15 nurses who worked directly with COVID-19 patients during the first wave of the pandemic. The analysis identified four major themes: emotional burden, professional duty, institutional support, and personal growth.

    Methodology Analysis: The phenomenological approach is appropriate for exploring lived experiences, aligning well with the research question. The authors provide a detailed explanation of their data collection and analysis process, enhancing methodological transparency. However, while the sample size is consistent with qualitative research norms, participants were recruited from a single hospital system, potentially limiting the range of experiences captured.

    Strengths: The article provides rich, detailed narratives that effectively communicate nurses’ experiences. The authors demonstrate reflexivity by acknowledging their positionality as nurse researchers. The findings are thoughtfully contextualized within existing literature on healthcare worker experiences during crises.

    Weaknesses: The study would benefit from greater demographic diversity among participants, as 12 of the 15 nurses identified as female and Caucasian. The authors do not adequately address how their own experiences may have influenced data interpretation. Additionally, the discussion of implications for practice lacks specific, actionable recommendations.

    Conclusion: Despite its limitations, this article offers valuable insights into the psychological impact of pandemic care on nurses. The study highlights the need for enhanced institutional support mechanisms. Future research should explore these experiences across more diverse nursing populations and healthcare settings.

    Example 3: Article Critique Example for Mixed Methods

    Critique of “Simulation-Based Learning in Undergraduate Nursing Education: A Mixed-Methods Evaluation”

    This critique examines a mixed-methods study by Williams and Thompson (2021) published in Nurse Education Today, evaluating the effectiveness of simulation-based learning for developing clinical competencies.

    Summary: The researchers utilized a sequential explanatory design, first collecting quantitative data from 85 nursing students using pre-post competency assessments, followed by qualitative data through four focus groups. Results indicated statistically significant improvements in clinical competency scores, with qualitative findings revealing themes of increased confidence, communication skills, and clinical reasoning.

    Methodology Analysis: The mixed-methods approach strengthens the study by providing both objective measures of competency gains and subjective experiences of learning. The sequential design is logical, with qualitative data helping to explain quantitative findings. However, the researchers provide limited justification for their sample size in the quantitative phase, raising questions about statistical power.

    Strengths: The article effectively integrates quantitative and qualitative data, creating a more comprehensive understanding than either method alone could provide. The authors clearly describe their simulation scenarios, enhancing replicability. The discussion thoughtfully considers how different learning styles may influence simulation effectiveness.

    Weaknesses: The study lacks a control group, making it difficult to attribute improvements specifically to simulation rather than other educational experiences. The researchers do not adequately address potential bias in self-reported confidence measures. Additionally, the six-week timeframe is insufficient to evaluate long-term retention of skills.

    Overall Evaluation: This article makes an important contribution to nursing education literature by providing both quantitative evidence and qualitative insights into simulation effectiveness. Despite methodological limitations, it offers practical guidance for educators. Future research should incorporate control groups and longitudinal designs to strengthen evidence quality.

    FAQs About Journal Article Critique

    How do I differentiate between a literature review and an article critique?

    While a literature review synthesizes information from multiple sources to establish what is known about a topic, an article critique paper focuses on thoroughly evaluating a single article’s quality, validity, and significance, examining its methodology, evidence, and conclusions with a critical eye.

    What citation style should I use when writing a journal article critique?

    Most nursing programs require APA (American Psychological Association) citation style for academic writing, including article critiques, though you should always verify your specific program’s requirements since citation style preferences may vary between institutions.

    How can I effectively evaluate the research context of a journal article?

    To evaluate research context effectively, examine how the article positions itself within existing literature, consider whether the author establishes a clear research gap, assess if the theoretical framework aligns with the research question, and determine whether the study’s justification is compelling and relevant to current nursing practice.

    What are the essential tips for analyzing and evaluating quantitative versus qualitative research articles?

    When critiquing quantitative research, focus on statistical methods, sample size adequacy, validity of measurements, and generalizability; for qualitative research, examine trustworthiness criteria (credibility, transferability, dependability, confirmability), appropriateness of the chosen methodology, richness of participant descriptions, and reflexivity of the researchers.

  • How to Write a Personal Philosophy of Nursing Paper: Guide and Examples

    Introduction

    As a nursing student preparing to enter the healthcare field, one of the most reflective and meaningful assignments you’ll encounter is writing your personal philosophy of nursing paper. This assignment isn’t just another academic exercise—it’s an opportunity to deeply consider what being a nurse means to you and how you’ll approach patient care throughout your nursing career. Below is a detailed guide on how to write a personal philosophy of nursing with examples for a better illustration.

    What Is a Personal Philosophy of Nursing?

    A personal philosophy of nursing represents your individual beliefs, values, and principles that will guide your nursing practice. Every nurse develops their unique philosophy based on their experiences, education, and personal values. Your nursing philosophy statement serves as a professional compass that will direct your decisions, interactions, and approach to nursing throughout your career.

    When you write a personal philosophy of nursing paper, you’re articulating your fundamental understanding of what nursing is and what it means to be a nurse. This exercise helps you connect theory with practice and clarifies how you’ll embody the nursing profession’s core values.

    Importance of a Personal Philosophy of Nursing Paper

    Developing a personal philosophy of nursing isn’t just an academic requirement—it’s a foundational process that shapes your identity as a nurse. Your personal nursing philosophy paper will help you:

    1. Clarify your understanding of the nursing profession
    2. Establish your approach to nursing practice
    3. Define your personal values within nursing
    4. Set meaningful career goals
    5. Create a framework for ethical decision-making
    6. Guide your professional development

    As you progress in your nursing career, your philosophy may evolve, but having a clear foundation helps you strive for excellence in patient care while staying true to your core beliefs.

    Key Elements to Include in Your Personal Philosophy of Nursing Paper

    1. Your Personal Definition of Nursing

    Begin your paper by articulating what nursing means to you personally. Consider questions like:

    • What does being a nurse mean to me?
    • Is nursing primarily an art, a science, or both?
    • What aspect of nursing resonates most with my personal values?

    2. Your Core Values and Beliefs

    Identify the fundamental values that inform your nursing philosophy. Common values in nursing include:

    • Compassion
    • Integrity
    • Excellence
    • Advocacy
    • Holistic care
    • Wellness
    • Empowerment
    • Ethics

    Explain how these values will influence your nursing practice and patient care approach.

    3. Theoretical Influences

    Reference nursing theories that align with your personal philosophy. Famous nursing theorists like Florence Nightingale, Jean Watson, or Patricia Benner might inform your perspective. Explain how these nursing theories connect with your personal definition of nursing and your approach to patient care.

    4. Your View on the Nurse-Patient Relationship

    Describe how you envision the ideal relationship between nurse and patient. Consider:

    • How will you deliver care to your patients?
    • How will you advocate for your patients within the healthcare system?
    • How will you address issues like socioeconomic disparity in healthcare settings?

    5. Professional Goals and Commitment to Growth

    Outline your commitment to continuous learning and professional development. Discuss how you plan to:

    • Stay current with new research
    • Enhance your nursing skills
    • Pursue certification or advanced practice
    • Contribute to the quality of care in your workplace
    • Potentially serve as a mentor to future nurses
    Key Elements to Include in Your Personal Philosophy of Nursing Paper

    How to Structure Your Personal Philosophy of Nursing Paper

    Introduction

    Begin with a compelling introduction that outlines what a personal philosophy of nursing is and why it matters. Briefly mention your motivation for becoming a nurse and preview the main components of your philosophy.

    Body Paragraphs

    Organize the body of your paper around the key elements mentioned above. Each section should thoroughly explain one aspect of your nursing philosophy, supported by examples, relevant nursing theories, and personal insights.

    Conclusion

    Summarize your personal philosophy of nursing and reflect on how it will guide your nursing practice. Emphasize how your philosophy aligns with the broader mission of the nursing profession and how it will help you provide quality care throughout your career.

    Sample Personal Philosophy of Nursing Papers

    Example 1: Evidence-Based Practice Centered Philosophy

    My personal philosophy of nursing centers on the integration of evidence-based practice with compassionate patient care. As a nurse, I believe my primary responsibility is to deliver care that is both scientifically sound and emotionally supportive. This philosophy stems from my understanding that nursing is a dynamic and evolving profession within the modern healthcare landscape.

    I define nursing as the art and science of promoting health, preventing illness, and facilitating healing through evidence-based interventions delivered with compassion. My approach to nursing practice will always prioritize the latest research while recognizing each patient’s unique needs and circumstances.

    Florence Nightingale’s emphasis on the patient’s environment profoundly influences my philosophy. Like Nightingale, I believe creating a healing environment is essential for optimal patient outcomes. This means not only maintaining physical cleanliness and comfort but also fostering emotional safety and respecting cultural differences.

    In my nursing career, I will strive to build relationships with patients based on trust and mutual respect. I firmly believe that empowerment comes through education, so I will dedicate myself to helping patients understand their health conditions and treatment options. My ethics as a nurse will guide me to advocate for patients, especially those facing healthcare disparities due to socioeconomic factors.

    As I grow professionally, I commit to continuous learning and staying current with new research. I aspire to obtain specialty certification in critical care nursing and eventually contribute to nursing education as a clinical instructor. By embracing lifelong learning, I can ensure that my nursing skills remain relevant and effective in an ever-changing healthcare field.

    This personal philosophy of nursing will serve as my professional compass, helping me navigate challenges while staying true to my core values of evidence-based practice, compassionate care, and patient advocacy.

    Example 2: Holistic Care Centered Philosophy

    My personal nursing philosophy is rooted in holistic care that addresses the physical, emotional, spiritual, and social dimensions of every patient. I believe that the essence of nursing extends beyond administering medication or performing procedures—it encompasses understanding the whole person and their unique healthcare journey.

    To me, the definition of nursing encompasses both scientific competence and empathetic connection. As Jean Watson’s Theory of Human Caring suggests, nursing practice should balance technical expertise with authentic human relationships. This resonates deeply with my approach to patient care, as I view each interaction as an opportunity to make a positive impact.

    My personal values of integrity, compassion, and respect form the foundation of my nursing philosophy statement. When I care for patients, I strive to create an environment where patients feel heard, valued, and involved in their healthcare decisions. This philosophy recognizes that wellness encompasses more than the absence of disease—it includes emotional wellbeing and quality of life.

    Throughout my nursing school journey, I’ve observed how socioeconomic disparity affects healthcare outcomes. My personal philosophy of nursing includes a commitment to addressing these inequities through advocacy and culturally competent care. I believe that a nurse must recognize how factors beyond the clinical setting influence health and recovery.

    As a professional, I commit to evidence-based practices while acknowledging nursing is an art requiring intuition and personalized approaches. My nursing career goals include specializing in community health nursing, where I can work directly with underserved populations. Through continuous learning and openness to new research, I will grow professionally while maintaining my core commitment to holistic, patient-centered care.

    This personal philosophy will guide my clinical practice decisions, shape my interactions with colleagues in various healthcare settings, and remind me of my purpose when facing the inevitable challenges of the nursing profession.

    Tips for Writing an Outstanding Personal Philosophy of Nursing Paper

    1. Be authentic: Your philosophy should genuinely reflect your personal beliefs about nursing, not what you think others want to hear.
    2. Be specific: Avoid vague generalizations. Use concrete examples to illustrate your philosophy in action.
    3. Connect theory to practice: Show how nursing theories inform your practical approach to patient care.
    4. Consider diverse perspectives: Acknowledge how your philosophy addresses patients from different cultural backgrounds.
    5. Be reflective: Discuss how your personal experiences have shaped your philosophy of nursing.
    6. Look forward: Include how you anticipate your philosophy may evolve as you grow professionally.
    7. Use clear language: While this is an academic paper, aim for clarity and accessibility in your writing.

    Common Challenges When Writing Your Nursing Philosophy Paper

    Many nursing students find it challenging to articulate their personal philosophy of nursing. Some common difficulties include:

    • Being too abstract: Remember to ground your philosophy in practical applications
    • Confusing philosophy with goals: Your philosophy guides your goals but isn’t the same thing
    • Overreliance on quotes: While referencing famous nursing theorists is valuable, your own voice should dominate
    • Neglecting ethical dimensions: Be sure to address how ethics informs your approach to nursing

    Remember that developing your personal philosophy of nursing is a process. As you progress through nursing school and gain clinical experience, your philosophy will naturally deepen and become more nuanced.

    How Your Personal Philosophy Evolves Throughout Your Nursing Career

    Personal Philosophy of Nursing Paper

    Your personal philosophy of nursing paper written in nursing school represents your starting point. As you enter the nursing profession and gain experience in healthcare settings, you’ll likely revisit and refine your philosophy.

    New research, changing healthcare landscapes, mentorship experiences, and patient interactions will all contribute to the evolution of your nursing philosophy. This dynamic nature is healthy and reflects your growth as a nurse.

    Many nurses find it valuable to periodically review and update their personal philosophy statement throughout their career. This practice helps maintain alignment between your values and your daily nursing practice.

    Frequently Asked Questions

    How can I incorporate Florence Nightingale’s environmental theory into my nursing philosophy statement?

    You can reference Nightingale’s focus on the patient’s environment by discussing how you plan to create a healing environment through attention to physical surroundings, minimizing stressors, and promoting conditions that support natural healing processes. Emphasize how environmental factors influence patient outcomes in your philosophy.

    What are some examples of evidence-based practices I should mention in my personal nursing philosophy paper?

    When discussing evidence-based practices in your philosophy, you might reference your commitment to using validated assessment tools, implementing best-practice protocols for specific conditions, participating in quality improvement initiatives, and basing interventions on current clinical practicClinical Practice Guidelinese guidelines rather than tradition.

    How do modern healthcare technologies fit into a personal definition of nursing?

    In your personal definition of nursing, you can address how modern healthcare technologies complement rather than replace the human connection in nursing. Discuss how you’ll use technology as a tool to enhance care delivery while maintaining focus on the patient as a whole person, balancing technical competence with empathetic presence.

    What should nursing students include about mentorship and professional development in their philosophy?

    Include how you value mentorship relationships as both a recipient and eventually a provider of guidance in the nursing profession. Discuss your vision for continuous learning through formal education, certification programs, professional organizations, and how these will help you grow professionally while improving the quality of care you provide to patients.

  • Erickson Nursing Theory: Modeling and Role-Modeling

    Erickson nursing theory helps nurses care for their patients by recognizing each individual’s uniqueness, and focusing on the individual patient’s needs. This theory stands as one of the most influential frameworks in modern nursing practice, as it integrates psychosocial elements with clinical practice, offering a more complete perspective on patient needs and treatment plans.

    Evolution of the Erickson Nursing Theory

    The Erickson nursing theory emerged in the early 1980s when Helen Erickson, along with her colleagues, developed the Modeling and Role-Modeling paradigm. This nursing theory was influenced by several existing theoretical frameworks, including Erik Erikson’s psychosocial development theory, Abraham Maslow’s hierarchy of needs, and Jean Piaget’s cognitive development theory.

    Helen Erickson, not to be confused with Erik Erikson, created a theory of nursing that emphasized understanding the patient’s worldview as the foundation for effective nursing interventions. While Erik Erikson’s work on psychosocial development influenced Helen’s thinking, her nursing theory represents a distinct and comprehensive approach to patient care.

    The Erickson nursing theory recognizes that individuals have inherent wisdom about their health needs. This wisdom, coupled with the psychosocial factors affecting their health, forms the basis of the nurse-patient relationship and subsequent interventions.

    Erickson nursing theory

    Core Concepts of Erickson Nursing Theory

    At its heart, this theory consists of two main processes: modeling and role-modeling.

    Modeling in Erickson Nursing Theory

    Modeling involves understanding the patient’s worldview—their perspective on the world, health, illness, and treatment. This process requires nurses to set aside their own perspectives temporarily to truly grasp the patient’s unique model. Within thetheory, modeling is essential for establishing trust and building therapeutic relationships.

    The process involves collecting data about the client’s psychosocial history, current stressors, available resources, and their sense of self. Through careful assessment, nurses gain insight into how patients have navigated their stages of development and how these experiences influence their current health status.

    Role-Modeling in Erickson Nursing Theory

    Role-modeling, the second core process involves planning and implementing interventions based on the patient’s model. This process respects the patient’s perspective while helping them achieve their health goals.

    Role-modeling acknowledges that patients may experience various psychosocial crises as described in Erik Erikson’s developmental theory. For example, a patient struggling with mistrust due to negative healthcare experiences may require specific nursing interventions to build a sense of trust before other treatments can proceed effectively.

    Core Concepts of Erickson Nursing Theory
    Core Concepts of Erickson Nursing Theory

    Application of Erickson Nursing Theory in Clinical Settings

    The Erickson nursing theory offers practical guidance for nurses across various healthcare settings. By applying this theory, nursing students can develop a more personalized and effective approach to patient care.

    Assessment in Erickson Nursing Theory

    Assessment using the this theory goes beyond physical examination to include psychosocial factors. Nurses collect data about:

    • The patient’s model of the world
    • Their developmental stage and associated tasks
    • Available resources and coping mechanisms
    • Basic need status (based on Maslow’s hierarchy)
    • Growth and development status

    This comprehensive assessment helps nurses understand how developmental stages and psychosocial factors influence the patient’s health experience.

    The Nursing Process Through Erickson’s Lens

    The nursing process takes on special significance within the Erickson nursing theory. Each step is enhanced by considering the patient’s unique model:

    1. Assessment: Gathering data about the patient’s model of the world
    2. Diagnosis: Identifying health problems from the patient’s perspective
    3. Planning: Developing interventions based on the patient’s strengths and resources
    4. Implementation: Providing care that respects the patient’s worldview
    5. Evaluation: Measuring outcomes meaningful to the patient

    This problem-oriented approach to documentation ensures that care remains patient-centered while meeting professional standards.

    Building Trust Through Erickson Nursing Theory

    Trust forms the cornerstone of the nurse-patient relationship in Erickson nursing theory. By validating the patient’s experiences and perspectives, nurses establish themselves as reliable allies in the healing process.

    For patients who have developed mistrust due to negative healthcare experiences or as a result of their developmental stages, nurses applying Erickson nursing theory take specific steps to build a sense of trust:

    • Maintaining consistency in care
    • Following through on commitments
    • Advocating for patient needs
    • Providing honest information
    • Respecting the patient’s model of the world

    Supporting Autonomy and Self-Care

    The Erickson nursing theory emphasizes supporting patient autonomy by recognizing their inherent wisdom about their health needs. Nurses facilitate self-care rather than creating dependency, helping patients develop a stronger sense of self and control over their health.

    This approach is particularly important for patients experiencing developmental crises related to autonomy versus shame and doubt. By involving patients in their care decisions, nurses promote healing while strengthening the patient’s sense of personal control.

    Erickson Nursing Theory and Erik Erikson’s Eight Stages

    While distinct, the Erickson nursing theory incorporates elements from Erik Erikson’s eight stages of psychosocial development. Understanding these stages helps nurses recognize how developmental challenges might affect a patient’s response to illness and treatment.

    Erickson Nursing Theory Applications
    Erickson Nursing Theory Applications

    Stage 1: Trust vs. Mistrust

    In the first stage of Erik Erikson’s theory, infants develop a sense of trust or mistrust based on the consistency of care they receive. The Erickson theory applies this concept to the nurse-patient relationship, emphasizing that consistent, reliable nursing care builds a foundation of trust essential for healing.

    For nursing students, recognizing signs of mistrust in patients can guide their approach to establishing therapeutic relationships, particularly with patients who have had negative healthcare experiences.

    Autonomy vs. Shame and Doubt

    Erik Erikson’s second stage focuses on developing autonomy versus experiencing shame and doubt. In Erickson theory, respecting patient autonomy is paramount. Nurses must balance providing necessary care while supporting the patient’s sense of personal control over their health decisions.

    When working with patients struggling with shame and doubt about their health condition, nurses applying Erickson nursing theory create environments that foster autonomy and self-efficacy.

    Initiative vs. Guilt

    During the initiative versus guilt stage, children develop a sense of purpose. Within the context of Erickson nursing theory, nurses help patients regain their sense of purpose when illness disrupts their normal life roles and responsibilities.

    Industry vs. Feelings of Inferiority

    In this stage of psychosocial development, individuals develop competence or struggle with feelings of inferiority. The Erickson nursing theory guides nurses to recognize how illness may trigger these feelings of inferiority and implement interventions that highlight patient strengths and capabilities.

    Identity vs. Role Confusion

    Adolescents develop a sense of identity or experience role confusion during this critical stage. The Erickson nursing theory acknowledges how illness can disrupt one’s sense of identity, particularly for younger patients. Nursing interventions often focus on helping patients maintain or reclaim their sense of self during treatment.

    Intimacy vs. Isolation

    Young adults seek to form committed relationships and achieve intimacy or risk isolation. The Erickson nursing theory recognizes the importance of maintaining social connections during illness and may incorporate support for intimacy needs in the care plan.

    Generativity vs. Stagnation

    Middle-aged adults focus on generativity—making meaningful contributions to society—or face stagnation. The Erickson nursing theory acknowledges patients’ needs to create or nurture things even during illness, incorporating this understanding into holistic care plans.

    Ego Integrity vs. Despair

    In late adulthood, individuals reflect on their lives and either achieve ego integrity or experience despair. When working with older adults, the Erickson nursing theory guides nurses to support patients in finding meaning in their life experiences, including their health challenges.

    Erickson Nursing Theory vs. Other Nursing Theories

    To fully appreciate the Erickson nursing theory, nursing students should understand how it compares to other major nursing frameworks:

    Erickson Theory vs. Maslow’s Theory

    While Maslow’s theory focuses on a hierarchy of needs, the Erickson nursing theory incorporates this hierarchy while emphasizing the patient’s unique perception of those needs. Erickson nursing theory recognizes that patients prioritize needs differently based on their unique worldviews.

    Erickson Theory vs. Caritative Theory

    The caritative approach to nursing emphasizes love and charity as central to care. The Erickson nursing theory shares this compassionate foundation but adds the specific processes of modeling and role-modeling to guide nursing practice.

    Erickson Theory vs. Cognitive Development Theories

    While cognitive development theories like Piaget’s focus on intellectual growth, the Erickson nursing theory incorporates these insights within a broader framework that includes emotional and social development. This comprehensive view guides nurses in addressing the whole person rather than isolated aspects.

    Challenges in Applying Erickson Nursing Theory

    While powerful, the Erickson nursing theory presents certain challenges for nursing students and practitioners:

    1. Time constraints in busy healthcare settings can make thorough modeling difficult
    2. Organizational policies may not always align with the individualized approach
    3. Some patients may be unable or unwilling to share their worldview
    4. Balancing the patient’s model with evidence-based practice requires skill

    Despite these challenges, the benefits of applying Erickson nursing theory often outweigh the difficulties, leading to more effective and satisfying nurse-patient relationships.

    Frequently Asked Questions about Erickson Nursing Theory

    How does physical therapy relate to Erickson nursing theory in patient care?

    Physical therapy integrates well with Erickson nursing theory by focusing on the patient’s individual needs and goals. Physical therapists, like nurses, using Erickson’s approach, create a personalized treatment plan based on the patient’s unique circumstances. A comprehensive physical therapy SOAP note documents the patient’s progress through subjective reports, objective measurements, assessment findings, and planned interventions, aligning with the holistic assessment valued in Erickson nursing theory.

    What role does a SOAP note play in documenting care based on Erickson nursing theory?

    A SOAP note serves as an essential documentation tool when applying Erickson nursing theory. The subjective section captures the patient’s perspective—a core element of modeling in Erickson’s approach. The objective section documents measurable findings, while the assessment integrates these findings with the patient’s psychosocial context. The plan portion outlines interventions that respect the patient’s worldview, creating a concise yet comprehensive record of patient-centered care.

    How can manual therapy techniques be incorporated into care guided by Erickson nursing theory?

    Manual therapy techniques can be effectively incorporated into care guided by Erickson nursing theory by tailoring the approach to the patient’s unique needs and preferences. When a physical therapist applies manual therapy techniques, including soft tissue mobilization, they consider not just the physical condition but also the patient’s comfort level, past experiences, and health beliefs—all essential elements in Erickson’s modeling process. This personalized approach enhances both the effectiveness of the intervention and the therapeutic relationship.

    How does Erickson nursing theory address a patient’s range of motion limitations?

    Erickson nursing theory addresses a patient’s range of motion limitations by considering both physical and psychosocial factors. Nurses using this theory recognize that limited flexion or movement affects not only physical function but also the patient’s sense of autonomy and self-concept. When developing a home exercise program to improve motion, the nurse considers the patient’s developmental stage, coping resources, and personal goals, creating an exercise program that strengthens both the body and the patient’s sense of control over their health journey.

  • Dorothy Johnson Behavioral System Model

    Dorothy Johnson Behavioral System Model

    Dorothy E. Johnson, a renowned nursing theorist, was born on August 21, 1919, in Savannah, Georgia. Her contributions to the field of nursing, particularly through Johnson Behavioral System Model, emphasize the intricate relationship between nursing care and the behavioral functions of individuals, promoting health and balance. Johnson’s innovative approach transformed nursing practice by advocating for the integration of scientific principles with the art of nursing. This model has become a cornerstone in understanding human behavior in healthcare settings, making it a pivotal component in contemporary nursing education and practice. Johnson’s legacy is underscored by her distinguished career, during which she introduced essential concepts such as nursing diagnosis and identified key subsystems integral to her behavioral system model.

    Introduction to Dorothy E. Johnson’s Model

    Dorothy E. Johnson, a prominent nursing theorist, is known for her influential contributions to the field of nursing, particularly through her development of the Behavioral System Model. Her biography reveals a strong foundation built upon her upbringing, education, and extensive nursing career.

    Background on Dorothy E. Johnson Biography

    Dorothy Johnson’s life and career exemplify her dedication to nursing. Born on August 21, 1919, in Savannah, Georgia, her early years were marked by an environment that shaped her understanding of health challenges faced by communities with limited healthcare access. This upbringing fueled her passion for enhancing nursing care and advocating for patients.

    Early Life

    Johnson’s early life experiences were pivotal in her development as a nursing theorist. Growing up amidst societal health disparities, she developed a keen awareness of the necessity for effective nursing practices. These formative years laid the groundwork for her future endeavors in nursing education and theory formulation.

    Education

    Her academic journey commenced with an Associate’s Degree from Armstrong Junior College, followed by a Bachelor of Science in Nursing from Vanderbilt University. This rigorous academic background was further enriched by her Master of Public Health degree earned at Harvard University in 1948. The comprehensive nursing education she received fostered significant insights that would later influence her theoretical contributions.

    Career & Appointments

    Dorothy Johnson’s nursing career began as a pediatric nursing instructor at Vanderbilt University, where she served for approximately five years. Subsequently, she accepted a faculty position at UCLA, dedicating nearly 29 years to nursing education, research, and administration. Her teaching appointments allowed her to shape future generations of nurses and empower them with her theoretical knowledge. Notably, Johnson made a lasting impact on global nursing education during her sabbatical in India, where she successfully initiated a baccalaureate nursing program.

    Key Concepts of the Johnson Behavioral System Model

    Core ConceptDefinitionCharacteristicsClinical Application
    Behavioral SystemA system of patterned, repetitive, and purposeful behaviors that function as an integrated whole• Dynamic • Organized • Interdependent parts • Goal-directed • Self-maintaining • AdaptiveFoundation for nursing assessment, viewing the person holistically as a complete behavioral system
    System Balance & StabilityState of equilibrium among subsystems where all are functioning efficiently• Flexibility within stability • Efficient energy use • Predictable patterns • Effective adaptationGoal of nursing interventions is to maintain or restore system balance
    System ImbalanceDisruption in function of one or more subsystems• Inefficient behavior • Unpredictable responses • Maladaptive patterns • Energy misuseTriggers nursing assessment and intervention

    The Seven Behavioral Subsystems

    SubsystemPurposeKey BehaviorsFunctional RequirementsImbalance IndicatorsNursing Interventions
    Attachment/AffiliativeSocial inclusion and bond formation• Forming relationships • Social interaction • Intimacy behaviors • Belonging• Security in relationships • Opportunities for meaningful connection • Social stimulation• Social isolation • Difficulty forming attachments • Excessive dependency • Social withdrawal• Facilitate social connections • Promote therapeutic relationships • Support family involvement
    DependencyObtaining nurturing and approval• Help-seeking • Approval-seeking • Care-receiving behavior• Reliable caregivers • Appropriate assistance • Validation• Excessive dependency • Inability to seek help • Rejection of assistance• Provide appropriate assistance • Encourage self-care when possible • Establish boundaries
    IngestiveFood and fluid intake• Eating • Drinking • Food selection • Appetite regulation• Nutritional adequacy • Eating satisfaction • Cultural appropriateness• Poor appetite • Malnutrition • Disordered eating • Inadequate fluid intake• Nutritional assessment • Meal planning • Feeding assistance • Hydration management
    EliminativeExcretion of waste products• Bowel elimination • Urination • Sweating • Expelling carbon dioxide• Regular patterns • Privacy • Comfort • Accessibility• Constipation • Incontinence • Retention • Irregular patterns• Bowel/bladder training • Elimination monitoring • Environmental adaptations
    SexualProcreation and gratification• Sexual identity expression • Intimacy • Reproductive behaviors • Sexual response• Gender identity support • Privacy • Sexual health education • Respect for values• Sexual dysfunction • Identity conflicts • Reproductive disorders• Sexual health education • Respect privacy • Address concerns sensitively
    Aggressive/ProtectiveSelf-protection and preservation• Self-defense • Boundary setting • Protection of values • Assertion of rights• Safety • Ability to protect self • Constructive expression• Excessive aggression • Inability to defend self • Self-harm • Risk-taking• Safety planning • Boundary education • Anger management • Protective environments
    AchievementEnvironmental mastery and competence• Skill development • Intellectual pursuits • Goal-directed activities • Creative expression• Challenges • Recognition • Opportunities to achieve • Skill development• Underachievement • Perfectionism • Lack of motivation • Skill deficits• Realistic goal setting • Skill development • Recognition of achievements • Adaptive equipment

    Functional Requirements for All Subsystems

    RequirementDefinitionExamplesNursing Implications
    ProtectionShielding from harmful influences• Safe environment • Health maintenance • Disease preventionNurses implement protective measures to prevent system damage
    NurturanceProviding input needed for growth• Educational support • Emotional nourishment • Resource provisionNurses support growth of each subsystem through targeted interventions
    StimulationPromoting appropriate behavioral responses• Sensory input • Challenges • Activity promotionNurses provide appropriate stimulation to activate subsystems

    Nursing Process in JBSM

    Process StepFocusActivitiesGoals
    AssessmentIdentify subsystem status and function• Observe behavioral patterns • Interview about subsystem function • Evaluate relationships between subsystemsComprehensive understanding of behavioral system status
    DiagnosisDetermine causes of system imbalance• Identify structural issues (insufficient, excessive, or restrictive environment) • Recognize functional problems (impaired use or development)Clear identification of behavioral system problems
    InterventionApply external regulatory mechanisms• Impose (restrict behaviors) • Teach (new behaviors) • Support (existing adaptive behaviors)Restoration of behavioral system balance
    EvaluationMeasure restoration of balance• Reassess subsystem functioning • Monitor stability over time • Evaluate integration of subsystemsDocument progress toward behavioral system equilibrium

    External Regulatory Mechanisms

    MechanismPurposeExamplesClinical Application
    ImpositionEstablish or reinforce behavioral limits• Activity restrictions • Dietary limitations • Safety protocolsUsed when patient cannot self-regulate behaviors
    TeachingProvide knowledge for new behaviors• Health education • Skill development • Decision-making guidanceUsed to develop new, more adaptive behaviors
    SupportMaintain existing adaptive behaviors• Positive reinforcement • Environmental modifications • Resource provisionUsed to strengthen functional behaviors

    The Behavioral System Model proposed by Dorothy E. Johnson represents an essential facet of modern nursing theory, focusing on the interplay between various behavioral systems and their impact on patient health. This model places a premium on understanding the organized and dynamic nature of behaviors that each individual exhibits. The following sections will elucidate the concept definition of behavioral systems and outline the critical behavioral system model components essential for nursing practice.

    Definition of Behavioral Systems

    Behavioral systems refer to structured patterns of behavior that coexist within individuals, influenced by biological, psychological, and social factors. Through the lens of nursing theory, these systems emphasize the interaction and interdependence of behaviors, asserting that health outcomes are significantly influenced by how these behaviors are organized. Johnson’s model articulates that understanding these systems is critical for effective nursing care, as they help healthcare professionals identify areas where patients may be experiencing imbalance and require support.

    Components of the Johnson Behavioral System Model

    Johnson Behavioral System Model
    Johnson Behavioral System Model

    Within the Johnson Behavioral System Model, several components emerge that serve to categorize human behavior into distinct subsystems. Johnson identified seven behavioral system model components:

    • Attachment
    • Achievement
    • Aggressive
    • Dependence
    • Sexual
    • Ingestive
    • Eliminative

    Each of these subsystems possesses three functional requirements necessary for maintaining balance: protection from harmful influences, nurturing through appropriate environmental input, and stimulation for growth. Johnson’s insights into the behavioral system model components illuminate how these subsystems can interact and influence each other, essential for restoring equilibrium when disruptions occur. This holistic understanding is pivotal in nursing practices, where diverse factors converge to shape patient h

    Within the Johnson Behavioral System Model, several components emerge that serve to categorize human behavior into distinct subsystems. Johnson identified seven behavioral system model components:

    • Attachment
    • Achievement
    • Aggressive
    • Dependence
    • Sexual
    • Ingestive
    • Eliminative

    Each of these subsystems possesses three functional requirements necessary for maintaining balance: protection from harmful influences, nurturing through appropriate environmental input, and stimulation for growth. Johnson’s insights into the behavioral system model components illuminate how these subsystems can interact and influence each other, essential for restoring equilibrium when disruptions occur. This holistic understanding is pivotal in nursing practices, where diverse factors converge to shape patient health and wellbeing.

    The Role of the Nurse in the Model

    Johnson’s Behavioral System Model positions nursing as a fundamental component of behavioral science, highlighting its critical role in understanding patient behavior and influencing health outcomes. The model suggests that to fulfill their nursing responsibilities effectively, nurses must engage with the various behavioral subsystems that govern patients’ actions. This requires a nuanced approach that balances scientific knowledge with compassionate care, enabling nurses to address both physical and emotional dimensions of health.

    Nursing as a Behavioral Science

    The integration of nursing with behavioral science enables practitioners to observe and respond to patient needs more effectively. Nurses analyze behaviors that may indicate underlying health issues, applying research-based knowledge to foster a supportive environment conducive to healing. In this context, the nursing role encompasses not only the assessment of patients but also the creation of individualized care plans that promote optimal functioning across the identified subsystems. By focusing on holistic assessments, nurses can pinpoint interconnected problems and facilitate improved health outcomes for their patients.

    Responsibilities of the Nurse Practitioner

    Nurse practitioners carry substantial responsibilities in executing the principles outlined in Johnson’s model. Primarily, they evaluate the balance within a patient’s behavioral system, identifying any disruptions that could stem from internal stressors such as anxiety or external factors like environmental influences. Continuous assessment is vital as it allows for flexibility in care plans, ensuring they evolve alongside the patient’s needs. Additionally, nurse practitioner roles include the collaboration with interdisciplinary teams, which enhances the effectiveness of interventions aimed at restoring stability and promoting holistic well-being. This commitment to addressing both medical and behavioral challenges underscores the critical nature of nursing practice in achieving healthy patient outcomes.

    Johnson Behavioral System Model: Seven Subsystems Explained

    Dorothy Johnson viewed each person as a behavioral system made up of seven interconnected subsystems. Think of these subsystems as seven essential parts of a person that work together to maintain balance and health. When one subsystem is affected, it impacts the others—much like how a mobile hanging above a baby’s crib will tilt completely if just one piece is moved.

    Before we dive into each subsystem, remember that:

    • Each subsystem has a purpose (what it aims to accomplish)
    • Each has functional requirements (what it needs to work properly)
    • Each displays behaviors (observable actions)
    • Each requires nursing care when imbalanced

    1. Attachment and Affiliative Subsystem: Building Meaningful Connections

    What It Is

    This subsystem governs how we form social bonds and maintain relationships with others. It’s about our need to belong and connect.

    Real-World Example

    Meet Mrs. Chen: An 82-year-old widow hospitalized for pneumonia. She rarely has visitors and appears withdrawn. Nurses notice she brightens significantly when they spend extra time talking with her during medication administration.

    Functional Assessment

    • Healthy Function: Mrs. Chen maintained close relationships with her church group before hospitalization
    • Dysfunction: Isolation in hospital has disrupted her attachment patterns

    Nursing Application

    1. Personalized Care: The nurse assigns the same staff to Mrs. Chen when possible
    2. Environmental Adjustment: Places Mrs. Chen in a semi-private room with a compatible roommate
    3. Family Involvement: Coordinates video calls with her church friends
    4. Therapeutic Communication: Schedules brief but meaningful daily conversations

    Result

    Mrs. Chen develops a trusting relationship with her care team, participates more actively in recovery, and experiences reduced anxiety—demonstrating how supporting the attachment subsystem promotes healing.

    2. Dependency Subsystem: Balancing Help and Self-Reliance

    What It Is

    This subsystem controls behaviors related to caretaking, assistance, and the balance between dependence and independence.

    Real-World Example

    Meet James: A 45-year-old man recovering from a stroke who is frustrated by his new limitations. He refuses help with activities he cannot safely perform alone, saying “I don’t need anyone’s help!”

    Functional Assessment

    • Healthy Function: Before his stroke, James appropriately sought help for complex tasks while maintaining independence
    • Dysfunction: Now alternates between refusing necessary assistance and becoming frustrated when tasks are difficult

    Nursing Application

    1. Gradual Independence: The nurse creates a schedule where James does more for himself each day
    2. Reframing Assistance: Explains how accepting help now leads to greater independence later
    3. Partnership Approach: “Let’s work on this together” instead of “Let me do this for you”
    4. Celebrating Milestones: Acknowledges each new skill James masters

    Result

    James begins to accept necessary help while working toward independence, showing how properly supporting the dependency subsystem creates a healthy balance between assistance and autonomy.

    3. Ingestive Subsystem: Nourishing the Body and Mind

    What It Is

    This subsystem manages behaviors related to eating, drinking, and taking in nourishment—both what and how we consume.

    Real-World Example

    Meet Sophia: A 16-year-old with newly diagnosed diabetes who is struggling with dietary restrictions. She secretly eats forbidden foods and then lies about her blood sugar readings.

    Functional Assessment

    • Healthy Function: Previously ate a varied diet with regular meal patterns
    • Dysfunction: Now exhibits disordered eating patterns and resistance to dietary guidelines

    Nursing Application

    1. Education Through Exploration: The nurse helps Sophia discover diabetes-friendly versions of favorite foods
    2. Psychological Support: Addresses the emotional aspects of dietary changes
    3. Practical Skills: Teaches carbohydrate counting instead of rigid “forbidden foods” rules
    4. Social Strategies: Role-plays how to handle food-centered social situations

    Result

    Sophia develops a healthier relationship with food while managing her diabetes appropriately, demonstrating how addressing both physical and psychological aspects of the ingestive subsystem leads to better outcomes.

    4. Eliminative Subsystem: Managing Waste Processes with Dignity

    What It Is

    This subsystem regulates behaviors related to bodily excretion—how we eliminate waste biologically, socially, and psychologically.

    Real-World Example

    Meet Mr. Rodriguez: A 70-year-old man hospitalized after prostate surgery who is now incontinent. He refuses to leave his room or see visitors due to embarrassment.

    Functional Assessment

    • Healthy Function: Previously had normal elimination patterns and no social limitations
    • Dysfunction: Now experiencing incontinence and social withdrawal due to shame

    Nursing Application

    1. Preserving Dignity: The nurse ensures privacy during care and uses discreet incontinence products
    2. Scheduled Voiding: Implements a timed toileting program
    3. Environmental Control: Places his room near the bathroom and creates clear access
    4. Normalization: Explains that temporary incontinence is common after his procedure

    Result

    Mr. Rodriguez regains confidence to participate in physical therapy and accept visitors, showing how addressing both physical and psychological aspects of the eliminative subsystem preserves dignity and promotes recovery.

    5. Sexual Subsystem: Acknowledging Identity and Intimacy Needs

    What It Is

    This subsystem encompasses behaviors related to gender identity, sexual expression, and reproduction.

    Real-World Example

    Meet Maria: A 35-year-old woman recovering from a mastectomy who expresses concerns about her relationship with her husband and her self-image.

    Functional Assessment

    • Healthy Function: Previously had positive body image and satisfying intimate relationship
    • Dysfunction: Now experiencing altered body image and anxiety about intimacy

    Nursing Application

    1. Open Communication: The nurse creates opportunities to discuss concerns about intimacy and relationship changes
    2. Body Image Support: Teaches Maria how to care for her surgical site while acknowledging emotional responses
    3. Resource Connection: Provides information about support groups and reconstruction options
    4. Partner Inclusion: With Maria’s permission, includes her husband in discussions about adjustment

    Result

    Maria begins to adapt to body changes and communicates more openly with her husband, demonstrating how supporting the sexual subsystem addresses both physical adjustments and relational aspects of health.

    6. Aggressive/Protective Subsystem: Safeguarding Self and Values

    What It Is

    This subsystem manages behaviors related to self-protection, setting boundaries, and responding to threats—both real and perceived.

    Real-World Example

    Meet Devon: A 19-year-old admitted after a car accident who becomes verbally aggressive when healthcare decisions are made without his input.

    Functional Assessment

    • Healthy Function: Previously used appropriate assertiveness to protect his interests
    • Dysfunction: Now displaying excessive aggression due to feeling threatened and powerless

    Nursing Application

    1. Control Restoration: The nurse involves Devon in care planning: “What time would you prefer to take your medication?”
    2. Boundary Education: Teaches the difference between assertiveness and aggression
    3. Predictability: Explains procedures before they happen to reduce threat perception
    4. Validation: Acknowledges his right to have opinions about his care

    Result

    Devon’s aggressive outbursts decrease as he gains appropriate control over his care, showing how supporting healthy protective behaviors while redirecting unhelpful aggression balances this subsystem.

    7. Achievement Subsystem: Mastering Skills and Environment

    What It Is

    This subsystem directs behaviors related to accomplishment, intellectual mastery, and skill development.

    Real-World Example

    Meet Aisha: A 50-year-old teacher who has had a stroke affecting her language abilities. She becomes depressed when unable to read or communicate effectively.

    Functional Assessment

    • Healthy Function: Previously derived significant satisfaction from intellectual accomplishments and teaching
    • Dysfunction: Now experiencing frustration and loss of identity due to communication difficulties

    Nursing Application

    1. Modified Goals: The nurse helps break rehabilitation into achievable milestones
    2. Alternative Achievements: Identifies non-verbal accomplishments Aisha can master
    3. Progress Visibility: Creates a visual chart showing improvement over time
    4. Strength Focus: Emphasizes abilities retained rather than only what was lost

    Result

    Aisha engages more actively in speech therapy and finds new ways to experience achievement, demonstrating how supporting this subsystem maintains motivation and identity during recovery.

    How These Subsystems Work Together: A Holistic View

    Interconnected Nature

    Consider how these subsystems overlap and influence each other:

    Case Study: Mr. Jackson Mr. Jackson, a 60-year-old with newly diagnosed heart failure, shows how disturbance in one subsystem affects others:

    • Ingestive subsystem is affected by sodium restrictions
    • This impacts his achievement subsystem as he can no longer cook favorite family recipes
    • His attachment subsystem is strained as social gatherings revolved around these meals
    • His aggressive/protective subsystem activates as he feels his identity threatened
    • His dependency subsystem struggles with new reliance on medications
    • His eliminative subsystem is affected by diuretics
    • His sexual subsystem faces challenges due to medication side effects and fatigue

    Nursing Application to Multiple Subsystems

    Effective nursing care addresses these connections:

    1. Holistic Assessment: Evaluate all subsystems, not just the most obvious one
    2. Prioritization: Address the most critical subsystem first while planning for others
    3. Ripple Effect Planning: Anticipate how interventions in one area will affect others
    4. Patient Perspective: Ask which subsystem disruption matters most to the patient

    Practical Application for Nursing Students

    Assessment Questions for Each Subsystem

    Attachment:

    • “Who are the important people in your life?”
    • “How has your illness affected your relationships?”

    Dependency:

    • “What activities do you need help with now?”
    • “How do you feel about asking for assistance?”

    Ingestive:

    • “Describe your typical eating patterns.”
    • “Have you noticed any changes in appetite or enjoyment of food?”

    Eliminative:

    • “Have you experienced any changes in your bowel or bladder habits?”
    • “Are you comfortable using the bathroom facilities here?”

    Sexual:

    • “Has your condition affected how you see yourself?”
    • “Do you have concerns about how this condition might affect intimate relationships?”

    Aggressive/Protective:

    • “What helps you feel safe and in control?”
    • “How do you typically respond when you feel threatened?”

    Achievement:

    • “What activities give you a sense of accomplishment?”
    • “How has your condition affected your ability to do things that matter to you?”

    Creating Nursing Care Plans Using Johnson’s Model

    • Step 1: Identify which subsystems are imbalanced
    • Step 2: Determine what each subsystem needs (protection, nurturance, stimulation)
    • Step 3: Plan interventions that specifically address those needs
    • Step 4: Evaluate effectiveness by observing behavioral changes

    Example: For Mr. Jackson (heart failure patient mentioned earlier):

    • Priority Subsystem: Ingestive
    • Need: Knowledge about heart-healthy eating while preserving enjoyment
    • Intervention: Work with dietitian to modify favorite recipes to be heart-healthy
    • Evaluation: Mr. Jackson demonstrates understanding by creating a meal plan that follows restrictions while maintaining satisfaction

    Dorothy Johnson’s Behavioral System Model offers a structured way to understand the whole person—not just their medical diagnosis. By recognizing how these seven subsystems interact, nurses can:

    1. Provide truly holistic care that addresses all aspects of human functioning
    2. Anticipate problems before they develop by noticing early subsystem imbalances
    3. Create interventions that promote balance rather than just treating symptoms
    4. Recognize that behavior has meaning and serves a purpose in maintaining balance

    Remember that each patient’s behavioral system is unique, shaped by their culture, experiences, and values. The art of nursing using Johnson’s model lies in understanding each patient’s individual patterns and supporting their return to their optimal balance.

    Furthermore, Johnson Behavioral System Model can be effectively juxtaposed against other nursing theories, including Orem’s Self-Care Deficit Theory. While Orem emphasizes the importance of individual self-care abilities, Johnson’s framework places a greater emphasis on the nurse’s role in achieving behavioral equilibrium for their patients. This Johnson model comparison allows for deeper insights into varying approaches to nursing care, reinforcing the necessity for adaptable strategies that meet diverse patient needs. The exploration of these nursing theories further solidifies the importance of acknowledging both self-care capabilities and the facilitative role of nursing in managing patient behaviors and health outcomes.

    FAQ

    What is Dorothy E. Johnson’s Behavioral System Model?

    The Behavioral System Model developed by Dorothy E. Johnson emphasizes the relationship between nursing care and individuals’ behavioral functions to promote health and equilibrium. It advocates a holistic approach to nursing that integrates both the science and art of care.

    How does Johnson’s model categorize human behavior?

    Johnson’s model categorizes human behavior into seven distinct subsystems, each addressing a specific function and goal. These subsystems facilitate the understanding of how behaviors interconnect and influence health outcomes.

    What role do nurses play in the Behavioral System Model?

    Nurses are tasked with assessing behavioral systems, implementing interventions, and evaluating patient outcomes. They are responsible for creating a therapeutic environment that empowers patients to modify their behaviors for better health.

    How does the Behavioral System Model relate to patient autonomy?

    Johnson’s model underscores the importance of encouraging patient autonomy while recognizing their needs for support. This balance is critical for recovery and self-management, making it essential for nurses to foster independence during care.

    What are the practical applications of Johnson’s Behavioral System Model?

    The model’s framework aids nurses in systematizing patient assessments and interventions, ensuring that care is patient-centered and responsive to behavioral needs, ultimately facilitating recovery in clinical settings.

    How does the Behavioral System Model integrate into nursing education?

    By incorporating Johnson’s model into nursing curricula, students are equipped to analyze patient behaviors better and design effective care plans that align with holistic health promotion.

    How does Johnson’s model compare to Orem’s Self-Care Deficit Theory?

    While Orem’s theory focuses on individuals’ self-care abilities, Johnson emphasizes the role of nurses in facilitating behavioral equilibrium. Both theories contribute to a more comprehensive approach to patient care.

  • Lydia Hall Core Nursing Theory: Revolutionizing Patient Care Through the Core, Care, and Cure Model

    Lydia Hall Core Nursing Theory: Revolutionizing Patient Care Through the Core, Care, and Cure Model

    Lydia Hall stands as a pioneering figure in nursing theory whose innovative approach continues to shape modern nursing practice. Her Core Nursing Theory transformed how nurses conceptualize their roles in patient care by dividing nursing into three interconnected aspects: core, care, and cure.

    This comprehensive article explores Hall’s groundbreaking theoretical framework, its practical applications, and its enduring impact on the nursing profession. Whether you’re a nursing student, practicing nurse, or healthcare professional interested in theoretical foundations, understanding Lydia Hall’s contributions will deepen your appreciation of nursing’s intellectual heritage and enhance your approach to patient care.

    Lydia Hall Core Nursing Theory
    Lydia Hall Core Nursing Theory

    Lydia Hall – The Nursing Theorist Behind the Core Theory

    Lydia Eloise Hall was born on September 21, 1906, and emerged as an influential nursing theorist during a pivotal time in the profession’s development. With a diploma in nursing and later a degree in public health nursing, Hall developed her theoretical framework through extensive practical experience. Hall was always interested in rehabilitative nursing and the role nurses play in patient recovery.

    As a nursing theorist who developed innovative approaches to care, her background in both clinical practice and nursing education provided the foundation for her revolutionary ideas. Hall then worked in various settings before establishing the Loeb Center for Nursing and Rehabilitation, where she implemented her theoretical concepts. Hall died in 1969, but her thoughts about nursing continue to influence the profession today.

    Biography

    Lydia Eloise Hall was born on September 21, 1906, in New York City. Her early life of Lydia Hall unfolded in a family immersed in healthcare, with her father serving as a physician. This background played a crucial role in influencing her decision to pursue a nursing career.

    Hall graduated from York Hospital School of Nursing in 1927, marking the beginning of her nursing beginnings. Over the years, her achievements included employment with the New York Heart Association and the Life Extension Institute, where she focused on preventative health measures.

    Early Life

    The childhood influences that shaped Lydia Hall were deeply rooted in her family’s commitment to healthcare. Growing up surrounded by medical discussions and practices fostered her interest in nursing. This engagement with the healthcare field laid the groundwork for her empathetic approach to patient care, which defined her career trajectory and later informed her distinctive nursing philosophy.

    Education

    The education of Lydia Hall was extensive and instrumental in her development as a healthcare professional. She earned a Bachelor of Science degree in public health nursing from Teacher’s College at Columbia University in 1932. Hall continued her academic pursuits, obtaining a master’s degree in the teaching of natural life sciences in 1942. Her nursing credentials, encompassing various nursing degrees and extensive educational achievements, provided a solid foundation for her future endeavors, including a distinguished career as a professor at Columbia University.

    YearAchievement
    1906Birth in New York City
    1927Graduated from York Hospital School of Nursing
    1932B.Sc. in Public Health Nursing from Columbia University
    1942M.A. in Teaching Natural Life Sciences from Columbia University
    1950Professor at Teacher’s College, Columbia University
    1962Established the Loeb Center for Nursing and Rehabilitation
    1984Inducted into the American Nurses Association Hall of Fame

    What is the Core Nursing Theory?

    Understanding Hall’s Three-Circle Model within the nursing process 

    Lydia Hall’s theory centers around three interconnected aspects of nursing: core, care, and cure. According to the theory, these three elements work together to provide comprehensive patient care. The core is the patient as a person with their individual needs, feelings, and goals. The care circle represents the nurturing component of nursing practice, involving bodily care and comfort.

    The cure aspect encompasses the medical interventions and therapeutic treatments administered by healthcare professionals. Hall’s theory was unique in its approach to patient care, emphasizing that these three aspects must be balanced for effective nursing.

    By dividing nursing into these three components, Lydia Hall’s nursing theory offered a clear framework for understanding the complexity of the nursing profession and the importance of the total patient experience.

    How Does the Core Component Function in Lydia Hall’s Nursing Theory?

    In Lydia Hall’s theoretical framework, the core is the patient as a whole person with their unique identity, values, and needs.

    Core is the patient’s internal self, encompassing their social, emotional, and psychological dimensions. According to Lydia, the core component requires nurses to develop therapeutic relationships based on understanding the individual care recipient as more than just their medical condition.

    The core is fundamentally about the patient as a whole person – not just their physical body or medical condition, but their complete identity with all its psychological, emotional, and social dimensions. Think of the core as addressing the question, “Who is this person beyond their illness?”

    In Hall’s conceptualization, the core deals with:

    1. The patient’s internal self – This includes their feelings, thoughts, values, beliefs, and experiences that shape how they perceive their illness and treatment. When nurses engage with the core component, they recognize that each patient brings their unique life story and perspective to the healthcare encounter.
    2. Therapeutic relationships – The core component functions through meaningful nurse-patient interactions that go beyond procedural care. Hall believed that by developing authentic connections with patients, nurses could help them tap into their own internal resources for healing.
    3. Patient autonomy and self-determination – The core component emphasizes the patient’s right and capacity to participate in their own care decisions. According to Lydia Hall, nursing that addresses the core helps patients express their needs and preferences, empowering them to take an active role in their recovery process.

    The functioning of the core component requires specific nursing knowledge and skills. Nurses working within this dimension draw upon psychological understanding, communication techniques, active listening, and therapeutic presence. Unlike the care component (which focuses on physical body care) or the cure component (which deals with medical treatments), the core represents nursing’s unique attention to the person’s sense of self and identity.

    How Does the Care Component Function in Lydia Hall’s Nursing Theory?

    The care circle in Lydia Hall’s theory represents the nurturing aspects of nursing practice. This dimension focuses on providing bodily care, physical comfort, and meeting basic human needs.

    Hall’s care component involves direct nursing interventions such as bathing, feeding, and positioning—the intimate aspects of patient care that define the nursing profession. The care provided forms the foundation of the nurse-patient relationship and establishes trust.

    The care component in Lydia Hall’s nursing theory focuses on the hands-on, physical aspects of nursing. Here’s how it works:

    What the care component is about:

    • Physical, and bodily care of patients
    • The nurturing dimension of nursing practice
    • Direct hands-on nursing interventions

    Key functions of the care component:

    1. Meeting physical needs
      • Bathing, feeding, and positioning patients
      • Helping with movement and comfort
      • Providing personal hygiene assistance
      • Managing physical symptoms
    2. Building trust through physical care
      • Creating connection through therapeutic touch
      • Establishing rapport during care activities
      • Demonstrating compassion through comfort measures
    3. Serving as a gateway to other components
      • Using care moments to assess emotional needs (core)
      • Identifying medical treatment needs (cure) during physical care
      • Integrating all aspects of nursing during bodily care

    Cure Theory in Lydia Eloise Hall Nursing Model

    The integration of the Cure Theory aspect into Hall’s Nursing Model enhances its comprehensiveness by addressing the medical dimension of patient care, thereby completing the model’s holistic framework. Here’s a structured breakdown:

    Lydia Hall Core Nursing Theory Model
    Lydia Hall Core Nursing Theory Model
    1. Hall’s Three Components:
      • Care: Hands-on, nurturing support (e.g., hygiene, comfort).
      • Core: Emotional, psychological, and identity-focused care (therapeutic communication, self-awareness).
      • Cure: Medical interventions and collaboration with healthcare professionals.
    2. Role of Cure Theory:
      • Medical Expertise: Strengthens the “cure” component by emphasizing evidence-based practices, clinical judgment, and adherence to medical protocols, ensuring nurses actively participate in treatment beyond passive task execution.
      • Interdisciplinary Collaboration: Highlights the nurse’s role as a collaborator with physicians and other professionals, fostering teamwork for optimal patient outcomes.
      • Patient Education: Integrates teaching patients about their conditions and treatments, empowering them to engage in their own care.
      • Monitoring and Adaptation: Encourages dynamic assessment of patient responses to treatments, enabling timely adjustments to care plans.
    3. Holistic Completion:
      • Without the cure aspect, Hall’s model would lack actionable medical strategies. Cure Theory ensures that scientific, procedural, and educational elements are systematically incorporated, balancing the physical (care), emotional (core), and clinical (cure) needs of patients.
      • Modern advancements in Cure Theory (e.g., technology integration, patient-centered care) update Hall’s 1960s model, making it relevant to contemporary practice.
    4. Synergy:
      • The Cure Theory bridges the gap between compassionate care (care/core) and medical rigor, ensuring nurses address all facets of healing. This synergy fosters a patient-centered approach where medical treatment is delivered alongside empathetic support, promoting holistic recovery.

    In essence, the Cure Theory completes Hall’s model by solidifying the nurse’s role in medical interventions, ensuring a triad of care that is physically nurturing, emotionally supportive, and clinically effective.

    Lydia Hall’s Approach to Patient Care Revolutionary

    Lydia Hall’s approach to care was revolutionary because it challenged the traditional disease-focused medical model. By emphasizing the interconnection between core, care, and cure, Hall elevated nursing beyond task-oriented practice to a holistic profession. Her philosophy of care recognized the patient as an active participant rather than a passive recipient—a concept that was ahead of its time.

    The nursing theorist developed her ideas when the role of nurses was primarily viewed as physician assistants rather than autonomous practitioners. Hall’s theory working together with her practical implementation at the Loeb Center for Nursing and Rehabilitation demonstrated the effectiveness of patient-centered nursing care. Her approach to care emphasized rehabilitation and recovery rather than just disease management. The patient receiving nursing care was seen as a complex individual with physical, emotional, and social needs, not merely a collection of symptoms. This revolutionary perspective continues to influence nursing education and patient care today.

    Core Nursing Theory’s Influence on Modern Nursing Practice

    Lydia Hall’s core nursing theory has significantly shaped modern nursing practice by emphasizing patient-centered care and holistic approaches. Concepts from her theory appear in contemporary nursing care plans and guide nursing interventions across various specialties. The theory has influenced nursing diagnosis processes by encouraging consideration of psychosocial factors alongside physical symptoms.

    In nursing education, Hall’s three aspects of nursing—core, care, and cure—provide a framework for teaching comprehensive patient assessment. Modern nursing theories study guides often reference Hall’s work as foundational to understanding nursing’s theoretical development.

    Her emphasis on rehabilitation has particularly influenced areas like long-term care and chronic disease management. The philosophy of nursing that emerged from Hall’s work continues to shape professional identity and practice standards. By establishing that the core is the patient rather than the disease, Hall helped shift nursing’s focus toward person-centered care that characterizes the best of modern practice.

    What Are the Practical Applications of Hall’s Theory in Nursing Care Plans

    Lydia Hall’s theory provides practical guidance for developing comprehensive nursing care plans. When applying Hall’s framework, nursing assessment incorporates all three dimensions—evaluating physical needs (care), medical requirements (cure), and psychological well-being (core). Care plans based on this theory include interventions addressing physical comfort, medical treatment, and emotional support.

    The nursing process guided by Hall’s theory ensures attention to the whole person rather than just presenting symptoms. Nursing diagnosis within this framework considers how physical ailments affect the patient’s sense of self and social functioning. The three aspects of patient care—core, care, and cure—provide a checklist for ensuring comprehensive planning.

    In specialized areas like psychiatric nursing, Hall’s emphasis on the core component is particularly valuable for treatment planning. Lydia Hall used her knowledge of psychiatry and nursing experiences in the Loeb Center to demonstrate how theory could be translated into practical care guidelines. This practical application of theory to patient care remains one of Hall’s most significant contributions to the nursing profession.

    How Does Hall’s Theory Compare to Other Major Nursing Theories?

    When compared to other nursing theories, Lydia Hall’s framework offers a unique perspective focused on the three interrelated dimensions of nursing. Unlike Virginia Henderson’s 14 fundamental needs, or Dorothy Orem’s self-care deficit theory, Hall emphasizes the integration of psychological, nurturing, and medical aspects of care. While Martha Rogers’ Science of Unitary Human Beings presents abstract concepts, Hall’s theory provides more concrete guidance for everyday nursing practice.

    Jean Watson’s Theory of Human Caring shares Hall’s emphasis on the therapeutic relationship but focuses more explicitly on caring as the moral ideal of nursing. In contrast to Hildegard Peplau’s interpersonal relations model, which centers entirely on the nurse-patient relationship, Hall’s theory acknowledges the importance of medical interventions alongside relational work. Dorothy Johnson’s Behavioral System Model and Hall’s theory both categorize nursing activities, but Hall specifically addresses the interconnection between psychological, physical, and medical domains. When compared to Faye Abdellah’s 21 Nursing Problems Theory, Hall’s model provides a broader conceptual framework rather than specific problem areas. This comparative analysis highlights the distinctive contribution Hall made to nursing theoretical development.

    Why Should Modern Nurses Learn About Lydia Hall and Her Nursing Theory?

    Modern nurses should study Lydia Hall and her nursing theory because it provides a foundational framework for understanding holistic patient care. In today’s healthcare environment, where technical skills often overshadow interpersonal aspects of nursing, Hall’s emphasis on the core component reminds practitioners of the human dimension of their work. Her theory helps nurses articulate the unique contribution they make to healthcare that differs from but complements medical practice.

    For nursing students, Hall’s three aspects of the theory offer a straightforward model for organizing their approach to patient care. Understanding Hall’s core theory assumptions helps practitioners balance the competing demands of modern healthcare systems while maintaining patient-centered focus. As a pioneer in nursing who advocated for nursing autonomy, Hall’s legacy inspires new generations of nurses to develop the profession’s distinct knowledge base and practice standards. By learning about Lydia Hall’s core nursing theory, contemporary nurses connect with the intellectual heritage of their profession and gain perspectives that enhance their clinical judgment and patient advocacy.

    Key Takeaways from Lydia Hall’s Core, Care, and Cure Theory

    Lydia Hall’s care component forms a central pillar of her nursing theory, highlighting the essential role of hands-on physical caregiving in the therapeutic process. Through her innovative framework, Hall elevated nursing care from routine tasks to meaningful interventions, establishing that participation in care by both nurse and patient creates healing opportunities beyond medical treatment alone.

    At the Loeb Center, which Hall also managed, she taught nursing students to function within all three aspects of nursing—core, care, and cure—while emphasizing that providing this care with intention and skill distinguishes nursing from other healthcare disciplines. Her approach recognized that care to the patient extends beyond physical interventions to encompass the relationship formed during caregiving activities.

    The concepts of care Hall developed reflected her background in science in public health nursing and her deep understanding of the nature of nursing as both art and science. While cure is the attention given to medical aspects and core addresses psychological dimensions, Hall maintained that care and core must work together to support the patient’s overall wellbeing.

    In advancing nursing practice through her theory, Hall established that cure is nursing’s collaborative component with medicine, whereas care represents nursing’s unique contribution. By developing the care dimension of her framework, Hall created a foundation for understanding nursing’s distinctive role in the care of the patient, influencing the nursing need theory movement and establishing care as the nurturing heart of the nursing profession.

    • Lydia Eloise Hall developed a three-part theoretical model consisting of core (person), care (body), and cure (disease) components that must work in balance for effective nursing.

    • The core represents the patient as a person with social, emotional, and psychological dimensions requiring therapeutic communication and relationship-building.

    • The care circle encompasses bodily care, comfort measures, and the nurturing aspects of nursing that establish trust and meet basic human needs.

    • The cure component involves medical interventions, treatments, and technical aspects of care that address the patient’s disease or condition.

    • Hall’s theory emphasizes patient participation in care and rehabilitation rather than passive treatment.

    • The Loeb Center for Nursing and Rehabilitation served as a practical implementation site where Hall demonstrated her theoretical concepts.

    • Hall’s approach revolutionized nursing by challenging the disease-focused medical model and establishing nursing as a holistic profession.

    • The theory continues to influence modern nursing practice, education, and care planning by providing a framework for comprehensive patient care.

    • Hall was a nursing theorist who developed her ideas through extensive practical experience in public health nursing and rehabilitation.

    • Understanding Hall’s theory helps modern nurses balance technical skills with interpersonal aspects of care in increasingly complex healthcare environments.

    FAQ

    What is the “Care, Core, Cure” model developed by Lydia E. Hall?

    The “Care, Core, Cure” model is a framework created by Lydia E. Hall that emphasizes the interrelated aspects of nursing care. It highlights the role of nurses in providing care, the individual patient as the core, and the collaborative “cure” efforts shared with other healthcare professionals.

    How did Lydia Hall’s upbringing influence her career in nursing?

    Growing up in a family involved in healthcare, particularly with her father as a physician, significantly shaped Lydia Hall’s passion for patient care. Her early exposure to healthcare principles instilled in her a commitment to compassionate and comprehensive nursing practice.

    What are the key assumptions of Hall’s nursing model?

    Key assumptions of Hall’s model include the belief that healing motivation originates from within the patient and that the care, core, and cure aspects are interrelated. These areas influence one another and vary in importance based on the patient’s needs.

    How does the “Care, Core, Cure” model apply to contemporary nursing practice?

    Hall’s model promotes a holistic approach to nursing care by encouraging nurses to address both physical and emotional needs of patients. For instance, in rehabilitative settings, nurses applying her principles might provide physical assistance while also engaging patients in supportive discussions about their health.

    In what ways is Lydia E. Hall recognized as a trailblazer?

    Lydia E. Hall is celebrated as an African American trailblazer for her contributions to nursing theory and her advocacy for women’s rights. Her innovative “Care, Core, Cure” model has had a lasting impact on nursing education and practice, making her an inspirational leader in the field.

    Can you explain the importance of interdisciplinary collaboration in Hall’s model?

    Interdisciplinary collaboration is central to Hall’s model as it promotes an integrated approach to patient treatment. By collaborating with other healthcare professionals, nurses can ensure that patients receive comprehensive care that addresses both their medical and emotional needs.

    What legacy did Lydia Hall leave in the field of nursing?

    Lydia Hall’s legacy includes her pioneering contributions to nursing theory, particularly her “Care, Core, Cure” model, which continues to influence nursing practices and education today. Her emphasis on holistic care and interdisciplinary collaboration has paved the way for future advancements in nursing and healthcare.